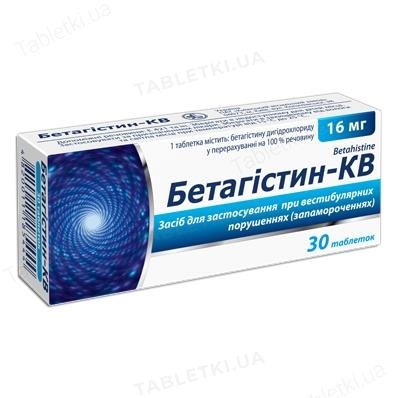


Betahistine-KV 16 mg tablets, No. 30 (10 x 3)
Composition
Active ingredient: betahistine dihydrochloride;
1 tablet contains 8, 16, or 24 mg of betahistine dihydrochloride, calculated as 100% active ingredient;
Excipients: microcrystalline cellulose, mannitol (E 421), colloidal anhydrous silicon dioxide, talc, citric acid monohydrate, stearic acid.
Dosage Form
Tablets.
Main physical and chemical properties:
8 mg tablets: flat-cylindrical tablets with a bevel, white or almost white in color. A marbled appearance on the surface of the tablets is permissible;
16 mg or 24 mg tablets: flat-cylindrical tablets with a bevel and a score line, white or almost white in color. Marbling on the surface of the tablets is permissible.
Pharmacotherapeutic group
Agents for the treatment of vestibular disorders.
ATC code N07C A01.
Pharmacological Properties
Pharmacodynamics.
The mechanism of action of betahistine has been only partially elucidated. Several plausible hypotheses have been confirmed by studies conducted in animals and humans.
Effect of betahistine on the histaminergic system.
It has been established that betahistine exhibits partial agonist activity at H1 receptors, as well as antagonist activity at H3 histamine receptors in nervous tissue, and has negligible activity at H2 histamine receptors. Betahistine increases the metabolism and release of histamine by blocking presynaptic H3 receptors and inducing a reduction in the number of these receptors.
Betahistine may increase blood flow in the cochlear region as well as throughout the entire brain.
There is evidence of improved blood flow in the stria vascularis of the inner ear, possibly due to the relaxation of precapillary sphincters in the inner ear’s microcirculatory system. Betahistine has also been shown to increase cerebral blood flow in humans.
Betahistine promotes vestibular compensation.
Betahistine accelerates the recovery of vestibular function following unilateral neurectomy in animals by stimulating and facilitating the process of central vestibular compensation. This effect is characterized by enhanced regulation of histamine metabolism and release and is mediated by H3-receptor antagonism. In humans, treatment with betahistine also reduced the time required for vestibular function to recover after neurectomy.
Betahistine alters neuronal activity in the vestibular nuclei.
It has also been established that betahistine has a dose-dependent inhibitory effect on the generation of spike potentials in neurons of the lateral and medial vestibular nuclei.
It is known that the pharmacodynamic properties of betahistine can produce a positive therapeutic effect of the drug on the vestibular system.
The efficacy of betahistine has been demonstrated in studies of patients with vestibular vertigo and Meniere’s disease, as evidenced by a reduction in the severity and frequency of vertigo attacks.
Pharmacokinetics.
Absorption. When administered orally, betahistine is rapidly and almost completely absorbed throughout the gastrointestinal tract. After absorption, the drug is rapidly and almost completely metabolized to form the metabolite 2-pyridylacetic acid. Plasma concentrations of betahistine are very low. Therefore, all pharmacokinetic analyses are conducted by measuring the concentration of the 2-pyridylacetic acid metabolite in plasma and urine.
When the drug is taken with food, the maximum concentration (Cmax) is lower than when taken on an empty stomach. However, the extent of absorption of betahistine is identical in both cases, indicating that food intake merely slows down the absorption of the drug.
Distribution. The percentage of betahistine bound to plasma proteins is less than 5%.
Biotransformation. After absorption, betahistine is rapidly and almost completely metabolized to 2-pyridylacetic acid (which has no pharmacological activity).
After oral administration of betahistine, the concentration of 2-pyridylacetic acid in plasma (and in urine) reaches its peak 1 hour after administration and declines with a half-life of approximately 3.5 hours.
Excretion. 2-pyridylacetic acid is rapidly excreted in the urine. When the drug is administered at a dose of 8–48 mg, approximately 85% of the initial dose is excreted in the urine. Renal or fecal excretion of betahistine is negligible.
Linearity. The rate of elimination remains constant following oral administration of 8–48 mg of the drug, indicating the linearity of betahistine’s pharmacokinetics and suggesting that the metabolic pathway involved is non-saturable.
Indications
Ménière’s disease and syndrome, which are characterized by three main symptoms:
- vertigo, sometimes accompanied by nausea and vomiting;
- hearing loss (deafness);
- tinnitus.
Symptomatic treatment of vestibular vertigo of various origins.
Contraindications
Hypersensitivity to any of the drug’s components. Pheochromocytoma.
Interactions with Other Medications and Other Types of Interactions
No in vivo studies have been conducted to investigate interactions with other medications. Based on in vitro data, inhibition of cytochrome P450 enzyme activity in vivo is not expected.
Data obtained in vitro indicate that the metabolism of betahistine is inhibited by drugs that inhibit monoamine oxidase (MAO) activity, including MAO subtype B (e.g., selegiline). Caution is recommended when betahistine is used concomitantly with MAO inhibitors (including those that selectively inhibit MAO subtype B).
Since betahistine is a histamine analog, its interaction with antihistamines could theoretically affect the efficacy of one of these drugs.
Special Considerations for Use
During treatment with this medication, patients with a history of bronchial asthma and/or gastric or duodenal ulcers should be closely monitored.
Use during pregnancy or breastfeeding.
Pregnancy. There are insufficient data on the use of betahistine in pregnant women.
Animal studies are insufficient to assess the effects on pregnancy, embryo/fetal development, labor, and postnatal development. The potential risk to humans is unknown. Betahistine should not be used during pregnancy unless clearly necessary.
Breastfeeding. It is unknown whether betahistine is excreted in human breast milk. No animal studies have been conducted on the excretion of betahistine into milk. The benefits of using the drug for the mother should be weighed against the benefits of breastfeeding and the potential risk to the infant.
Effect on reaction time when operating motor vehicles or other machinery.
Betahistine is indicated for the treatment of Meniere’s disease, characterized by a triad of primary symptoms: vertigo, hearing loss, and tinnitus—as well as for the symptomatic treatment of vestibular vertigo. Both conditions may adversely affect the ability to drive a car or operate machinery. Betahistine is known to have no effect or only a negligible effect on the ability to drive a car or operate machinery.
Dosage and Administration
The daily dose for adults is 24–48 mg, divided evenly throughout the day.
| 8-mg tablets | 16 mg tablets | 24 mg tablets |
| 1–2 tablets
3 times a day |
½–1 tablet
3 times a day |
1 tablet
2 times a day |
The dose should be adjusted individually, depending on the response. Symptom relief is sometimes observed only after two to three weeks of treatment. The best results are sometimes achieved when the medication is taken for several months. There is evidence that initiating treatment early in the course of the disease prevents its progression and/or hearing loss in later stages.
Elderly patients
Postmarketing experience with the drug suggests that no dose adjustment is necessary for this patient population.
Renal impairment
Postmarketing experience indicates that no dose adjustment is necessary.
Hepatic impairment
Postmarketing experience indicates that no dose adjustment is necessary.
Children. Due to insufficient data on the safety and efficacy of this drug, it is not recommended for use in children (under 18 years of age).
Overdose
Several cases of overdose with this medication have been reported. Some patients experienced mild to moderate symptoms (nausea, drowsiness, abdominal pain) after taking doses of up to 640 mg. More serious complications (seizures, cardiopulmonary complications) have been observed following the intentional ingestion of high doses of betahistine, especially when combined with an overdose of other medications.
Treatment of overdose should include standard supportive measures.
Side Effects
Gastrointestinal: nausea and dyspepsia, mild gastrointestinal disturbances (vomiting, gastrointestinal pain, abdominal distension, and flatulence). These side effects usually resolve when the medication is taken with food or after the dose is reduced.
Nervous system: headache.
Immune system: hypersensitivity reactions, such as anaphylaxis.
Skin and subcutaneous tissue disorders: Hypersensitivity reactions of the skin and subcutaneous tissue have been observed, including angioedema, rash, itching, and hives.
Shelf life
3 years.
Storage Conditions
Store in the original packaging at a temperature not exceeding 25 °C.
Keep out of reach of children.
Packaging
10 tablets per blister pack, 3 blister packs per box.
Manufacturer
JSC “KYIV VITAMIN PLANT.”
Address
38 Kopylivska St., Kyiv, 04073, Ukraine.
Website: www.vitamin.com.ua.