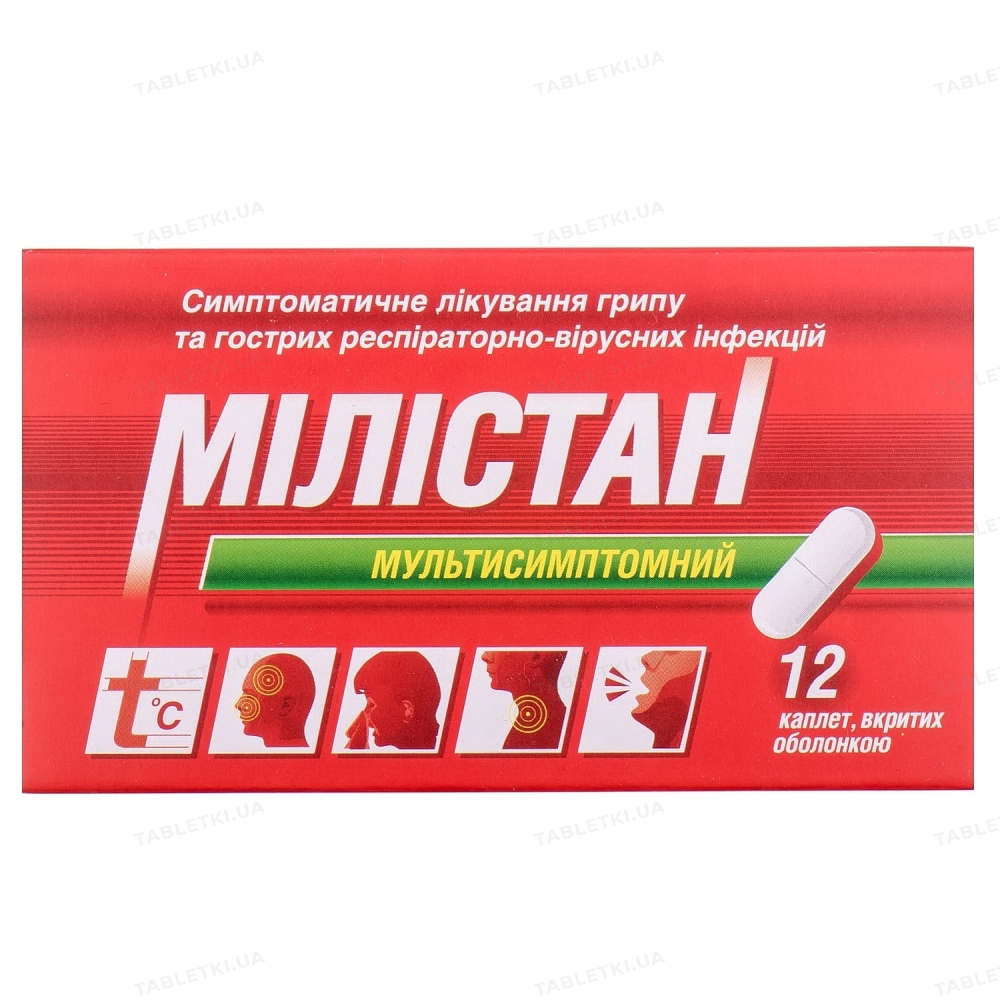
Milistan Multisymptomatic Caplets, Batch No. 12
Composition
Active ingredients: Each tablet contains 325 mg of acetaminophen, 10 mg of cetirizine hydrochloride, 2 mg of chlorpheniramine maleate, and 15 mg of dextromethorphan hydrobromide;
inactive ingredients: corn starch, microcrystalline cellulose, methylparaben (E 218), propylparaben (E 216), magnesium stearate, talc, colloidal anhydrous silicon dioxide, sodium lauryl sulfate, sodium starch glycolate (type A), hypromellose, propylene glycol, polyethylene glycol 4000, titanium dioxide (E 171).
Dosage form
Film-coated caplets.
Main physical and chemical properties: white or almost white, oval-shaped, biconvex film-coated caplets with a score line on one side.
Pharmacotherapeutic group
Analgesics and antipyretics. Paracetamol in combination with other drugs (excluding psycholeptics). ATC code N02B E51.
Pharmacological properties
Pharmacodynamics.
Paracetamol has analgesic, antipyretic, and anti-inflammatory properties. The mechanism of paracetamol’s analgesic effect is associated with the inhibition of prostaglandin biosynthesis. By inhibiting cyclooxygenase, it prevents the formation of prostaglandins E2 and F2, which play an important role in the perception of pain stimuli by nociceptors and the transmission of excitation in the central nervous system. Paracetamol inhibits cyclooxygenase more effectively in CNS cells and to a much lesser extent in peripheral tissues. Paracetamol’s lack of effect on prostaglandin synthesis in peripheral tissues explains its lack of adverse effects on water-salt balance and the gastrointestinal mucosa. The antipyretic effect of paracetamol is due to the inhibition of prostaglandin biosynthesis directly in the hypothalamus, where prostaglandins act as mediators of the thermoregulatory center.
Cetirizine hydrochloride is a selective antagonist of peripheral H1-histamine receptors and a metabolite of hydroxyzine. It prevents the development of and alleviates the course of allergic reactions and has antipruritic and antiexudative effects. It exerts its antiallergic effect by inhibiting the late phase of cell migration involved in the inflammatory response (primarily eosinophils); and also reduces the expression of adhesion molecules, such as ICAM-1 and VCAM-1, which are markers of allergic inflammation. It inhibits the action of other mediators and inducers of histamine secretion, such as PAF (platelet-activating factor) and substance P. It has virtually no anticholinergic or antiserotonergic effects. It reduces capillary permeability, prevents the development of tissue edema, and relieves smooth muscle spasms. It has virtually no anticholinergic or antiserotonergic effects. At therapeutic doses, it has no sedative effect.
Dextromethorphan hydrobromide is an antitussive agent effective for nonproductive bronchial cough. Its mechanism of action involves the suppression of afferent impulses from the respiratory tract mucosa and an increase in the sensitivity threshold of the cough center in the medulla oblongata. At therapeutic doses, dextromethorphan does not cause analgesic or sedative effects, nor does it depress respiration, cause dependence, or inhibit ciliary activity.
Chlorpheniramine maleate—an antiallergic agent and histamine H1 receptor blocker—has antiallergic effects, reduces capillary permeability, constricts blood vessels, and alleviates swelling and hyperemia of the nasal mucosa, nasopharynx, and paranasal sinuses; reduces local exudative manifestations, and alleviates the symptoms of allergic rhinitis (sneezing, rhinorrhea, itching of the eyes, nose, and throat). It causes a moderately pronounced sedative effect.
Pharmacodynamics.
Absorption. After oral administration, the drug is rapidly and almost completely absorbed from the gastrointestinal tract.
Elimination. The half-life of acetaminophen is 1–4 hours. In patients with liver cirrhosis, the half-life is prolonged. Plasma protein binding is variable.
Renal clearance of paracetamol is 5%. It is excreted in the urine primarily as glucuronide and sulfate conjugates.
After a single oral dose of cetirizine hydrochloride, the half-life is approximately 10 hours; two-thirds of the drug is excreted unchanged by the kidneys, and about 10% is excreted in the feces. Systemic clearance is 53 mL/min.
The half-life of dextromethorphan hydrobromide is approximately 4 hours; the drug is excreted by the kidneys in its unchanged form and as demethylated metabolites (including dextrorphan). The active ingredients of the drug cross the placenta and pass into breast milk.
Indications
Symptomatic treatment of influenza and other acute respiratory viral infections accompanied by a dry, irritating cough, fever, muscle and joint pain, headache, nasal congestion, runny nose, and watery eyes; including those accompanied by allergies.
Contraindications
- Hypersensitivity to the components of the drug, to hydroxyzine, or to any piperazine derivative or other antihistamines.
- Severe renal impairment.
- Severe liver dysfunction, congenital hyperbilirubinemia, alcoholism, Gilbert’s syndrome.
- Blood disorders, glucose-6-phosphate dehydrogenase deficiency, severe anemia, leukopenia, and hypocoagulation.
- Angle-closure glaucoma.
- Risk of urinary retention due to diseases of the urethra and prostate, bladder neck obstruction.
- Pyloroduodenal stenosis, intestinal obstruction.
- Severe hypertension, coronary artery disease, arrhythmias. Diabetes mellitus, hyperthyroidism.
- Epilepsy.
- Patients at risk of respiratory failure.
- Do not use concomitantly with monoamine oxidase (MAO) inhibitors or within 2 weeks after discontinuing MAO inhibitors, antidepressants that inhibit serotonin reuptake (fluoxetine, paroxetine).
Drug Interactions and Other Interactions
Concomitant use of this medication with other drugs containing acetaminophen or other active ingredients included in Milistan Multisymptomatic should be avoided.
The nature of these interactions is determined by the properties of the drug’s components.
Paracetamol.
The rate of paracetamol absorption may increase with the use of metoclopramide and domperidone and decrease with the use of cholestyramine. The anticoagulant effect of warfarin and other coumarins, which increases the risk of bleeding, may be enhanced with concomitant long-term use of paracetamol. Intermittent use has no significant effect. Barbiturates reduce the antipyretic effect of paracetamol.
Anticonvulsants (including phenytoin, barbiturates, and carbamazepine), which stimulate the activity of hepatic microsomal enzymes, may increase the toxic effect of acetaminophen on the liver by increasing the extent to which the drug is converted into hepatotoxic metabolites. Concomitant use of paracetamol with hepatotoxic agents increases the toxic effects of these drugs on the liver. Concomitant use of high doses of paracetamol with isoniazid increases the risk of developing hepatotoxic syndrome.
Paracetamol reduces the effectiveness of diuretics. Do not use concomitantly with alcohol.
Caffeine may potentiate the analgesic effect of acetaminophen.
Caution is advised when paracetamol is used concomitantly with flucloxacillin, as such concomitant use is associated with metabolic acidosis with a high anion gap due to pyroglutamic acidosis, especially in patients with risk factors (see the “Special Considerations for Use” section).
Cetirizine hydrochloride
In a study of repeated administration of theophylline (400 mg once daily) and cetirizine, a slight (16%) decrease in cetirizine clearance was observed, while the disposition of theophylline was not increased when taken concomitantly with cetirizine.
In a study of repeated administration of ritonavir (600 mg twice daily) and cetirizine (10 mg daily), the duration of exposure to cetirizine increased by approximately 40%, while the disposition of ritonavir was slightly impaired (-11%) when taken concomitantly with cetirizine.
There are no data on the potentiation of the effects of sedatives when cetirizine is used at therapeutic doses. However, the use of sedatives should be avoided while taking cetirizine.
The extent of absorption of cetirizine is not reduced by food intake, although the rate of absorption is delayed by 1 hour.
Concomitant use of the drug with alcohol or other central nervous system depressants may cause further impairment of attention and performance, although cetirizine does not potentiate the effects of alcohol (at blood alcohol levels of 0.5 g/L).
Chlorpheniramine maleate
Alcoholic beverages or medications that depress the central nervous system may enhance the sedative effects of similar drugs or antihistamines, such as chlorpheniramine, which may lead to symptoms of overdose.
Chlorpheniramine inhibits the metabolism of phenytoin and may lead to phenytoin toxicity.
Contraindicated with MAO inhibitors. Monoamine oxidase inhibitors (MAO inhibitors), including furazolidone (an antibacterial drug) and procarbazine (an antineoplastic drug): Concomitant use is not recommended, as the anticholinergic effects and central nervous system depression characteristic of antihistamines may be prolonged and intensified.
Tricyclic antidepressants or maprotiline (a tetracyclic antidepressant) and other anticholinergic drugs: the anticholinergic effects of these drugs or of antihistamines such as chlorpheniramine may be potentiated. If gastrointestinal side effects occur, patients should consult a doctor as soon as possible, as this may lead to paralytic ileus.
Ototoxic drugs may mask symptoms of ototoxicity, such as ringing in the ears, dizziness, and fainting.
Photosensitizing medications may cause an additional photosensitizing effect.
This medication should not be used concurrently with antitussives that suppress the cough reflex (e.g., codeine), especially before bedtime. Such combined use of medications impedes expectoration.
Dextromethorphan hydrobromide
When dextromethorphan, which is a component of this medication, is used concomitantly with other medications, the following interactions are possible:
with MAO inhibitors, medications for Parkinson’s disease, selective serotonin reuptake inhibitors (SSRIs), and other antidepressants—potentiation of the effects of the latter; Concomitant use of this medication with the aforementioned drugs is contraindicated;
with amiodarone and quinidine—increased plasma concentrations of dextromethorphan.
Alcohol may increase the side effects of dextromethorphan.
Special Considerations for Use
Do not exceed the recommended dose.
Keep the medication out of sight and out of reach of children.
If erythrocyte hemolysis or drug-induced hemolytic anemia occurs while taking Milistan Multisymptomatic, the medication must be discontinued immediately.
If a skin rash develops, discontinue use of the medication.
During long-term use, liver and kidney function, as well as the condition of the hematopoietic system, should be monitored. If symptoms persist, consult a doctor.
If the condition is caused by a bacterial infection, concurrent treatment with antibiotics is recommended.
Do not consume alcohol while taking this medication!
Related to acetaminophen.
If you have liver or kidney disease, consult a doctor before using this medication.
Consult a doctor before taking this medication if the patient is taking warfarin or similar medications with anticoagulant effects. Note that patients with non-cirrhotic alcohol-induced liver damage are at increased risk of paracetamol-induced hepatotoxicity; this medication may affect the results of laboratory tests for blood glucose and uric acid levels. Patients who take analgesics daily for mild arthritis should consult a doctor. In patients with severe infections, such as sepsis, which are accompanied by decreased glutathione levels, the risk of metabolic acidosis increases when taking paracetamol. Symptoms of metabolic acidosis include deep, rapid, or labored breathing, nausea, vomiting, and loss of appetite. Seek immediate medical attention if these symptoms occur.
Cases of metabolic acidosis with a high anion gap due to pyroglutamic acidosis have been reported in patients with severe illnesses, such as severe renal failure and sepsis, or in patients who were malnourished or had other causes of glutathione deficiency (e.g., chronic alcoholism), and who were treated with paracetamol at therapeutic doses over a prolonged period or with a combination of paracetamol and flucloxacillin. If metabolic acidosis with a high anion gap is suspected due to pyroglutamic acidosis, it is recommended to immediately discontinue paracetamol and closely monitor the patient’s condition. Measuring urinary 5-oxoproline levels may be helpful in identifying pyroglutamic acidosis as the underlying cause of metabolic acidosis with a high anion gap in patients with multiple risk factors.
Do not take this medication at the same time as other products containing acetaminophen.
If symptoms persist, consult a doctor.
If headaches become persistent, consult a doctor.
Related to cetirizine hydrochloride.
When taken at therapeutic doses, no clinically significant interactions with alcohol were observed (at blood alcohol levels of 0.5 g/L). However, it is recommended to avoid concomitant use of this medication with alcohol. Caution is advised when prescribing this medication to patients with epilepsy and to patients at risk of seizures.
Use with caution in patients prone to urinary retention (spinal cord injury, prostatic hyperplasia), as cetirizine may increase the risk of urinary retention.
Antihistamines suppress skin allergy tests; therefore, before conducting such a test, the medication must be discontinued 3 days prior to the test (elimination period).
Regarding chlorpheniramine maleate
Chlorpheniramine, like other drugs with anticholinergic effects, should be used with caution in patients with epilepsy; high intraocular pressure, including glaucoma; prostatic hypertrophy; severe hypertension or cardiovascular disease; bronchitis, bronchiectasis, or asthma; and hepatic or renal insufficiency. In children and elderly patients, adverse reactions affecting the nervous system—such as anticholinergic effects and paradoxical excitation (increased energy, restlessness, nervousness)—may occur more frequently during chlorpheniramine therapy.
The anticholinergic properties of chlorpheniramine may cause drowsiness, dizziness, blurred vision, and impaired psychomotor reactions in some patients, which may seriously affect the ability to operate vehicles and machinery.
Concomitant use of chlorpheniramine with alcohol should be avoided, as the effects of alcohol are potentiated.
Chlorpheniramine should not be used with other antihistamines.
Related to dextromethorphan hydrobromide
Patients with a chronic cough caused by smoking or bronchial asthma, or a cough resulting from an acute asthma attack, should consult a doctor before using dextromethorphan hydrobromide. A doctor’s consultation is also required before using this medication in patients whose cough is accompanied by excessive phlegm production.
If the cough lasts longer than 7 days or is accompanied by fever, rash, or headache, the patient must be properly examined to identify the underlying cause.
There have been reports of cases of dextromethorphan hydrobromide abuse. This must be taken into account when prescribing the medication to adolescents and young adults, as well as to patients with a history of abuse of narcotics or psychotropic substances.
Dextromethorphan is metabolized in the liver by cytochrome P450 2D6. The activity of this enzyme is genetically determined. Approximately 10% of the general population are slow metabolizers of the CYP2D6 enzyme. In such individuals, as well as in patients receiving therapy with CYP2D6 inhibitors, signs of overdose and/or prolonged effects of dextromethorphan may occur. Therefore, caution should be exercised when administering the drug to patients who are slow metabolizers of CYP2D6 or who are taking CYP2D6 inhibitors.
Excipients.
The drug contains methylparaben (E 218) and propylparaben (E 216), which may cause allergic reactions (possibly delayed).
Use During Pregnancy or Breastfeeding
Pregnancy
This medication should not be used during pregnancy.
Breastfeeding
It is advisable to avoid using this medication while breastfeeding; however, if use of the medication is necessary, you should consider discontinuing breastfeeding.
Data on acetaminophen:
There are no standard studies using currently accepted standards for assessing reproductive and ontogenetic toxicity.
Extensive data on pregnant women indicate neither teratogenicity nor fetal/neonatal toxicity. Epidemiological studies of nervous system development in children exposed to paracetamol in utero have not yielded conclusive results.
Effect on reaction time when driving or operating machinery
If neurological disorders (drowsiness, dizziness, visual disturbances) occur, you must refrain from driving or operating machinery.
Dosage and Administration
Adults and children over 12 years of age should take 1 lozenge orally once daily. The maximum duration of treatment is 5–7 days.
The maximum duration of use for children without consulting a doctor is 3 days.
Patients with moderate renal insufficiency should take half the recommended dose.
For elderly patients with normal renal function, no dose adjustment is necessary.
Children
Contraindicated in children under 12 years of age.
Overdose
Symptoms.
The signs and symptoms of an overdose of individual components of Milistan Multisymptomatic can be categorized as follows:
Related to acetaminophen.
Liver damage is possible in adults who have taken 10 g or more of paracetamol and in children who have taken more than 150 mg/kg of body weight. In patients with risk factors (long-term use of carbamazepine, phenobarbital, phenytoin, primidone, rifampicin, St. John’s wort, or other drugs that induce liver enzymes; alcohol abuse; or glutathione system deficiency, such as digestive disorders, HIV infection, starvation, cystic fibrosis, or cachexia), taking 5 g or more of acetaminophen may lead to liver damage.
Symptoms of overdose within the first 24 hours include pallor, nausea, vomiting, loss of appetite, and abdominal pain. Liver damage may become apparent 12–48 hours after overdose. Glucose metabolism disorders and metabolic acidosis may occur. In severe poisoning, liver failure may progress to encephalopathy, hemorrhages, hypoglycemia, coma, and may be fatal. Acute renal failure with acute tubular necrosis may manifest as severe lower back pain, hematuria, and proteinuria, and may develop even in the absence of severe liver damage. Cardiac arrhythmia and pancreatitis have also been reported.
With prolonged use of the drug in high doses, the hematopoietic system may be affected, leading to aplastic anemia, pancytopenia, agranulocytosis, neutropenia, leukopenia, and thrombocytopenia. When taking high doses, the following may occur in the central nervous system: dizziness, psychomotor agitation, and disorientation; and nephrotoxicity (renal colic, interstitial nephritis, capillary necrosis) may occur in the urinary system.
These are associated with cetirizine hydrochloride.
Cetirizine overdose is primarily associated with effects on the CNS or with effects that may indicate anticholinergic activity. Side effects reported after taking a dose at least 5 times higher than the recommended daily dose include: confusion, diarrhea, dizziness, fatigue, headache, malaise, mydriasis, pruritus, restlessness, sedation, drowsiness, stupor, tachycardia, tremor, and urinary retention.
Associated with chlorpheniramine maleate.
The estimated lethal dose of chlorpheniramine is 25 to 50 mg/kg of body weight. In case of overdose, the condition may range from depression to agitation (restlessness and convulsions). Atropine-like symptoms may occur, including mydriasis, photophobia, dryness of the skin and mucous membranes, increased body temperature, and intestinal atony; CNS depression is accompanied by respiratory disturbances and cardiovascular dysfunction.
Associated with dextromethorphan hydrobromide
Symptoms of dextromethorphan hydrobromide overdose include nausea and vomiting, CNS depression, dizziness, dysarthria, ataxia, blurred vision, myoclonus, nystagmus, drowsiness, tremor, agitation, hyperactivity, confusion, psychotic disorders (psychosis), and respiratory depression.
Treatment
In case of overdose, immediate medical attention is required. The patient should be taken to a hospital immediately, even if there are no early symptoms of overdose. Symptoms may be limited to nausea and vomiting or may not reflect the severity of the overdose or the risk of organ damage. Treatment with activated charcoal should be considered if an excessive dose of the drug was taken within 1 hour. Plasma paracetamol concentrations should be measured 4 hours or more after ingestion (earlier measurements are unreliable). Treatment with N-acetylcysteine may be administered within 24 hours after ingestion, but the maximum protective effect is achieved when administered within 8 hours after ingestion.
The effectiveness of the antidote decreases sharply after this time. If necessary, N-acetylcysteine should be administered intravenously to the patient in accordance with current guidelines. In the absence of vomiting, oral methionine may be used as an appropriate alternative in remote areas outside of a hospital setting.
In addition to the above, symptomatic or supportive therapy is recommended.
Side Effects
Skin and subcutaneous tissue disorders: skin rashes, including generalized, maculopapular, and erythematous rashes; urticaria, mucosal eruptions, erythema, pruritus, angioedema, erythema multiforme, Stevens-Johnson syndrome, toxic epidermal necrolysis, persistent drug-induced erythema, angioedema, exfoliative dermatitis, photosensitivity.
Immune system disorders: hypersensitivity reactions, including allergic reactions, anaphylaxis, anaphylactic reactions, anaphylactic shock, pruritus, skin and mucosal rashes (usually generalized, erythematous, or urticarial), angioedema, erythema multiforme (including Stevens-Johnson syndrome), toxic epidermal necrolysis (Lyell’s syndrome).
Gastrointestinal: dyspeptic disorders, gastrointestinal disorders, nausea, vomiting, epigastric pain, abdominal pain, dry mouth, diarrhea, gastritis, heartburn, loose stools, constipation, flatulence.
Hepatobiliary system: impaired liver function, elevated levels of “liver” enzymes (transaminases, alkaline phosphatase, GGT), usually without the development of jaundice, hyperbilirubinemia, hepatitis, jaundice. With prolonged use, especially at high doses, hepatotoxic effects cannot be ruled out.
Endocrine system: hypoglycemia, up to hypoglycemic coma.
Metabolic disorders: increased appetite, anorexia, metabolic acidosis with a high anion gap (frequency unknown).
Blood and lymphatic system disorders: anemia, sulfhemoglobinemia, and methemoglobinemia (cyanosis, shortness of breath, chest pain), aplastic anemia, hemolytic anemia; agranulocytosis, thrombocytopenia, leukopenia, bruising or bleeding, abnormal blood counts.
Respiratory system: pharyngitis, rhinitis, bronchospasm in patients sensitive to acetylsalicylic acid and other NSAIDs, nasal congestion, thickening of the bronchial walls due to increased bronchial secretion.
Neurological system: dizziness, headache, possible paradoxical central nervous system stimulation, agitation, sedative effect, paresthesia, convulsions, movement disorders, dysgeusia, loss of consciousness, syncope, tremor, muscle tone disturbances (dystonia), dyskinesia, coordination disorders, increased fatigue, confusion, anxiety, nervousness, tremor, irritability, insomnia, euphoria, paresthesia, neurosis, neuritis, convulsions; drowsiness, coma, behavioral changes, memory impairment, amnesia, attention disorders.
Ear and balance disorders: vertigo, dizziness, impaired coordination, ringing in the ears, tinnitus, acute labyrinthitis.
Urinary system: difficulty and delay in urination (see the “Special Considerations for Use” section), dysuria, enuresis.
Ocular system: impaired accommodation, blurred vision, decreased visual acuity, involuntary eye movements, clouding of vision, double vision, increased intraocular pressure, mydriasis, photophobia.
Psychiatric disorders: nervous agitation, confusion, irritability, anxiety, aggression, confusion, depression, suicidal thoughts, hallucinations, insomnia, drowsiness, nightmares, and nervous tics.
Cardiovascular system: tachycardia, arrhythmia, sensation of a rapid heartbeat, fluctuations in blood pressure, hypotension.
Musculoskeletal and connective tissue disorders: muscle twitching, muscle weakness.
General disorders: asthenia, increased fatigue, malaise, edema, feeling of tightness in the chest.
Laboratory findings: weight gain.
Reproductive system: menstrual irregularities; impotence.
Other: dry mucous membranes, increased sweating, increased fatigue.
Description of Individual Adverse Reactions
Metabolic acidosis with a high anion gap. Cases of metabolic acidosis with a high anion gap due to pyroglutamic acidosis have been observed in patients with risk factors who were taking acetaminophen (see the “Special Considerations” section). Pyroglutamic acidosis may occur due to low glutathione levels in these patients.
Shelf life
3 years.
Storage conditions
Store at a temperature not exceeding 25 °C in the original packaging, out of reach of children.
Packaging
12 tablets per blister pack in a cardboard box.
Dispensing Category
Available without a prescription.
Manufacturer
IxEl Laboratories Pvt. Ltd.
Manufacturer’s location and business address: E-1223, Phase I, Extn. (Ghatal) RIICO Industrial Area, Bhiwadi, Alwar Dist. (Rajasthan), India.
Applicant
Mili Healthcare Limited.
Location of the applicant: 2nd Floor, Office Space, 4 Chartfield House, Castle Street, Tonton, Somerset, England, TA1 4AS, United Kingdom.