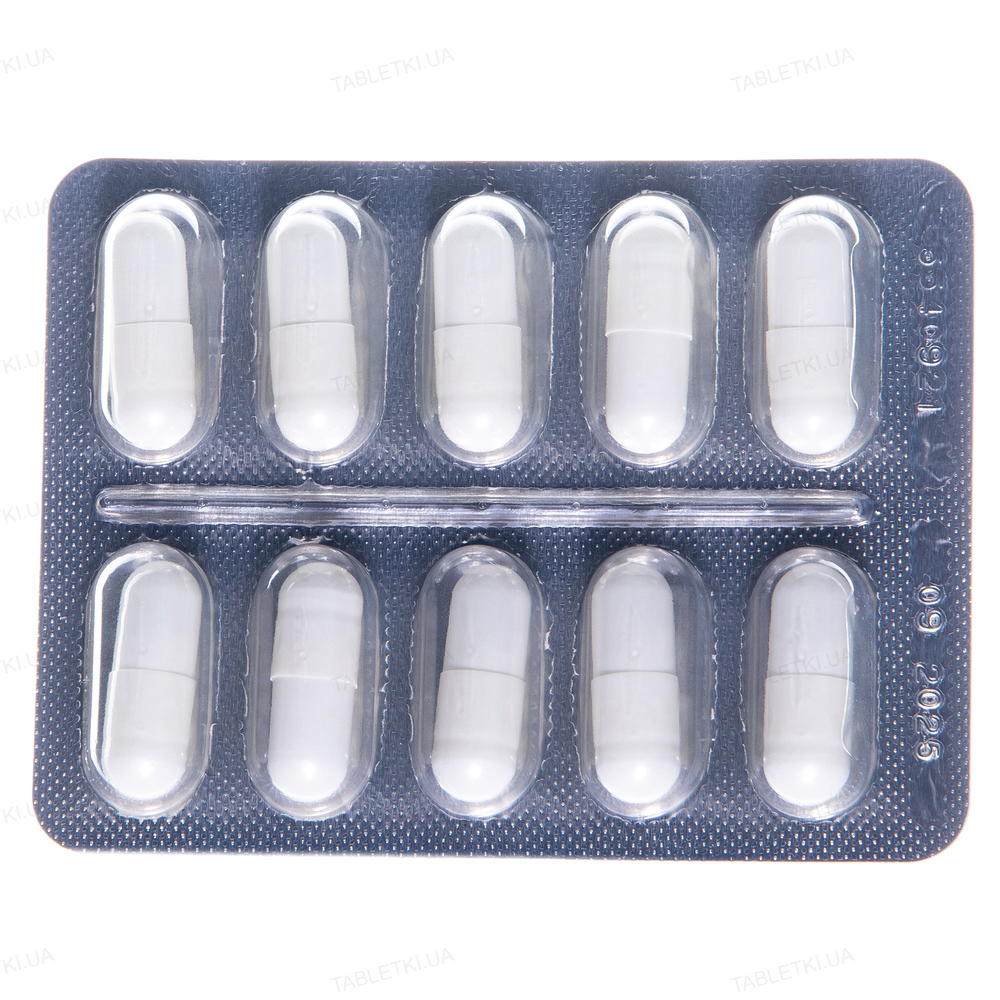
Mildronate Hard Capsules, 250 mg, No. 40 (10 x 4)
Ingredients
Active ingredient: meldonium;
1 hard capsule contains 250 mg of meldonium dihydrate;
excipients: potato starch, silicon dioxide, calcium stearate;
Capsule (body and cap): titanium dioxide (E 171), gelatin.
Dosage Form
Hard capsules.
Main physical and chemical properties: white hard gelatin capsules. The capsule contents are a white crystalline powder with a faint odor. The powder is hygroscopic.
Pharmacotherapeutic group
Other cardiovascular drugs. ATC code C01E B22.
Pharmacological properties
Pharmacodynamics.
Meldonium is a precursor of carnitine and a structural analog of gamma-butyrobetaine (GBB), in which one carbon atom is replaced by a nitrogen atom. Its effect on the body can be explained in two ways.
1. Effect on carnitine biosynthesis.
By reversibly inhibiting gamma-butyrobetaine hydroxylase, meldonium reduces carnitine biosynthesis and thus impedes the transport of long-chain fatty acids across cell membranes, thereby preventing the accumulation within cells of a potent detergent—the activated forms of unoxidized fatty acids. This prevents damage to cell membranes.
When carnitine concentrations decrease under ischemic conditions, fatty acid beta-oxidation is delayed and oxygen consumption in cells is optimized, glucose oxidation is stimulated, and the transport of adenosine triphosphate (ATP) from its sites of biosynthesis (mitochondria) to its sites of consumption (cytosol) is restored. Essentially, cells are supplied with nutrients and oxygen, and the consumption of these substances is optimized.
In turn, as the biosynthesis of the carnitine precursor—GBA—increases, NO synthase is activated, resulting in improved blood rheological properties and reduced peripheral vascular resistance.
When the concentration of meldonium decreases, carnitine biosynthesis increases again, and the amount of fatty acids in the cells gradually rises.
It is believed that the efficacy of meldonium is based on an increase in tolerance to cellular stress (as a result of changes in fatty acid levels).
2. Mediator function in the hypothetical GBB-ergic system.
A hypothesis has been proposed that the body contains a system for transmitting neural signals—the GBB-ergic system—which facilitates the transmission of nerve impulses between cells. The mediator of this system is the final precursor of carnitine—GBB ester. As a result of the action of GBB esterase, the mediator donates an electron to the cell, thereby transmitting an electrical impulse, and is itself converted into GBB. The hydrolyzed form of GBB is then actively transported to the liver, kidneys, and ovaries, where it is converted into carnitine. In somatic cells, new GBB molecules are synthesized in response to stimulation, ensuring signal propagation.
A decrease in carnitine concentration stimulates GBB synthesis, resulting in an increase in GBB ester concentration.
Meldonium, as noted earlier, is a structural analog of GBB and can act as a “mediator.” In contrast, GBB hydroxylase “does not recognize” meldonium, so the concentration of carnitine does not increase but rather decreases. Thus, meldonium—both by acting as a “mediator” itself and by promoting an increase in GBB concentration—triggers the corresponding physiological response. As a result, overall metabolic activity also increases in other systems, such as the central nervous system (CNS).
Effects on the CNS.
Animal studies have demonstrated meldonium’s antihypoxic effects and its ability to promote cerebral blood flow. Meldonium optimizes the redistribution of cerebral blood flow toward ischemic areas and increases neuronal resilience under hypoxic conditions.
Meldonium has a stimulating effect on the CNS—increasing motor activity and physical endurance, stimulating behavioral responses, and exerting an anti-stress effect — stimulation of the sympathetic-adrenal system, accumulation of catecholamines in the brain and adrenal glands, and protection of internal organs from stress-induced changes.
Efficacy in neurological disorders.
The rehabilitation process for patients with neurological disorders (following cerebrovascular diseases, brain surgery, trauma, or tick-borne encephalitis) has been studied.
The results of testing meldonium’s therapeutic activity indicate its dose-dependent positive effect on physical endurance and the restoration of functional independence during the recovery period.
An analysis of changes in individual and overall cognitive functions following administration of the drug revealed a positive effect on the recovery process of cognitive functions during the convalescence period.
It has been established that meldonium improves the quality of life during convalescence (primarily due to the restoration of the body’s physical function); furthermore, it helps eliminate mental disorders.
Meldonium has a positive effect on nervous system function—reducing disorders in patients with neurological deficits during the recovery period.
The overall neurological condition of patients improves (reduction in brain nerve damage and reflex abnormalities, regression of paresis, and improvement in motor coordination and autonomic functions).
Pharmacokinetics.
Absorption
After a single oral dose of meldonium at doses of 25, 50, 100, 200, 400, 800, or 150 mg, the maximum plasma concentration (Cmax) and the area under the time-concentration curve (AUC) increase proportionally to the administered dose. The time to reach maximum plasma concentration (tmax) is 1–2 hours. With repeated dosing, steady-state plasma concentrations are achieved 72–96 hours after the first dose. Accumulation of meldonium in plasma is possible. Food slightly delays the absorption of meldonium without altering Cmax or AUC values.
Distribution
Meldonium is rapidly distributed from the bloodstream into tissues. Plasma protein binding increases over time following administration. Meldonium and its metabolites partially cross the placental barrier. Animal studies have shown that meldonium is excreted into breast milk.
Biotransformation
Studies of metabolism in experimental animals have shown that meldonium is primarily metabolized in the liver.
Elimination
Renal excretion plays a significant role in the elimination of meldonium and its metabolites from the body. The half-life of meldonium (t1/2) is approximately 4 hours. The half-life varies when repeated doses are administered.
Special Patient Populations
Elderly patients
For elderly patients with impaired liver or kidney function, who may experience increased bioavailability, the dose of meldonium should be reduced.
Renal impairment
Patients with renal impairment, in whom bioavailability is increased, should have their meldonium dose reduced. Nonclinical studies have shown that when administered orally to animals at doses of 20, 100, and 500 mg/kg, meldonium is low in toxicity and does not affect renal function. There is an interaction between the renal reabsorption of meldonium or its metabolites (e.g., 3-hydroxymeldonium) and carnitine, resulting in increased renal clearance of carnitine. There is no direct effect of meldonium, GBB, or the meldonium/GBB combination on the renin-angiotensin-aldosterone system.
Liver dysfunction
In patients with impaired liver function, who experience increased bioavailability, the dose of meldonium should be reduced. In animal toxicity studies, administration of meldonium at doses exceeding 100 mg/kg resulted in yellow discoloration of the liver and lipid denaturation. In histopathological studies in animals following administration of high doses of meldonium (400 mg/kg and 1,600 mg/kg), lipid accumulation in liver cells was observed. No changes in liver function tests were observed in humans following administration of high doses of 400–800 mg. The possibility of lipid infiltration into liver cells cannot be ruled out.
Children
There are no data on the safety and efficacy of meldonium in children (under 18 years of age); therefore, the use of this drug in this patient population is contraindicated.
Indications
As part of combination therapy in the following cases:
- reduced performance capacity, physical and psychoemotional overexertion;
- during the recovery period following cerebrovascular disorders, head injuries, and encephalitis.
Contraindications
- Hypersensitivity to meldonium and/or to any excipient in the medication;
- increased intracranial pressure (due to impaired venous outflow or intracranial tumors);
- severe hepatic and/or renal insufficiency (insufficient data on safety of use);
- children under 18 years of age;
- pregnancy;
- breastfeeding.
Drug Interactions and Other Interactions
Meldonium may be used in combination with long-acting nitrates and other antianginal agents, cardiac glycosides, and diuretics. It can also be combined with anticoagulants, antiplatelet agents, antiarrhythmic drugs, and other medications that improve microcirculation.
Meldonium may enhance the effects of drugs containing glyceryl trinitrate, nifedipine, beta-blockers, other antihypertensives, and peripheral vasodilators.
When meldonium is used concomitantly with lisinopril, a positive effect of the combination therapy has been observed (vasodilation of the major arteries, improvement in peripheral blood flow and quality of life, and reduction in mental and physical stress).
When meldonium is used in combination with orotic acid to reverse damage caused by ischemia/reperfusion, an additional pharmacological effect is observed.
Concomitant use of iron supplements and meldonium in patients with iron-deficiency anemia improved the fatty acid composition of red blood cells.
Meldonium helps reverse pathological changes in the heart caused by azidothymidine (AZT), and indirectly influences AZT-induced oxidative stress reactions that lead to mitochondrial dysfunction. The use of meldonium in combination with azidothymidine or other antiretroviral drugs has a positive effect in the treatment of acquired immunodeficiency syndrome (AIDS). In a test of ethanol-induced loss of the balance reflex, meldonium reduced the duration of sleep. During seizures induced by pentylentetrazol, meldonium was found to have a pronounced anticonvulsant effect. In turn, when the alpha-2 adrenergic blocker yohimbine at a dose of 2 mg/kg and the nitric oxide synthase inhibitor (NOS) N-(G)-nitro-L-arginine at a dose of 10 mg/kg completely blocked the anticonvulsant effect of meldonium.
An overdose of meldonium may exacerbate the cardiotoxicity caused by cyclophosphamide.
Carnitine deficiency resulting from meldonium use may exacerbate the cardiotoxicity caused by ifosfamide.
Meldonium has a protective effect against cardiotoxicity caused by indinavir and neurotoxicity caused by efavirenz.
Do not use meldonium capsules together with other medications containing meldonium, as this increases the risk of adverse reactions.
Special Considerations for Use
Caution is advised when administering this medication to patients with a history of mild to moderate liver and/or kidney dysfunction (liver and/or kidney function should be monitored).
Use during pregnancy or breastfeeding.
Pregnancy. Animal studies are insufficient to assess the effects of meldonium on pregnancy, embryonic/fetal development, labor, and postnatal development. The potential risk to humans is unknown; therefore, meldonium is contraindicated during pregnancy.
Breastfeeding. Available data from animal studies indicate that meldonium passes into breast milk. It is unknown whether meldonium passes into human breast milk. A risk to newborns/infants cannot be ruled out; therefore, meldonium is contraindicated during breastfeeding.
Effect on reaction time when operating motor vehicles or other machinery.
No studies have been conducted to assess the effect on the ability to drive or operate machinery.
Dosage and Administration
For oral use. Swallow the capsules with water. Take the medication orally before or after meals. Due to its potential stimulating effect, it is recommended to take the medication in the morning.
Adults
The dose is 500 mg per day (2 capsules of 250 mg each). The daily dose may be taken all at once or divided into two doses. The maximum daily dose is 500 mg.
The duration of treatment is 4–6 weeks. The course of treatment may be repeated 2–3 times a year.
Elderly Patients
Elderly patients with impaired liver and/or kidney function may require a reduced dose of meldonium.
Patients with Renal Impairment
Since the drug is excreted by the kidneys, patients with mild to moderate renal impairment should receive a lower dose of meldonium.
Patients with liver impairment
Patients with mild to moderate hepatic impairment should receive a lower dose of meldonium.
Children. There are no data on the safety and efficacy of meldonium in children (under 18 years of age); therefore, the use of meldonium in this patient population is contraindicated.
Overdose
No cases of meldonium overdose have been reported. The drug is low-toxicity and does not cause life-threatening side effects.
If blood pressure drops, headaches, dizziness, tachycardia, and general weakness may occur. Treatment is symptomatic.
In cases of severe overdose, liver and kidney function must be monitored.
Hemodialysis is not significantly effective in cases of meldonium overdose due to its high binding to blood proteins.
Side Effects
Meldonium is generally well tolerated.
Side effects are classified by organ system and frequency of occurrence according to MedDRA: common (≥1/100 to <1/10), rare (≥1/10,000 to <1/1,000).
Adverse effects observed in clinical trials and during the postmarketing period:
| Immune system | |
| Common
Rare |
Allergic reactions*
Hypersensitivity, including allergic dermatitis, urticaria, angioedema, and anaphylactic reactions up to shock |
| Psychiatric | |
| Rare | Agitation, anxiety, obsessive thoughts, sleep disturbances |
| Nervous system | |
| Common
Rare |
Headaches *
Paresthesia, tremor, hypoesthesia, tinnitus, vertigo, dizziness, gait disturbance, presyncope, syncope |
| Cardiac | |
| Rare | Changes in heart rhythm, palpitations, tachycardia / sinus tachycardia, atrial fibrillation, arrhythmia, chest discomfort / chest pain |
| Cardiovascular system | |
| Rare | Increased/decreased blood pressure, hypertensive crisis, flushing, pallor |
| Respiratory, thoracic, and mediastinal disorders | |
| Common
Rare |
Respiratory tract infections
Sore throat, cough, dyspnea, apnea |
| Gastrointestinal system | |
| Common
Rare |
Dyspepsia *
Dysgeusia (metallic taste in the mouth), loss of appetite, nausea, vomiting, flatulence, diarrhea, abdominal pain, dry mouth, or hypersalivation |
| Skin and subcutaneous tissue | |
| Rare | Rash, generalized/maculopapular rash, itching |
| Musculoskeletal system | |
| Rare | Back pain, muscle weakness, muscle spasms |
| Renal and urinary system | |
| Rare | Pollakiuria |
| General disorders and administration site conditions | |
| Rare | General weakness, chills, asthenia, edema, facial edema, leg edema, sensation of heat, sensation of cold, cold sweat |
| Examination | |
| Common
Rare |
Dyslipidemia, elevated C-reactive protein levels
Abnormal electrocardiogram (ECG), tachycardia, eosinophilia * |
* Side effects observed in previously conducted uncontrolled clinical trials.
Shelf life
4 years.
Do not use after the expiration date.
Storage conditions
Store at a temperature not exceeding 25 °C.
Store in the original packaging to protect from moisture.
Keep out of reach of children.
Packaging
10 capsules per blister pack; 2 or 4 blister packs per cardboard box.
Dispensing Category
Over-the-counter.
Manufacturer
JSC “Grindeks,” Latvia.
Manufacturer’s location and business address.
53 Krustpils St., Riga, LV-1057, Latvia.
Applicant
JSC “Grindeks.”
Location of the applicant.
53 Krustpils St., Riga, LV-1057, Latvia.
Phone/Fax: +371 67083205 / +371 67083505
Email: grindeks@grindeks.lv