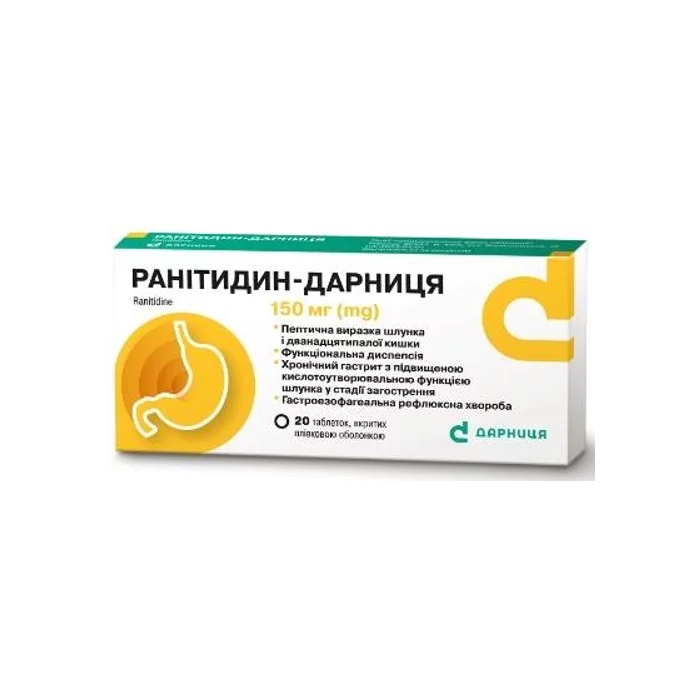
Ranitidine-Darnitsa 150 mg Tablets, No. 20
Ranitidine-Darnitsa: Instructions for Use
Composition
Active ingredient: ranitidine;
1 tablet contains:
- 150 mg of ranitidine hydrochloride, equivalent to 150 mg of ranitidine;
Excipients: microcrystalline cellulose, povidone, lactose monohydrate, potato starch, talc, magnesium stearate, Opadry AMB 80 W yellow.
Dosage Form
Main physical and chemical properties: round, biconvex, film-coated tablets, yellow to yellow-orange in color. Two layers are visible on cross-section.
Pharmacotherapeutic group
Agents for the treatment of peptic ulcers and gastroesophageal reflux disease. H2-histamine receptor antagonists. Ranitidine. ATC code A02B A02.
Pharmacological Properties
Pharmacodynamics.
Ranitidine is an antiulcer agent and an H2-histamine receptor antagonist.
Its mechanism of action is based on competitive inhibition of H2-histamine receptors on the membranes of parietal cells in the gastric mucosa. It reduces basal and stimulated secretion of hydrochloric acid, thereby decreasing the volume of gastric juice produced in response to stimulation of baroreceptors (gastric distension), food intake, and the action of hormones and biogenic stimulants (gastrin, histamine, pentagastrin, caffeine). Ranitidine reduces the amount of hydrochloric acid in gastric juice, does not affect the concentration of gastrin in blood plasma, nor does it affect mucus production. Ranitidine is characterized by a prolonged action.
Ranitidine does not affect the cytochrome P450 enzyme system in the liver.
Pharmacokinetics.
After oral administration, ranitidine is rapidly absorbed in the gastrointestinal tract. Bioavailability is approximately 50%. Maximum blood concentration is reached in 2–3 hours and is 478 ng/mL. It is partially metabolized in the liver to N-oxide (the major metabolite, 4% of the dose), S-oxide, and is demethylated.
The half-life (after oral administration) is 2–3 hours with normal creatinine clearance and 8–9 hours with reduced creatinine clearance (20–30 mL/min). It is excreted by the kidneys within 24 hours; approximately 30% of the orally administered dose is excreted unchanged.
It crosses histohematological barriers, including the placental barrier, but crosses the blood-brain barrier poorly. Significant concentrations are detected in breast milk. The rate and extent of elimination depend little on liver function and are primarily related to renal function.
Clinical Characteristics.
Indications
- Peptic ulcer of the stomach and duodenum not associated with Helicobacter pylori (in the acute phase), including ulcers associated with the use of nonsteroidal anti-inflammatory drugs (NSAIDs);
- functional dyspepsia;
- chronic gastritis with increased gastric acid secretion in the acute phase;
- gastroesophageal reflux disease (to relieve symptoms) or reflux esophagitis.
Contraindications for Ranitidine-Darnitsa
Hypersensitivity to ranitidine or any other components of the drug; presence of malignant gastric diseases, a history of liver cirrhosis with portosystemic encephalopathy, liver failure, severe renal failure (creatinine clearance < 30 mL/min).
Drug Interactions and Other Interactions
Ranitidine may affect the absorption, metabolism, and renal excretion of other medications.
At therapeutic doses, ranitidine does not alter the activity of the cytochrome P450 enzyme system and does not potentiate the effects of drugs metabolized by this system (diazepam, lidocaine, phenytoin, propranolol, theophylline).
By altering gastric acidity, ranitidine may affect the bioavailability of certain drugs. This leads either to increased absorption (triazolam, midazolam, glipizide) or to decreased absorption (ketoconazole, itraconazole, atazanavir, gefitinib).
Antacids and sucralfate slow the absorption of ranitidine; therefore, the interval between taking these medications and ranitidine should be at least 1–2 hours.
Concomitant use with metoprolol may lead to increased serum concentrations of metoprolol.
When used concomitantly with coumarin anticoagulants (warfarin), ranitidine may alter prothrombin time (monitoring of prothrombin time is recommended).
High doses of ranitidine may slow the excretion of procainamide and N-acetylprocainamide, leading to increased plasma levels of these drugs.
There are no data on interactions between ranitidine and amoxicillin or metronidazole.
Smoking reduces the effectiveness of ranitidine.
Special Considerations for Use
If a patient is allergic to other medications in the histamine H2-receptor blocker class, allergic reactions to ranitidine are possible; therefore, the drug should be used with caution in patients with hypersensitivity to other medications in this class.
Use this medication with caution in patients with acute porphyria (including a history of the condition), immunodeficiency, or phenylketonuria.
Ranitidine is excreted by the kidneys; therefore, plasma levels are elevated in patients with severe renal insufficiency (see dosage recommendations for such patients in the “Dosage and Administration” section).
In elderly patients with impaired liver or kidney function, confusion may occur, necessitating a dose reduction.
Treatment with ranitidine may mask the symptoms of gastric carcinoma; therefore, the presence of malignant tumors in the stomach should be ruled out before starting treatment.
Regular monitoring is required for patients (especially the elderly and those with a history of peptic ulcer disease of the stomach and/or duodenum) who are taking ranitidine in combination with NSAIDs.
When administered concomitantly with theophylline, plasma theophylline levels must be monitored and the dosage adjusted.
Elderly patients, individuals with chronic lung disease, diabetes mellitus, or those with compromised immune systems have shown an increased susceptibility to developing community-acquired pneumonia.
Treatment with ranitidine should be discontinued gradually due to the risk of a “rebound” syndrome if discontinued abruptly.
Ranitidine should not be used in patients with hepatic insufficiency.
Important information about excipients.
This medication contains lactose, which should be taken into account by patients with rare hereditary forms of galactose intolerance, lactase deficiency, or glucose-galactose malabsorption.
If a patient has been diagnosed with an intolerance to certain sugars, they should consult a doctor before taking this medication.
Use During Pregnancy or Breastfeeding
This medication is contraindicated during pregnancy.
If use of the medication is necessary, breastfeeding should be discontinued.
Effect on reaction time when driving or operating machinery
Since adverse reactions (dizziness, hallucinations, accommodation disorders) may occur in sensitive patients when taking this medication, patients should refrain from driving or operating machinery while taking this medication.
Dosage and Administration of Ranitidine-Darnitsa
Prescribe to adults and children 12 years of age and older. Take orally without chewing, with a small amount of water, regardless of meals.
Peptic ulcer of the stomach and duodenum not associated with Helicobacter pylori (during the acute phase). Administer 150 mg (1 tablet) twice daily, in the morning and evening, or 300 mg (2 tablets) once at night for 4 weeks. For non-healed ulcers, continue treatment for the next 4 weeks.
Prevention of peptic ulcers of the stomach and duodenum associated with NSAID use. Administer 150 mg (1 tablet) twice daily, in the morning and evening, for the duration of NSAID therapy.
Functional dyspepsia. Administer 150 mg (1 tablet) twice daily, in the morning and in the evening, for 2–3 weeks.
Chronic gastritis with increased gastric acid secretion during the acute phase. Administer 150 mg (1 tablet) twice daily, in the morning and in the evening, for 2–4 weeks.
Gastroesophageal reflux disease. To relieve symptoms, administer 150 mg (1 tablet) twice daily, in the morning and in the evening, for 2 weeks; continue treatment if necessary.
For long-term treatment and during exacerbations of gastroesophageal reflux disease, prescribe 150 mg (1 tablet) twice daily, in the morning and in the evening, or 300 mg (2 tablets) once daily at night for 8 weeks; if necessary, extend the course of treatment to 12 weeks.
Patients with severe renal impairment (creatinine clearance <50 mL/min). The daily dose for this patient population is 1 tablet (150 mg of ranitidine).
Children
For children aged 12 years and older, the drug is indicated to shorten the duration of treatment for peptic ulcers of the stomach and duodenum, to treat gastroesophageal reflux disease, including reflux esophagitis, and to relieve the symptoms of gastroesophageal reflux disease.
Overdose
Side effects may be exacerbated.
Treatment: Provide appropriate symptomatic and supportive therapy as needed.
Ranitidine can be removed from the blood serum by hemodialysis.
Side Effects of Ranitidine-Darnitsa
- Ocular: blurred vision, accommodation disorders.
- Gastrointestinal system: dry mouth, nausea, vomiting, constipation, diarrhea, abdominal pain, flatulence, acute pancreatitis, decreased appetite, loss of appetite.
- Liver and biliary tract: transient and reversible changes in liver function tests (transaminases, gamma-glutamyltransferase, alkaline phosphatase, bilirubin), hepatocellular, cholestatic, or mixed hepatitis with or without jaundice (usually reversible).
- Renal and urinary system: impaired renal function, acute interstitial nephritis, elevated plasma creatinine levels.
- Nervous system disorders: headache (sometimes severe), dizziness, and reversible involuntary movement disorders.
- Psychiatric disorders: increased fatigue, reversible confusion, drowsiness, agitation, insomnia, emotional lability, restlessness, anxiety, depression, nervousness, hallucinations, tinnitus, irritability, disorientation, and confusion. These symptoms are observed primarily in critically ill or elderly patients.
- Cardiovascular system: decreased blood pressure, bradycardia, tachycardia, asystole, atrioventricular block, vasculitis, chest pain, arrhythmia, extrasystole.
- Blood and lymphatic system: leukopenia, reversible thrombocytopenia, agranulocytosis, or pancytopenia, sometimes with bone marrow hypoplasia or aplasia, neutropenia, immune hemolytic and aplastic anemia (usually reversible).
- Immune system disorders: hypersensitivity reactions, including urticaria, angioedema, anaphylactic shock, bronchospasm, erythema multiforme, exfoliative dermatitis, Stevens-Johnson syndrome, toxic epidermal necrolysis (Lyell’s syndrome), hyperthermia.
- Skin and subcutaneous tissue disorders: erythema, pruritus, skin rash, erythema multiforme, alopecia, dry skin.
- Musculoskeletal and connective tissue disorders: arthralgia, myalgia.
- Reproductive system and breast disorders: hyperprolactinemia, galactorrhea, gynecomastia, amenorrhea, decreased potency (reversible) and/or libido.
- General disorders: fever.
Reporting of Suspected Adverse Reactions.
Reporting suspected adverse reactions after a drug’s approval is an important procedure. It allows for continued monitoring of the benefit-risk profile of the drug in question. Healthcare professionals should report any suspected adverse reactions through the national reporting system.
Shelf life
2 years.
Storage Conditions
Store in the original packaging at a temperature not exceeding 25 °C. Keep out of the reach of children.
Packaging
10 tablets per blister pack; 1 or 2 blister packs per package.
Pharmacy Dispensing Category
By prescription.