Angelique tablets, coated, No. 28
Composition
Active ingredients: estradiol, drospirenone;
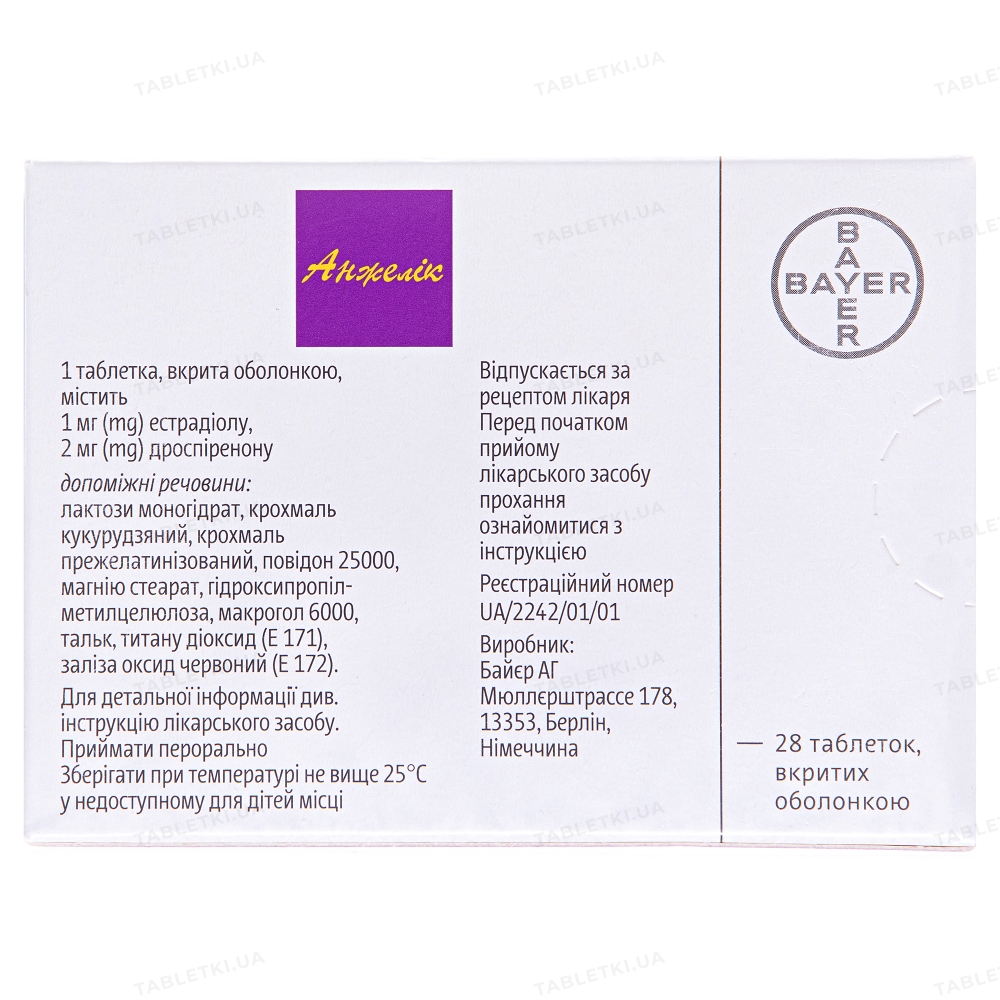
1 tablet contains 1.0 mg of estradiol (as estradiol hemihydrate) and 2.0 mg of drospirenone;
Excipients: lactose monohydrate, corn starch, pregelatinized starch, povidone 25,000, magnesium stearate, hydroxypropyl methylcellulose, polyethylene glycol 6,000, talc, titanium dioxide (E 171), red iron oxide (E 172).
Dosage Form
Film-coated tablets.
Main physical and chemical properties: round, biconvex, moderately red film-coated tablets, embossed with “DL” in a regular hexagon on one side.
Pharmacotherapeutic group
Sex hormones. Estrogen-progestin combinations.
ATC code G03F A17.
Pharmacological properties
Pharmacodynamics.
Estradiol.
Angelique contains synthetic 17β-estradiol, which is chemically and biologically identical to the estradiol produced in the human body. It compensates for the decrease in estrogen production in menopausal women and alleviates the symptoms of the postmenopausal period. Estrogens prevent bone loss following menopause or oophorectomy.
Drospirenone.
Drospirenone is a synthetic progestogen.
Since estrogens stimulate endometrial growth, estrogen monotherapy increases the risk of endometrial hyperplasia and endometrial cancer. The addition of a progestogen reduces, but does not completely eliminate, the estrogen-induced risk of endometrial hyperplasia in women with an intact uterus.
Drospirenone exhibits antagonistic activity against aldosterone. Therefore, increased sodium and water excretion and decreased potassium excretion may occur.
In preclinical studies, drospirenone did not exhibit estrogenic, glucocorticoid, or anti-glucocorticoid activity.
Data obtained from clinical studies.
- Reduction in symptoms of estrogen deficiency and improvement in bleeding patterns.
A reduction in menopausal symptoms was achieved within the first few weeks of treatment. Amenorrhea was observed in 73% of women during 10–12 months of treatment. Menstrual-like bleeding and/or spotting occurred in 59% of women during the first three months of therapy and in 27% of women during 10–12 months of treatment.
- Prevention of Osteoporosis.
Estrogen deficiency during menopause is associated with an increased rate of bone remodeling and a decrease in bone mass. The effect of estrogen on bone mineral density is dose-dependent. Effective protection is provided throughout the treatment period. After discontinuation of hormone replacement therapy (HRT), bone mass loss occurs at the same rate as in women who did not receive treatment.
Results from the WHI study and data from a meta-analysis of other studies show that the use of HRT, primarily in healthy women, either alone or in combination with a progestin, reduces the risk of hip, vertebral, and other osteoporosis-related fractures. HRT may also prevent fractures in women with low bone mineral density and/or osteoporosis; however, the data supporting this are limited.
After 2 years of treatment with Angelique, the increase in femoral bone mineral density was 3.96 ± 3.15% (mean ± standard deviation) in patients with osteoporosis and 2.78 ± 1.89% (mean ± standard deviation) in individuals without osteoporosis. The proportion of women who maintained or increased their femoral bone mineral density during treatment was 94.4% among patients with osteoporosis and 96.4% among patients without osteoporosis.
The effect of the drug Angelique on bone mineral density in the lumbar spine was also established. The increase in density after 2 years of therapy was 5.61 ± 3.34% (mean ± standard deviation) in women with osteoporosis and 4.92 ± 3.02% (mean ± standard deviation) in women without osteoporosis. During treatment, preservation or improvement in bone mineral density in the lumbar spine was observed in 100% of women with osteoporosis and in 96.4% of women without osteoporosis.
- Antimineralocorticoid activity.
Drospirenone exerts a competitive antagonistic effect on aldosterone, which may result in a reduction in blood pressure in women with hypertension. In a double-blind, placebo-controlled study of postmenopausal women with hypertension who received Angelique (n = 123) for 8 weeks, a significant reduction in systolic and diastolic blood pressure was observed (office readings obtained using a cuff, compared with baseline values: -12/-9 mmHg, including the placebo effect: -3/-4 mmHg; 24-hour ambulatory blood pressure monitoring compared with baseline values: -5/-3 mmHg, including the placebo effect: -3/-2 mmHg).
Angelique is not indicated for the treatment of hypertension. Women with hypertension should receive treatment in accordance with hypertension treatment protocols.
Pharmacokinetics.
- Drospirenone.
Absorption. Following oral administration, drospirenone is rapidly and almost completely absorbed. The maximum serum concentration is reached approximately 1 hour after a single oral dose of Angelique and is 21.9 ng/mL. With repeated dosing, a maximum steady-state concentration of 35.9 ng/mL is observed approximately 10 days after the start of treatment. Bioavailability is 76–85% and is not affected by whether the drug is taken with food or on an empty stomach.
Distribution. Following oral administration, the serum concentration of drospirenone decreases in two phases, with a mean terminal half-life of approximately 35–39 hours. Drospirenone binds to serum albumin but does not bind to sex steroid-binding globulin (SSBG) or corticosteroid-binding globulin (CSBG). Only 3–5% of the total drospirenone concentration is present as free steroid in serum. The mean apparent volume of distribution of drospirenone is 3.7–4.2 L/kg.
Metabolism. After oral administration, drospirenone is extensively metabolized. The major metabolites in plasma are the acidic form of drospirenone, resulting from the opening of the lactone ring, and 4,5-dihydro-drospirenone-3-sulfate, which is formed by reduction followed by sulfation. These two major metabolites are pharmacologically inactive. Drospirenone also undergoes oxidative metabolism catalyzed by cytochrome P450 3A4.
Elimination. The plasma clearance of drospirenone is 1.2–1.5 mL/min/kg, with individual variations of approximately 25%. Only very small amounts of drospirenone are excreted unchanged. Drospirenone metabolites are excreted in feces and urine in a ratio of approximately 1.2 : 1.4. The half-life of metabolites in urine and feces is approximately 40 hours.
Steady-state concentration and linearity. Steady-state concentration is reached approximately 10 days after daily oral administration of Angelique. As a result of the ratio between the terminal half-life and the dosing interval, the serum concentration of drospirenone increased approximately 2–3-fold. At steady state, the mean serum concentration of drospirenone ranges from 14 to 36 ng/mL following administration of Angelique. The pharmacokinetic properties of drospirenone when the drug is administered in doses of 1–4 mg are dose-proportional.
- Estradiol.
Absorption. After oral administration, estradiol is rapidly and completely absorbed. During absorption and first-pass metabolism in the liver, estradiol is extensively metabolized, reducing the absolute bioavailability of estrogen after oral administration to approximately 5% of the administered dose. Peak concentrations, approximately 22 pg/mL, were reached approximately 6–8 hours after a single oral dose of Angelique. Food intake does not affect the bioavailability of estradiol compared to administration on an empty stomach.
Distribution. Following oral administration of Angelique, only gradual changes in serum estradiol concentrations are observed over the 24-hour interval between doses. Due to the large volume of circulating estrogen sulfates and glucuronides on the one hand, and enterohepatic recirculation on the other, the terminal half-life of estradiol is a composite parameter that depends on all of these processes and lasts approximately 13–20 hours after oral administration.
Estradiol binds nonspecifically to serum albumin and specifically to sex steroid-binding globulin (SSBG). Only 1–2% of estradiol circulates as a free steroid; 40–45% is bound to SSBG. The apparent volume of distribution of estradiol after a single intravenous administration is approximately 1 L/kg.
Metabolism. Estradiol is rapidly metabolized, resulting in the formation of a large number of other metabolites and conjugates in addition to estrone and estrone sulfate. Estrone and estriol are known to be pharmacologically active metabolites of estradiol. Only estrone has been detected in significant concentrations in plasma. The concentration of estrone in serum is approximately 6 times higher than that of estradiol. Serum concentrations of estrone conjugates are approximately 26 times higher than the corresponding concentrations of free estrone.
Elimination. Metabolic clearance is approximately 30 mL/min/kg. Estradiol metabolites are excreted in urine and bile with a half-life of approximately 1 day.
Steady-state concentration. After daily oral administration of the drug Angelique, steady-state estradiol concentrations are reached in approximately five days. Serum estradiol concentrations increase approximately twofold. When administered orally, estradiol induces the formation of SHBG, which affects its distribution among serum proteins, resulting in an increase in the SHBG-bound fraction and a decrease in the albumin-bound and unbound fractions, indicating the nonlinear nature of estradiol pharmacokinetics following administration of Angelique. With a 24-hour dosing interval, the mean steady-state concentration of estradiol in serum ranges from 20 to 43 pg/mL after administration of the drug Angelique. The pharmacokinetic properties of estradiol are directly proportional to the dose when the drug is administered at doses of 1 and 2 mg.
Special Patient Populations.
- Hepatic impairment.
An assessment of the pharmacokinetic properties of a single 3-mg oral dose of drospirenone in combination with 1 mg of estradiol was conducted in 10 female patients with moderate hepatic insufficiency (Class B according to the Child–Pugh classification) and 10 healthy women of matching age, weight, and smoking history. The mean serum concentration-time profiles for drospirenone were similar in both groups of women during the absorption and distribution phases, with identical Cmax and tmax values, suggesting that liver impairment does not affect the rate of absorption. In patients with moderate hepatic impairment, compared with healthy women without liver disease, the mean terminal half-life was nearly 1.8 times longer, and the apparent total clearance (CL/f) following oral administration was reduced by approximately 50%.
- Renal impairment.
The effect of renal impairment on the pharmacokinetic properties of drospirenone (3 mg daily for 14 days) was studied in patients with normal renal function and with mild to moderate renal impairment. Upon reaching steady state during drospirenone therapy, the group of women with mild renal insufficiency (creatinine clearance 50–80 mL/min) and in the group of women without impaired renal function (creatinine clearance > 80 mL/min), similar serum concentrations of drospirenone were observed. In the group of women with moderate renal impairment (creatinine clearance 30–50 mL/min), serum concentrations of drospirenone were on average 37% higher than in the group of women with normal renal function. Based on the results of a linear regression analysis of drospirenone AUC (0–24 hours) versus creatinine clearance, a 3.5% increase was observed with a 10 mL/min decrease in creatinine clearance. This slight increase is not clinically significant.
Preclinical safety data.
Animal studies with estradiol and drospirenone demonstrated the expected estrogenic and progestogenic effects. There are no preclinical study data that would supplement the information already provided in other sections of this Prescribing Information for the drug Angelique.
Indications
Hormone replacement therapy (HRT) for symptoms of estrogen deficiency in postmenopausal women more than 1 year after the onset of menopause.
Prevention of osteoporosis in postmenopausal women who are at increased risk of bone fractures and who are intolerant to other medications used for the prevention of osteoporosis, or for whom such medications are contraindicated (see the “Special Considerations for Use” section).
Experience with the use of this medication in women aged 65 years and older is limited.
Contraindications
- Genital bleeding of unknown cause.
- Breast cancer, suspected breast cancer, or a history of breast cancer.
- Estrogen-dependent malignant tumors or suspected estrogen-dependent malignant tumors (e.g., endometrial cancer).
- Untreated endometrial hyperplasia.
- Venous thromboembolism or a history of this condition (deep vein thrombosis, pulmonary embolism).
- Acute or recent arterial thromboembolism (e.g., angina, myocardial infarction, stroke).
- High risk of venous or arterial thrombosis.
- Acute liver disease or a history of liver disease—until liver function tests return to normal.
- Severe liver disease.
- Current or past history of liver tumors (benign or malignant).
- Predisposition to thrombosis (e.g., protein C deficiency, protein S deficiency, or antithrombin deficiency; see the “Special Considerations for Use” section).
- Impaired renal function or acute renal failure.
- Adrenal insufficiency.
- Known anaphylactic reactions, angioedema, or hypersensitivity to the active ingredients or to any of the drug’s excipients.
- Porphyria.
- Severe hypertriglyceridemia.
Drug Interactions and Other Interactions
Note: Review the information for any medication being taken concurrently to identify potential interactions.
Effects of other medications on Angelique.
Substances that increase the clearance of sex hormones (reduce efficacy by inducing enzymes)
The metabolism of estrogens and progestogens may be enhanced by concomitant use of substances that induce enzymes, particularly cytochrome P450 enzymes, such as anticonvulsants (e.g., phenobarbital, phenytoin, carbamazepine) and anti-infective agents (e.g., rifampicin, rifabutin, nevirapine, efavirenz); felbamate, griseofulvin, oxcarbazepine, topiramate, and medications containing St. John’s wort extract (Hypericum perforatum).
Clinically, increased metabolism of estrogens and progestogens may lead to reduced efficacy and changes in the pattern of uterine bleeding.
Enzyme induction may become apparent within a few days of treatment. Maximum enzyme induction is generally observed after several weeks. After discontinuation of treatment, enzyme induction may persist for approximately 4 weeks.
Substances with variable effects on the clearance of sex hormones
When used concomitantly with HRT, most HIV protease inhibitors and non-nucleoside reverse transcriptase inhibitors, including combinations with hepatitis C virus (HCV) inhibitors, may cause an increase or decrease in estrogen and progestin concentrations. These changes may be clinically significant in some cases.
Therefore, to identify potential interactions, consult the prescribing information for the HIV/HCV medication being taken concurrently.
Substances that reduce the clearance of sex hormones (enzyme inhibitors)
Potent or moderate CYP3A4 inhibitors, such as azole antifungals (e.g., fluconazole, itraconazole, ketoconazole, voriconazole), verapamil, macrolides (e.g., clarithromycin, erythromycin), diltiazem, and grapefruit juice, may lead to increased plasma concentrations of estrogens and progestins. In a multiple-dose study of the combination of drospirenone (3 mg/day) and estradiol (1.5 g/day), the concomitant use of the potent CYP3A4 inhibitor ketoconazole for 10 days resulted in a 2.30-fold increase in the AUC (0–24 h) of drospirenone (90% confidence interval (CI): 2.08; 2.54). No changes were observed in estradiol parameters; however, the AUC (0–24 h) of its less potent metabolite, estrone, increased by a factor of 1.39 (90% CI: 1.27; 1.52).
Effect of the drug Angelique on other drugs
In vitro, drospirenone is capable of weakly or moderately inhibiting the cytochrome P450 enzymes CYP1A1, CYP2C9, CYP2C19, and CYPZA4.
Based on the results of an in vivo interaction study conducted in healthy female volunteers who received drospirenone at a fixed dose of 3 mg per day in combination with omeprazole, simvastatin, or midazolam as marker substrates, a clinically significant interaction between drospirenone and other drugs whose metabolism depends on cytochrome P450 is considered unlikely.
It is unlikely that the combined use of the drug Angelique with NSAIDs (nonsteroidal anti-inflammatory drugs) or angiotensin-converting enzyme inhibitors/angiotensin II receptor antagonists will increase serum potassium levels. However, the concomitant use of these three types of medications may cause a slight increase in serum potassium levels, which is more pronounced in women with diabetes. In women with hypertension, an additional decrease in blood pressure may occur during treatment with Angelique (see the “Special Considerations” section).
Alcohol abuse during HRT may lead to an increase in circulating estrogen levels in the blood.
Other Interactions
In clinical trials involving patients receiving treatment for viral hepatitis C with medications containing ombitasvir/paritaprevir/ritonavir, with or without dasabuvir, elevations in transaminase (ALT) levels more than 5 times the upper limit of normal (ULN) were observed significantly more frequently in women taking medications containing ethinyl estradiol, such as combined hormonal contraceptives (CHCs).
The rate of ALT elevation in women taking medications containing estrogens other than ethinyl estradiol, such as estradiol, was similar to that in women who did not receive any estrogens. However, due to the limited number of women taking estrogens other than ethinyl estradiol, caution should be exercised when co-administering with medications containing ombitasvir/paritaprevir/ ritonavir with or without dasabuvir, as well as with the combination of glecaprevir/pibrentasvir (see the “Special Considerations for Use” section).
Laboratory Tests.
The use of sex hormones may affect the results of certain laboratory tests, including biochemical markers of liver, thyroid, adrenal, and kidney function, protein (carrier) levels, such as sex hormone-binding globulins, lipids/lipoprotein fractions, and coagulation and fibrinolysis parameters. As a rule, these changes remain within normal limits. Drospirenone causes an increase in plasma renin and plasma aldosterone levels, which is due to its moderate antimineralocorticoid activity.
Special Considerations for Use
When treating disorders associated with the postmenopausal period, HRT should be initiated only in the presence of symptoms that impair quality of life. In all cases, a thorough benefit-risk assessment must be conducted at least once a year, and HRT should be continued only if the benefits outweigh the risks.
Data on the risks associated with HRT in the treatment of premature menopause are limited. However, due to the low absolute risk in younger women, the benefit-risk ratio in these women may be more favorable than in older women.
Medical evaluation/follow-up.
Before starting or resuming HRT, the patient’s personal and family medical history should be thoroughly reviewed, and a physical examination (including examination of the pelvic organs and breasts) should be performed, taking into account contraindications (see “Contraindications”) and precautions (see “Adverse Reactions”), and repeat such examinations periodically. The frequency and nature of these examinations should be based on current standards of medical practice, taking into account the individual characteristics of each patient. Women should be advised regarding which changes in their breasts they should report to their doctor or nurse. Examinations, including appropriate imaging methods such as mammography, should be performed in accordance with current screening practices, adapted to individual clinical needs.
Conditions Requiring Monitoring.
If any of the conditions listed below are currently present, have a history of occurrence, and/or have worsened during pregnancy or previous hormone therapy, the patient should be under close medical supervision. It is important to note that these conditions may recur or worsen during treatment with Angelique. Specifically, these include:
- leiomyoma (uterine fibroid) or endometriosis;
- the presence of risk factors for thromboembolic complications (see below);
- the presence of risk factors for estrogen-dependent tumors, such as a first-degree family history of breast cancer;
- hypertension;
- liver disease (e.g., hepatadenoma);
- diabetes mellitus with or without vascular complications;
- gallstone disease;
- migraine or (severe) headache;
- systemic lupus erythematosus (SLE);
- history of endometrial hyperplasia (see below);
- epilepsy;
- asthma;
- otosclerosis.
Reasons for Immediate Discontinuation of Therapy
HRT should be discontinued immediately if any of the contraindications are identified, as well as in the presence of the following conditions and diseases:
- jaundice or impaired liver function;
- a significant increase in blood pressure;
- first occurrence of a migraine-like headache;
- pregnancy;
- cholestatic pruritus occurring for the first time, during pregnancy, or following the use of sex steroids;
- symptoms of thrombosis or suspected thrombosis.
Gallbladder disease.
Estrogens increase the lithogenicity of bile. Some women are prone to developing gallbladder disease during estrogen therapy.
Endometrial hyperplasia and carcinoma.
In women with an intact uterus, long-term estrogen monotherapy increases the risk of developing endometrial hyperplasia or carcinoma. The observed increased risk of endometrial cancer among patients who received estrogen monotherapy—depending on the duration of treatment and the estrogen dose—is 2 to 12 times higher than the risk in women who did not receive estrogen (see the “Adverse Reactions” section). After discontinuation of treatment, the increased risk may persist for at least 10 years.
Including progestins in the treatment regimen on a cyclic basis for at least 12 days per month (28-day cycle) or continuous combined estrogen-progestin therapy helps prevent the increased risks associated with estrogen-only hormone replacement therapy in women with an intact uterus.
Menstrual-like bleeding and spotting may occur during the first few months of treatment. If such symptoms occur some time after the start of treatment or persist after discontinuation of therapy, their causes must be identified; for this purpose, an endometrial biopsy may be performed to rule out malignant endometrial tumors.
Breast cancer.
There is evidence of an increased risk of breast cancer in women receiving combined estrogen-progestin therapy or, possibly, estrogen-only HRT; this risk depends on the duration of HRT.
Combined estrogen-progestin therapy
Results from the randomized, placebo-controlled Women’s Health Initiative (WHI) study — WHI) and a meta-analysis of prospective epidemiological studies revealed an increased risk of breast cancer in women receiving combined estrogen-progestin HRT. This risk emerged approximately 3 (1–4) years after starting therapy (see the “Adverse Reactions” section).
Estrogen-only HRT
The WHI study did not find an increased risk of breast cancer with estrogen-only HRT in women who had undergone hysterectomy. Observational studies have, in most cases, shown a slightly increased risk of a breast cancer diagnosis with estrogen-only HRT, but the risk was lower than that in women using combined estrogen-progestin therapy (see the “Adverse Reactions” section).
The results of a large meta-analysis showed that the increased risk decreases over time after discontinuation of therapy and that the time it takes to return to the age-related baseline risk depends on the duration of HRT use. If HRT was used for more than 5 years, the risk may persist for 10 years or longer.
HRT, particularly combined estrogen-progestin therapy, increases mammographic density, which may adversely affect the radiological diagnosis of breast cancer.
Venous Thromboembolism
HRT is associated with a 1.3- to 3-fold increased risk of venous thromboembolism (VTE), i.e., deep vein thrombosis or pulmonary embolism. The likelihood of these events occurring is higher during the first year of HRT than in subsequent years (see the “Adverse Reactions” section).
Generally recognized risk factors for VTE include estrogen use, advanced age, major surgery, patient obesity, or a family history of this condition (BMI > 30 kg/m²), pregnancy/postpartum period, SLE, and cancer. There is currently no consensus on the role of varicose veins in the development of VTE.
Patients with a known predisposition to thrombosis are at increased risk for VTE, and HRT may further increase this risk. Therefore, HRT is contraindicated in this group of patients (see the “Contraindications” section).
As with all postoperative patients, preventive measures should be taken to prevent VTE following surgery. If prolonged immobilization is required after elective surgery, it is recommended to temporarily discontinue HRT 4–6 weeks prior to the procedure. Treatment may be resumed only after the woman has fully regained her mobility.
Women with no personal history of VTE but with a family history of thrombosis in first-degree relatives at a young age may be offered screening, however, after thoroughly discussing the limitations of the data that will be obtained (screening may detect only some thrombophilic disorders). If a specific predisposition to thrombosis is identified—one that is also observed in other family members—or if the disorder is severe (e.g., antithrombin, protein S, protein C, or multiple disorders), OAT is contraindicated.
In women already receiving long-term anticoagulant therapy, the benefit-risk ratio of using ZGT should be carefully weighed.
If venous thromboembolism develops after the start of therapy, the drug should be discontinued. Patients should be advised to seek immediate medical attention if they experience potential symptoms of thromboembolism (e.g., painful leg swelling, sudden chest pain, shortness of breath).
Ischemic heart disease (IHD).
Data from randomized controlled trials indicate no protective effect against the development of myocardial infarction in women with or without CHD who received combined estrogen-progestin HRT or estrogen monotherapy. The relative risk of developing CHD with combined estrogen-progestin HRT is slightly elevated. Since the baseline absolute risk of CHD depends largely on age, the number of additional cases of CHD attributable to the use of estrogens and progestins is very small in healthy women approaching menopause, but will increase with advancing age.
Ischemic stroke.
Combined estrogen-progestin therapy and estrogen monotherapy are associated with a 1.5-fold increase in the risk of ischemic stroke. The relative risk does not change with age or with the time elapsed since the onset of menopause. However, since the baseline risk of stroke depends significantly on age, the overall risk of stroke in women using HRT will increase with age (see the “Adverse Reactions” section).
Ovarian cancer.
Ovarian cancer is much less common than breast cancer.
Epidemiological data from a large-scale meta-analysis suggest a slightly increased risk of ovarian cancer in women using estrogen-only or combined estrogen-and-progestin HRT, which becomes more pronounced within 5 years of use and decreases for some time after discontinuation.
Results from some studies, including the WHI study, indicate that the use of combined HRT may be associated with a similar or slightly lower risk (see the “Adverse Reactions” section).
Liver tumors.
In rare cases, benign (less commonly malignant) liver tumors have been observed following the use of hormonal medications (e.g., for HRT). Occasionally, these tumors have led to life-threatening intra-abdominal bleeding.
Hepatitis C.
In clinical trials involving patients receiving treatment for viral hepatitis C with medications containing ombitasvir/paritaprevir/ritonavir, with or without dasabuvir, elevations in ALT levels more than 5 times the upper limit of normal (ULN) were observed significantly more frequently in women taking medications containing ethinyl estradiol, such as combined oral contraceptives (COCs). In addition, elevated ALT levels were observed in women taking medications containing ethinyl estradiol during treatment with glecaprevir/pibrentasvir.
The incidence of elevated ALT levels in women taking medications containing estrogens other than ethinyl estradiol, such as estradiol, was similar to that in women who did not receive any estrogens. However, due to the limited number of women taking estrogens other than ethinyl estradiol, caution is advised when co-administering with medications containing ombitasvir/paritaprevir/ ritonavir with or without dasabuvir, as well as with the combination of glecaprevir/pibrentasvir (see the “Drug Interactions and Other Interactions” section).
Other Conditions.
Estrogens may cause fluid retention; therefore, patients with impaired cardiac or renal function require close monitoring.
Women with moderately elevated triglyceride levels require special monitoring. In such cases, HRT may cause a further increase in triglyceride levels, posing a risk of pancreatitis.
Exogenous estrogens may induce or exacerbate symptoms of hereditary or acquired angioedema.
Estrogens increase thyroxine-binding globulin (TBG) levels, leading to an increase in total circulating thyroid hormone levels. This parameter is determined by the level of protein-bound iodine, the level of T4 (measured by column chromatography or radioimmunoassay), or T3 (measured by radioimmunoassay). T3 uptake decreases, indicating elevated TSH levels. Concentrations of free T3 and T4 remain unchanged. Levels of other serum binding proteins — corticosteroid-binding globulin and sex hormone-binding globulin — may increase, leading to elevated concentrations of circulating corticosteroids and sex hormones, respectively. Concentrations of free or biologically active hormones remain unchanged. Concentrations of other plasma proteins (angiotensinogen/renin substrate, alpha-1-antitrypsin, ceruloplasmin) may increase.
HRT does not improve cognitive function. There is limited evidence that long-term combined HRT or estrogen monotherapy increases the risk of dementia if treatment is initiated in women aged 65 years or older.
The progesterone component of the drug Angelique is an aldosterone antagonist that exhibits a slight potassium-sparing effect. In most cases, an increase in serum potassium levels is unlikely. However, in a clinical study, some patients with mild to moderate renal insufficiency who were concurrently taking potassium-sparing medications (e.g., ACE inhibitors, angiotensin II receptor antagonists, or NSAIDs), a slight increase in serum potassium levels was observed during treatment with drospirenone. Therefore, during the first month of treatment, and especially during concomitant therapy with potassium-sparing medications, it is recommended to monitor serum potassium levels in patients with renal insufficiency whose serum potassium levels were at the upper limit of normal prior to treatment (see the section “Interactions with Other Medications and Other Interactions”).
In women with high blood pressure, a decrease in blood pressure may occur during treatment with Angelique, due to the antagonistic activity of drospirenone against aldosterone (see the “Pharmacodynamics” section). Angelique is not indicated for the treatment of hypertension. Women with hypertension should be treated according to the appropriate treatment protocol.
In some cases, chloasma may occur, particularly in women with a history of chloasma of pregnancy. While undergoing HRT, women prone to chloasma should avoid exposure to sunlight or ultraviolet radiation.
Each Angelique tablet contains 46 mg of lactose. Patients with rare hereditary disorders such as galactose intolerance, lactase deficiency, or glucose-galactose malabsorption should not use this medication.
Mild liver dysfunction, including hyperbilirubinemia (e.g., Dubin–Johnson syndrome, Rotor syndrome), requires careful monitoring; periodic monitoring of liver function tests is also necessary. If abnormal changes in liver function tests occur, treatment with ZGT must be discontinued.
Patients with prolactinoma require close medical supervision (including periodic measurement of prolactin levels).
The administration of estrogens may lead to severe hypercalcemia in women with breast cancer and bone metastases. If hypercalcemia develops, treatment with the drug must be discontinued, and appropriate measures taken to lower blood calcium levels.
Estrogen therapy should be used with caution in women with hypoparathyroidism, as they may develop estrogen-induced hypocalcemia.
Cases of retinal vascular thrombosis have been reported in women receiving estrogens. In the event of sudden partial or complete loss of vision, sudden onset of proptosis, diplopia, or migraine, the drug must be discontinued. If optic disc edema or retinal vascular damage occurs, estrogen therapy must be discontinued.
As an aldosterone antagonist, drospirenone may increase the risk of hyponatremia in high-risk patients.
Serum concentrations of follicle-stimulating hormone and estradiol were not indicative in the management of patients with moderate to severe vasomotor symptoms.
Use during pregnancy or breastfeeding.
Pregnancy
Angelique is contraindicated in pregnant women. If pregnancy occurs while taking Angelique, the medication should be discontinued immediately. There are no clinical data on the effects of drospirenone on pregnancy. Results of animal studies indicate adverse effects of the drug during pregnancy and lactation (reproductive toxicity; see the “Pharmacological Properties” section). The potential risk to humans is unknown. Currently available epidemiological data do not indicate any teratogenic or embryotoxic effects of estrogen/progestin combinations when used accidentally during pregnancy.
Breastfeeding
Angelique is contraindicated in women who are breastfeeding.
Effect on reaction time when driving or operating machinery.
The drug Angelique does not affect reaction time when driving or operating machinery.
Dosage and Administration
If HRT is being prescribed for the first time or if a switch to Angelique is being made from a combined continuous HRT preparation, Angelique tablets may be started at any time. If switching to Angelique from a cyclic combined HRT preparation, the current treatment cycle should be completed before starting Angelique.
Dosage.
One tablet per day. Each package is designed for a 28-day course of treatment.
Directions for Use.
Swallow the tablet whole with a small amount of liquid. Treatment is continuous; that is, start taking tablets from the next pack immediately after finishing the previous one, without any breaks. It is recommended to take the tablets at the same time each day. If you miss a scheduled dose, take it as soon as possible. If more than 24 hours have passed since the scheduled dose, do not take an extra tablet. If several tablets are missed in a row, bleeding may occur.
The lowest effective dose is used to treat postmenopausal symptoms.
To initiate and continue therapy for postmenopausal symptoms, the lowest effective dose is used for the shortest possible duration (see also the “Special Considerations” section).
Additional Information for Specific Patient Populations
Elderly patients.
There are no data indicating a need for dose adjustment in elderly patients.
Patients with hepatic impairment.
In women with mild to moderate hepatic impairment, drospirenone is well tolerated (see the “Pharmacokinetics” section). The use of the drug Angelique is contraindicated in women with severe hepatic impairment (see the “Contraindications” section). Patients with impaired liver function require close monitoring; if liver function parameters deteriorate, HRT should be discontinued (see the “Special Considerations” section).
Patients with renal insufficiency.
In women with mild or moderate renal insufficiency, a slightly increased exposure to drospirenone is observed; however, this effect is not considered clinically significant (see the “Pharmacokinetics” section). The use of Angelique is contraindicated in women with severe renal impairment (see the “Contraindications” section).
Children.
Angélique is not indicated for use in children and adolescents.
Overdose
In clinical studies conducted with male volunteers, doses of up to 100 mg of drospirenone were well tolerated. Overdose may cause nausea and vomiting; some women may experience vaginal bleeding. There is no specific antidote; treatment should be symptomatic.
Side Effects
The frequency of adverse reactions reported during clinical trials with the drug Angelique is summarized in the table below by organ system (Medical Dictionary for Regulatory Activities (MedDRA) System Organ Class (SOC)). Adverse reactions were observed during 7 Phase III clinical trials (N = 2,424 women) and are considered to have at least a potential causal relationship with the use of Angelique (estradiol 1 mg/drospirenone 0.5, 1, 2, or 3 mg).
The most commonly reported adverse reactions with Angélique were breast pain (>10%) and, during the first months of therapy, bleeding and spotting (>10%), which usually resolved as treatment continued (see the “Pharmacological Properties” section). The frequency of bleeding decreased as the duration of therapy increased.
| Organ Systems | Common
(≥ 1/100 to < 1/10) |
Uncommon
(≥ 1/1,000 to < 1/100) |
Rare
(< 1/1,000) |
| Hematologic and lymphatic system | anemia | ||
| Nutrition and Metabolic Disorders | weight gain or weight loss, anorexia, increased appetite, hyperlipidemia | ||
| Psychiatric | depression, emotional instability, nervousness | Sleep disturbances, anxiety, decreased libido | |
| Nervous system | headache | paresthesia, impaired concentration, dizziness | vertigo |
| Eye-related | Eye diseases, visual disturbances | ||
| Ear and balance disorders | ringing in the ears | ||
| Cardiac | rapid heartbeat | ||
| Vascular system | embolism, venous thrombosis, hypertension, migraine, thrombophlebitis, varicose veins | ||
| Respiratory, thoracic, and mediastinal symptoms | shortness of breath | ||
| Gastrointestinal system | abdominal pain, nausea, bloating | gastrointestinal disorders, diarrhea, constipation, vomiting, dry mouth, flatulence, taste disturbances | |
| Liver and biliary tract | changes in liver function tests | gallstone disease | |
| Skin and subcutaneous tissue disorders | skin inflammation, acne, alopecia, itching, rash, hirsutism, abnormal hair changes | ||
| Musculoskeletal and connective tissue disorders | pain in the extremities, back pain, arthralgia, muscle cramps | myalgia | |
| Renal and urinary system | urinary tract disorders, urinary tract infections | ||
| Reproductive system and breast disorders | benign breast lesions, breast enlargement, enlargement of uterine fibroids, benign cervical lesions, menstrual disorders, vaginal discharge | breast carcinoma, endometrial hyperplasia, benign uterine tumors, fibrocystic mastopathy, uterine disorders, ovarian disorders, cervical disorders, pelvic pain, vulvovaginal disorders, vaginal candidiasis, vaginitis, vaginal dryness | salpingitis, galactorrhea |
| General disorders | asthenia, localized edema | generalized edema, chest pain, discomfort, excessive sweating | chills |
To describe an individual adverse reaction or concomitant condition, use the most appropriate MedDRA term.
Specific patient groups.
The adverse reactions listed below are considered to be the least likely to be associated with the use of the drug Angelique; they were observed during two clinical trials in women with hypertension.
Nutritional and Metabolic Disorders.
Hyperkalemia.
Cardiac disorders.
Heart failure, atrial flutter, QT interval prolongation, cardiomegaly.
Laboratory tests.
Elevated blood aldosterone levels.
The following adverse reactions have also been reported during HRT: erythema nodosum; erythema multiforme; chloasma; hemorrhagic dermatitis.
Risk of breast cancer.
In women receiving combined estrogen-progestin therapy for more than 5 years, an up to twofold increase in the risk of breast cancer has been reported.
The increased risk among patients receiving estrogen monotherapy is significantly lower than in those receiving estrogen-progestin combinations. The degree of risk depends on the duration of use (see the “Special Considerations for Use” section). Estimates of absolute risk are based on the results of the largest randomized, placebo-controlled trial (the WHI study) and the largest meta-analysis of prospective epidemiological studies to date.
The largest meta-analysis to date of prospective epidemiological studies
Estimated additional risk of developing breast cancer after 5 years of HRT use in women with a BMI of 27 (kg/m²).
| Age at the start of HRT (years) | Incidence per 1,000 women who have never used HRT over a 5-year period (ages 50–54)* | Risk ratio | Number of additional cases per 1,000 women who used HRT after a 5-year period |
| Estrogen-only HRT | |||
| 50 | 13.3 | 1.2 | 2.7 |
| Combined estrogen-progestin therapy | |||
| 50 | 13.3 | 1.6 | 8.0 |
* Relative to baseline breast cancer incidence rates in England for women with a BMI of 27 (kg/m²) in 2015. Note: Since baseline breast cancer incidence rates vary across EU countries, the number of additional breast cancer cases will vary proportionally in each EU country.
Estimated additional risk of breast cancer after 10 years of HRT use in women with a BMI of 27 (kg/m²)
| Age at the start of HRT (years) | Incidence per 1,000 women who have never used HRT over a 10-year period (ages 50–59)* | Risk ratio | Number of additional cases per 1,000 women who used HRT after a 10-year period |
| Estrogen-only HRT | |||
| 50 | 26.6 | 1.3 | 7.1 |
| Combined estrogen-progestin therapy | |||
| 50 | 26.6 | 1.8 | 20.8 |
* Relative to baseline breast cancer incidence rates in England for women with a BMI of 27 (kg/m²) in 2015.
Note: Since baseline breast cancer incidence rates vary across EU countries, the number of additional breast cancer cases will vary proportionally in each EU country.
WHI Study (U.S.) – Additional Risk of Breast Cancer After 5 Years of Use
| Age range (years) | Number of cases per 1,000 women in the placebo group after 5 years | Risk ratio and
95% CI |
Number of additional cases per 1,000 women who used HRT for 5 years (95% CI) |
| Estrogen-only HRT | |||
| 50–79 | 21 | 0.8 (0.7–1.0) |
|
| Combined estrogen-progestin therapyb | |||
| 50–79 | 17 | 1.2 (1.0–1.5) | +4 (0–9) |
a The WHI study involving women with a history of hysterectomy, in which no increased risk of breast cancer was observed.
b When the analysis was restricted to women who had not received HRT prior to study enrollment, no clear increase in risk was observed during the first 5 years of treatment; after 5 years, the risk was slightly higher than in women who did not receive this therapy.
Risk of endometrial cancer.
Postmenopausal women with an intact uterus.
The risk of endometrial cancer is approximately 5 cases per 1,000 women with an intact uterus who are not taking HRT. Estrogen-only HRT is not recommended for women with an intact uterus due to an increased risk of endometrial cancer (see the “Special Considerations” section). Epidemiological studies have shown that, depending on the duration of monotherapy and estrogen doses, the risk of endometrial cancer ranged from 5 to 55 additional cases per 1,000 women aged 50 to 65.
The use of progestins for at least 12 days per cycle in addition to estrogens may prevent this increased risk. In the “Million Women” study, 5 years of combined (sequential or continuous) HRT did not result in an increased risk of endometrial cancer [relative risk (RR) 1.0 (0.8–1.2)].
Ovarian cancer.
Long-term use of estrogen monotherapy and combined HRT with estrogen and progestin is associated with a slight increase in the risk of ovarian cancer (see the “Special Considerations for Use” section).
A meta-analysis of 52 epidemiological studies indicates an increased risk of ovarian cancer in women using HRT compared with women who have never used HRT (RR 1.43; 95% CI 1.31–1.56). In women aged 50 to 54 who use HRT for 5 years, these results correspond to one additional case per 2,000. Among women aged 50 to 54 who do not use HRT, approximately 2 out of every 2,000 will be diagnosed with ovarian cancer over a 5-year period.
Risk of venous thromboembolism.
HRT is associated with a 1.3–3-fold increase in the relative risk of venous thromboembolism (VTE), i.e., deep vein thrombosis or pulmonary thromboembolism. The likelihood of such events is higher during the first year of HRT use (see the “Special Considerations for Use” section). The results of the WHI studies are presented below.
WHI Studies—Additional Risk of VTE Over 5 Years of HRT Use
| Age range (years) | Incidence per 1,000 women in the placebo group over 5 years | Risk ratio and 95% CI | Number of additional cases per 1,000 women using HRT |
| Oral estrogen-only therapya | |||
| 50–59 | 7 | 1.2 (0.6–2.4) | 1 (–3–10) |
| Oral use of a combination of estrogen and progestin | |||
| 50–59 | 4 | 2.3 (1.2–4.3) | 5 (1–13) |
a Studies involving women with a history of hysterectomy.
Risk of ischemic heart disease.
In women aged 60 years and older who use combined estrogen-progestin HRT, there is a slight increase in the risk of developing coronary heart disease (see the “Special Considerations for Use” section).
Risk of ischemic stroke.
The use of estrogen-only therapy and estrogen-progestin therapy is associated with an increase in the relative risk of ischemic stroke by up to 1.5 times. The risk of hemorrhagic stroke does not increase with HRT use.
The relative risk does not depend on age or duration of use; however, since the baseline risk is significantly age-dependent, the overall risk of stroke in women taking HRT will increase with age (see the “Special Considerations” section).
Pooled data from the WHI studies—additional risk of ischemic stroke over 5 years of HRT use.
| Age range (years) | Incidence per 1,000 women in the placebo group over 5 years | Risk ratio and
95% CI |
Additional number of cases per 1,000 women taking HRT over 5 years |
| 50–59 | 8 | 1.3 (1.1–1.6) | 3 (1–5) |
| a Without distinguishing between ischemic and hemorrhagic stroke. | |||
Other adverse reactions reported in association with estrogen/progestin therapy:
- gallbladder disorders;
- skin and subcutaneous tissue disorders (chloasma, erythema multiforme, erythema nodosum, vascular purpura);
- possibly dementia in patients over 65 years of age (see the “Special Considerations” section).
The following adverse reactions may also occur: breast discomfort, liver tumors; liver dysfunction; hypertriglyceridemia; changes in glucose tolerance; recurrence of endometriosis; prolactinoma; jaundice and/or pruritus associated with cholestasis; epilepsy, asthma, porphyria, systemic lupus erythematosus; otosclerosis; chorea; angioedema, peripheral edema, hypersensitivity reactions, including rash and hives.
Reporting of Suspected Adverse Reactions
Reporting suspected adverse reactions during postmarketing surveillance is very important. This allows for the monitoring of the benefit-risk profile of medicinal products. Healthcare professionals should report suspected adverse reactions.
Shelf life
5 years.
Do not use this medication after the expiration date printed on the package.
Storage Conditions
Store at a temperature not exceeding 25 °C, out of the reach of children.
Packaging
28 film-coated tablets in a blister pack with a calendar scale, in a paper pouch, inside a cardboard box.
.
Manufacturer
Bayer AG.
Manufacturer’s location and business address.
Müllerstraße 178, 13353, Berlin, Germany.