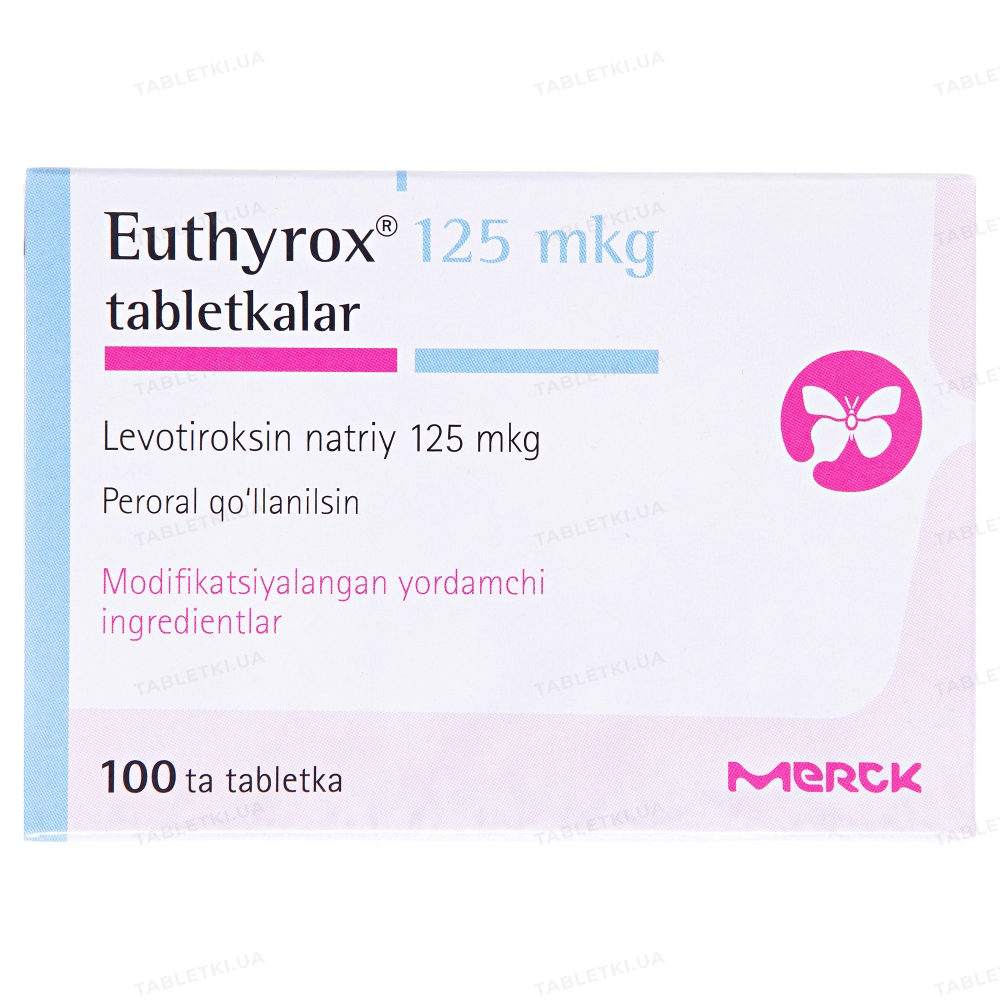

Eutirox 125 mcg tablets, No. 100 (25 x 4)
Composition
Active ingredient: levothyroxine sodium;
1 tablet contains 25 mcg, 50 mcg, 75 mcg, 100 mcg, 125 mcg, or 150 mcg of levothyroxine sodium;
Excipients: mannitol (E 421); corn starch; gelatin; croscarmellose sodium; anhydrous citric acid; magnesium stearate.
Dosage Form
Tablets.
Main physical and chemical properties: nearly white, round, flat on both sides, with beveled edges, a score line on both sides, and engraved on one side with “EM + dosage.”
Pharmacotherapeutic group
Hormonal preparations for systemic use (excluding sex hormones and insulin). Preparations for the treatment of thyroid disorders. Thyroid preparations. Levothyroxine sodium. ATC code H0ZA A01.
Pharmacological Properties
Pharmacodynamics. The synthetic levothyroxine contained in Eutirox exhibits effects identical to those of the hormone secreted by the thyroid gland. It is converted to T3 (triiodothyronine) in peripheral organs and, like the endogenous hormone, acts on T3 receptors. There is no difference between the functions of the endogenous hormone and those of exogenous levothyroxine.
Pharmacokinetics. After oral administration, levothyroxine is almost completely absorbed in the upper small intestine. Depending on the dosage form, up to 80% of the administered dose is absorbed. Maximum concentration (Tmax) is reached in approximately 5–6 hours.
The clinical effect of the drug becomes apparent 3–5 days after oral administration. Levothyroxine rapidly binds to specific transport proteins in the blood (up to 99.97%). The binding to proteins is not covalent; thus, the bound hormone present in plasma is capable of constantly and rapidly exchanging with the free hormone fractions.
Due to its high protein-binding capacity, levothyroxine is not removed by hemodialysis or hemoperfusion.
The drug’s half-life is 7 days. In hyperthyroidism, this period is reduced to 3–4 days, and in hypothyroidism, it is prolonged to 9–10 days. The volume of distribution is 10–12 L. Approximately one-third of the total administered levothyroxine accumulates in the liver, where it rapidly interacts with levothyroxine present in serum. Thyroid hormones are metabolized primarily in the liver, kidneys, brain, and muscles. Metabolites are excreted in the urine and feces. The total metabolic clearance of levothyroxine is approximately 1.2 L of plasma per day.
Indications
Eutirox 25–200 mcg
- Treatment of benign euthyroid goiter.
- Prevention of recurrence following surgical treatment of euthyroid goiter, depending on hormone levels during the postoperative period.
- As replacement therapy for hypothyroidism.
- Suppressive therapy for thyroid cancer.
Eutirox 25–100 mcg
- As an adjunctive medication during antithyroid therapy for hyperthyroidism.
Eutirox 100/150/200 mcg
- As a diagnostic tool during thyroid suppression testing.
Contraindications
- Hypersensitivity to any component of the drug.
- Untreated adrenal insufficiency, pituitary insufficiency, or thyrotoxicosis.
- Acute myocardial infarction, acute myocarditis, acute pancarditis.
- Combination therapy with levothyroxine and antithyroid agents is not indicated during pregnancy (see the section “Use During Pregnancy or Breastfeeding”).
Interactions with Other Medications and Other Types of Interactions
Antidiabetic agents. Levothyroxine may reduce the effect of antidiabetic drugs. It is recommended to monitor blood glucose levels frequently at the start of thyroid hormone therapy and, if necessary, adjust the dose of antidiabetic medications.
Coumarin derivatives. Levothyroxine potentiates the effects of anticoagulants by displacing them from their binding sites on plasma proteins, which increases the risk of hemorrhage, such as hemorrhage in the spinal cord or brain, or gastrointestinal bleeding, especially in the elderly. Therefore, coagulation parameters should be monitored regularly at the start of and during combination therapy, and the daily dose of anticoagulants should be adjusted as necessary.
Protease inhibitors (e.g., ritonavir, indinavir, lopinavir) may affect the action of levothyroxine. Careful monitoring of thyroid hormone levels is required. If necessary, the levothyroxine dose should be adjusted.
Phenytoin may affect the action of levothyroxine by displacing it from its binding sites on plasma proteins, resulting in increased levels of free thyroxine (fT4) and free triiodothyronine (fT3). On the other hand, phenytoin increases the hepatic metabolism of levothyroxine. Careful monitoring of thyroid hormone levels is recommended.
Cholestyramine, colestipol. The use of ion-exchange resins such as cholestyramine and colestipol inhibits the absorption of levothyroxine sodium. Therefore, levothyroxine sodium should be taken 4–5 hours before taking these medications.
Medications containing aluminum, iron, and calcium salts. According to data cited in relevant literature, medications containing aluminum (antacids, sucralfate) may potentially reduce the effect of levothyroxine. Therefore, levothyroxine should be taken at least 2 hours before taking medications containing aluminum. This also applies to medications containing iron and calcium salts.
Salicylates, dicumarol, furosemide in high doses (250 mg), clofibrate, and other substances may displace levothyroxine sodium from its binding to plasma proteins, leading to an increase in the fT4 fraction.
Proton pump inhibitors (PPIs). Concomitant use with PPIs may reduce the absorption of thyroid hormones due to an increase in intragastric pH caused by PPIs. During concomitant treatment, regular monitoring of thyroid function and clinical monitoring are recommended, with a possible increase in the dose of thyroid hormones.
Caution should also be exercised when PPI treatment is discontinued.
Orlistat. Concomitant use of orlistat and levothyroxine may lead to the development of hypothyroidism and/or worsening of hypothyroidism control. This may be due to reduced absorption of iodine salts and/or levothyroxine.
Sevelamer may reduce the absorption of levothyroxine. Therefore, it is recommended to monitor changes in thyroid function tests at the beginning and end of concomitant treatment. If necessary, the levothyroxine dose should be adjusted.
Tyrosine kinase inhibitors (e.g., imatinib, sunitinib) may reduce the effectiveness of levothyroxine. Therefore, it is recommended to monitor changes in thyroid function at the start and end of concomitant treatment. If necessary, the levothyroxine dose should be adjusted.
Propylthiouracil, glucocorticoids, beta-blockers, amiodarone, and iodine-containing contrast agents inhibit the peripheral conversion of T4 to T3. Due to its high iodine content, amiodarone may contribute to the development of both hyperthyroidism and hypothyroidism. The drug should be prescribed with particular caution to patients with nodular goiter of unknown etiology.
Sertraline, chloroquine/proguanil reduce the effectiveness of levothyroxine and increase serum TSH levels.
Enzymes induced by medications such as barbiturates, carbamazepine, or products containing St. John’s wort (Hypericum perforatum L.) may increase the hepatic clearance of levothyroxine, leading to a decrease in serum thyroid hormone concentrations.
Therefore, patients receiving thyroid replacement therapy may require an increase in their thyroid hormone dose if these medications are taken concurrently.
Estrogens. Women taking estrogen-containing contraceptives, as well as postmenopausal women taking hormone replacement therapy, may require higher doses of levothyroxine.
Products containing soy may inhibit the intestinal absorption of levothyroxine. Therefore, the dose of Eutirox should be adjusted, especially at the start of and after discontinuing the use of soy-containing supplements.
Effect on Laboratory Tests. Biotin may interfere with immunological thyroid tests based on the biotin/streptavidin interaction, leading to falsely low or falsely high test results (see the “Special Considerations for Use” section).
Special Considerations for Use
Before starting treatment with thyroid hormones or performing thyroid suppression tests, the presence of conditions such as coronary insufficiency, angina, atherosclerosis, hypertension, pituitary insufficiency. Functional autonomy of the thyroid gland should also be ruled out or treated prior to initiating thyroid hormone therapy.
In cases of adrenocortical dysfunction, appropriate replacement therapy should be administered before starting levothyroxine therapy to prevent acute adrenal insufficiency (see the “Contraindications” section).
Levothyroxine therapy in patients at risk of developing psychotic disorders should be initiated at low doses, with the dosage gradually increased at the start of therapy. It is recommended to monitor the patient’s condition. If psychotic disorders develop, consider adjusting the levothyroxine dose.
Even mild manifestations of hyperthyroidism caused by the drug should be avoided in patients with coronary artery disease, heart failure, or tachyarrhythmia. Thyroid hormone levels must be monitored regularly when treating such patients.
If secondary hypothyroidism develops, the cause should be identified before initiating replacement therapy. If necessary, a course of replacement therapy should be administered to compensate for adrenal insufficiency.
If functional autonomy of the thyroid gland is suspected, TSH levels should be determined or a thyroid scintigraphy should be performed before starting treatment with this drug.
When initiating levothyroxine therapy in premature newborns with very low birth weight, hemodynamic parameters must be monitored, as circulatory disturbances may occur due to immature adrenal function.
Postmenopausal women with hypothyroidism who are at increased risk of developing osteoporosis should avoid very high serum levothyroxine levels that exceed physiological levels. Therefore, laboratory parameters of thyroid function must be carefully monitored.
Levothyroxine should not be prescribed to patients with hyperthyroidism who are undergoing therapy with antithyroid medications for the treatment of hyperthyroidism.
Thyroid hormones should not be used for weight loss. Administration of levothyroxine does not result in weight loss in patients with euthyroidism. Higher doses may lead to serious or even life-threatening adverse reactions. High-dose levothyroxine should not be combined with certain substances intended for weight loss (e.g., sympathomimetics) (see the “Overdose” section).
If it is necessary to switch from one levothyroxine-containing medication to another, careful monitoring—including clinical and laboratory monitoring—is required during the transition period due to the potential risk of thyroid dysfunction. Some patients may require a dose adjustment.
Concomitant use of orlistat and levothyroxine may lead to the development of hypothyroidism and/or worsening of hypothyroidism control (see the “Interactions with Other Medications and Other Interactions” section). Patients taking levothyroxine should consult their doctor before starting, stopping, or changing their orlistat treatment, as orlistat and levothyroxine must be taken at different times, and the levothyroxine dose may need to be adjusted. Subsequent monitoring of serum hormone levels in patients is recommended.
Use the drug with caution in patients with diabetes mellitus and in patients taking anticoagulants (see the section “Interactions with Other Medications and Other Types of Interactions”).
Effect on Laboratory Tests
Biotin may interfere with immunological thyroid assays based on the biotin/streptavidin interaction, leading to falsely low or falsely high test results. The risk of interference increases with higher doses of biotin.
When interpreting laboratory test results, the potential for biotin interference should be considered, especially if there is a lack of consistency with the clinical picture.
Patients taking products containing biotin should inform laboratory staff when thyroid function tests are to be performed. Alternative tests that are not affected by biotin should be used if available (see the section “Interactions with Other Medications and Other Interactions”).
This medication contains less than 1 mmol of sodium (23 mg) per tablet; therefore, it is essentially sodium-free.
Use During Pregnancy or Breastfeeding.
Treatment with this medication for hypothyroidism should be continued during pregnancy or breastfeeding. During pregnancy, it may be necessary to increase the dose of the medication. Since serum TSH levels may rise as early as the 4th week of pregnancy, pregnant women taking levothyroxine should have their TSH levels checked during each trimester. Serum TSH levels in pregnant women should be within the appropriate ranges established for each trimester. To correct elevated serum TSH levels, the dose of levothyroxine should be increased. Since postnatal TSH levels correspond to those present prior to conception, the levothyroxine dose should be adjusted immediately after delivery to match the pre-pregnancy dose. The target serum TSH level should be established 6–8 weeks after delivery.
Pregnancy
There are no data on teratogenicity and/or fetotoxicity when the drug is taken at recommended therapeutic doses. Taking very high doses of levothyroxine during pregnancy may adversely affect the fetus and the child’s postnatal development.
Combination therapy with levothyroxine and antithyroid drugs is not prescribed during pregnancy for the treatment of hyperthyroidism, as this combination requires higher doses of antithyroid drugs, which can cross the placenta and may cause hypothyroidism in the newborn. A thyroid suppression test is not performed during pregnancy, as the use of radioactive substances is contraindicated during pregnancy.
Breastfeeding
Levothyroxine passes into breast milk; however, when the drug is used at the recommended therapeutic doses, the concentration of the drug in breast milk is insufficient to cause hyperthyroidism or suppress TSH secretion in the infant.
Effect on the ability to drive or operate machinery.
There are no data on the possible effects on the ability to drive or operate complex machinery. However, since levothyroxine is identical in action to the natural thyroid hormone, Eutirox is not expected to affect reaction time when driving or operating machinery.
Directions for Use and Dosage
Dosage.
To treat each individual patient according to their specific needs, Eutirox is available in tablets containing 25 mcg to 150 mcg of levothyroxine sodium. Therefore, patients are generally prescribed only 1 tablet per day.
Dosage information is for guidance only.
The daily dose is determined individually, based on laboratory test results and the clinical presentation of the disease.
Since elevated T4 and fT4 levels have been observed in some patients during levothyroxine therapy, the baseline serum thyroid-stimulating hormone (TSH) level is a more reliable indicator for subsequent dose adjustments.
Thyroid hormone therapy should be initiated at a low dose and gradually increased (every 2–4 weeks) to the required therapeutic dose.
In elderly patients, patients with coronary artery disease, and patients with severe or long-standing hypothyroidism, treatment should be initiated with particular caution, starting with low doses (12.5 μg per day), and the dose should be increased to a maintenance dose at longer intervals (gradually by 12.5 mcg every 2 weeks), with regular monitoring of thyroid hormone levels. It should be noted that prescribing doses lower than the optimal dose, which ensures complete replacement therapy, does not result in full correction of TSH levels.
Clinical experience shows that lower doses are sufficient for patients with low body weight and for patients with large nodular goiters.
| Indications | Recommended Doses
(levothyroxine sodium, mcg/day) |
|||||||||||||||
| Treatment of benign euthyroid goiter | 75–200 | |||||||||||||||
| Prevention of recurrence after surgical treatment of euthyroid goiter | 75–200 | |||||||||||||||
For replacement therapy of hypothyroidism in adults:
|
25–50
100–200 |
|||||||||||||||
For replacement therapy of hypothyroidism in children:
|
12.5–50
100–150 mcg/m² of body surface area |
|||||||||||||||
| As an adjunctive medication during antithyroid therapy for hyperthyroidism | 50–100 | |||||||||||||||
| Suppressive therapy for thyroid cancer | 150–300 | |||||||||||||||
| As a diagnostic agent during thyroid suppression testing |
|
The daily dose may be taken in a single dose.
Take the daily dose in the morning on an empty stomach, 30 minutes before a meal, with a small amount of water (half a glass of water).
Eutirox should be used for life as replacement therapy for hypothyroidism, following surgical procedures (strumectomy or thyroidectomy), and to prevent recurrence after removal of an euthyroid goiter. Combination therapy with thyreostatics should be prescribed after achieving a euthyroid state.
For the benign form of euthyroid goiter, the duration of treatment ranges from 6 months to 2 years. If the condition does not improve after treatment, surgical intervention or radioactive iodine therapy should be considered.
Children.
For newborns and infants with congenital hypothyroidism, where rapid achievement of a therapeutic effect is critical, the recommended initial dose is 10 to 15 mcg/kg of body weight per day for the first 3 months. Thereafter, the dose is adjusted individually, depending on clinical indicators and thyroid-stimulating hormone (TSH) levels.
For infants, the daily dose should be administered in a single dose 30 minutes before the first feeding. Dissolve the tablet in water to form a suspension, which should be prepared immediately before administration, and administer after adding a small amount of additional liquid.
Overdose
Elevated levels of T3 (triiodothyronine) are a reliable indicator of overdose, more so than elevated levels of T4 and free T4 (fT4) in serum.
An overdose may result in symptoms characteristic of increased metabolism (see the “Adverse Reactions” section).
In case of overdose, discontinue the drug and perform laboratory tests.
If symptoms manifest as pronounced beta-sympathomimetic effects, such as tachycardia, restlessness, nervous agitation, or hyperkinesia, beta-blockers should be prescribed. If the dose is significantly exceeded, plasmapheresis is recommended.
In rare cases, patients prone to seizures may experience seizures if the individual tolerable dose of the drug is exceeded.
An overdose of levothyroxine may cause symptoms of hyperthyroidism and lead to acute psychosis, especially in patients at risk of developing psychotic disorders.
There have been several reports of sudden fatal coronary events in patients who have abused (exceeded the recommended dosage) levothyroxine for many years.
Side Effects
Clinical symptoms of hyperthyroidism may occur in the event of an overdose, if the dose exceeds the patient’s individual tolerance for levothyroxine, or if the dose is increased rapidly at the start of treatment. Symptoms: Cardiovascular system: cardiac arrhythmias (atrial fibrillation, extrasystoles), tachycardia, angina, palpitations, hot flashes; nervous system: headache, insomnia, anxiety, pseudotumor cerebri, tremor; gastrointestinal system: vomiting, diarrhea, weight loss; skin and musculoskeletal system: increased sweating, muscle weakness, and cramps; general disorders: fever, menstrual irregularities.
In such cases, the daily dose of the drug should be reduced or treatment should be interrupted for several days. Once the side effects have subsided, treatment may be resumed.
In cases of hypersensitivity to the drug’s components, allergic reactions may occur on the skin (rash, hives) and in the respiratory tract, including skin rashes, itching, hives, and shortness of breath. There have been reports of cases of angioedema (Quincke’s edema).
Shelf life
3 years.
Storage conditions
Store at a temperature not exceeding 25 °C in the original packaging. Keep out of reach of children!
Packaging
25 tablets per blister pack. 2 or 4 blister packs per cardboard box.
.
Manufacturer
Merck Healthcare KGaA, Germany.
Address
Frankfurter Strasse 250, 64293 Darmstadt, Germany.