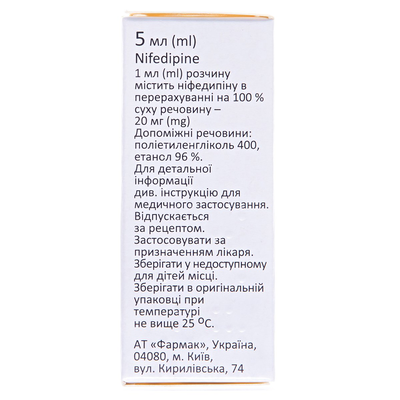


Pharmadipin drops, 2% solution, 5 mL per bottle.
Composition
Active ingredient: nifedipine;
1 mL of solution contains 20 mg of nifedipine calculated as 100% dry weight (30 drops);
Excipients: polyethylene glycol 400, 96% ethanol.
Dosage Form
Oral drops.
Main physicochemical properties: a clear yellow or greenish-yellow viscous liquid with a faint alcohol odor.
Pharmacotherapeutic group
Selective calcium antagonists with a predominant effect on blood vessels. ATX code: C08C, A05.
Pharmacological properties
Pharmacodynamics.
Pharmadipine® has antianginal and antihypertensive effects. It blocks the influx of calcium ions into cardiomyocytes and smooth muscle cells of the coronary and peripheral arteries through slow, voltage-gated calcium channels in cell membranes. It relaxes vascular smooth muscle, relieves spasms, and dilates the coronary and peripheral arteries, thereby reducing peripheral vascular resistance, blood pressure, afterload, and myocardial oxygen demand; it slightly reduces myocardial contractility and slightly reduces platelet aggregation.
Pharmacokinetics.
When taken orally, it is well absorbed from the gastrointestinal tract; bioavailability is 40–60%. The effect develops particularly rapidly (within 5–10 minutes) following sublingual administration. The maximum effect is usually observed after 30–40 minutes. Food intake has no significant effect on the rate of absorption. The hemodynamic effect persists for 4–6 hours. Up to 90% of nifedipine is bound to plasma proteins. It is metabolized in the liver and excreted from the body primarily as inactive metabolites. The total clearance of nifedipine ranges from 0.4 to 0.6 L/kg/h. The half-life is 2–4 hours. In the elderly and in patients with liver cirrhosis, the metabolism of nifedipine is slowed, so the drug’s half-life may be prolonged by nearly a factor of 2, requiring a reduction in dose and longer intervals between doses. Nifedipine does not accumulate in the body. In small amounts, it crosses the blood-brain and placental barriers and passes into breast milk.
Indications
Hypertension (for the treatment of hypertensive crises).
Contraindications
- Acute myocardial infarction (within the first 4 weeks);
- cardiogenic shock;
- severe aortic and mitral stenosis;
- unstable angina;
- Do not use for the treatment of angina attacks or for secondary prevention of myocardial infarction;
- decompensated heart failure;
- hypotension (systolic blood pressure (BP) below 90 mm Hg)
- ventricular tachycardia with a widened QRS complex;
- sick sinus syndrome;
- Wolf-Parkinson-White (WPW) syndrome, Lown-Ganong-Levine (LGL) syndrome;
- second- and third-degree AV block;
- Porphyria;
- ileostomy following proctocolectomy;
- Hypersensitivity to nifedipine or other components of the drug;
- Hypersensitivity to other dihydropyridines;
- Do not take concomitantly with rifampicin.
Drug Interactions and Other Interactions
Drugs that affect the efficacy of nifedipine.
Nifedipine is metabolized via the cytochrome P450 ZA4 system, which is located in the intestinal mucosa and the liver. Consequently, drugs that inhibit or induce this enzyme system may alter the “first-pass effect” (following oral administration) or the clearance of nifedipine.
When nifedipine is used in combination with the following medications, the extent and duration of the interaction should be taken into account.
Rifampicin
Rifampicin significantly induces the cytochrome P450 ZA4 system. When used concomitantly with rifampicin, the bioavailability of nifedipine is significantly reduced, thereby diminishing its efficacy. Therefore, the combination of nifedipine and rifampicin is contraindicated.
When the following weak or moderate inhibitors of the cytochrome P450 ZA4 system are used concomitantly, blood pressure should be monitored and, if necessary, a reduction in the nifedipine dose should be considered.
Macrolide antibiotics (e.g., erythromycin)
No studies have been conducted on the interaction between nifedipine and macrolide antibiotics. Some macrolide antibiotics inhibit the systemic metabolism of other drugs via cytochrome P450 ZA4. Therefore, the possibility of increased nifedipine concentrations in plasma cannot be ruled out when both drugs are used concomitantly.
Azithromycin, which is structurally similar to other macrolide antibiotics, does not inhibit CYP4A4.
HIV protease inhibitors (e.g., ritonavir)
No clinical study has yet been conducted to investigate the potential for interactions between nifedipine and certain anti-HIV protease inhibitors. It is known that drugs in this class inhibit the cytochrome P450 ZA4 system. In addition, drugs in this class inhibit the cytochrome P450 ZA4-mediated systemic metabolism of nifedipine in vitro. When used concomitantly with nifedipine, a significant increase in plasma concentrations of nifedipine cannot be ruled out due to a reduction in first-pass metabolism and a decrease in the rate of elimination from the body.
Azole antifungals (e.g., ketoconazole)
No clinical study has yet been conducted to investigate the potential for interactions between nifedipine and certain azole antifungals. It is known that drugs in this class inhibit the cytochrome P450 ZA4 system. When administered orally concomitantly with nifedipine, a significant increase in the systemic bioavailability of nifedipine due to reduced first-pass metabolism cannot be ruled out.
Fluoxetine
No clinical study has yet been conducted to investigate the potential for an interaction between nifedipine and fluoxetine. It is known that fluoxetine inhibits cytochrome P450 ZA4-mediated metabolism of nifedipine in vitro. When both drugs are administered concomitantly, an increase in plasma concentrations of nifedipine cannot be ruled out.
Nefazodone
No clinical study has yet been conducted to investigate the potential for an interaction between nifedipine and nefazodone. It is known that nefazodone inhibits the in vitro metabolism of other drugs mediated by the cytochrome P450 ZA4 system. When both drugs are used concomitantly, an increase in plasma nifedipine concentrations cannot be ruled out.
Quinucristine/dalfopristine
Concomitant use of quinacristine/dalfopristin and nifedipine may lead to increased plasma concentrations of nifedipine.
Valproic acid
No clinical study has yet been conducted to investigate the potential for an interaction between nifedipine and valproic acid. It is known that valproic acid increases the plasma concentration of the structurally similar calcium channel blocker nimodipine due to enzyme inhibition. Therefore, an increase in nifedipine plasma concentrations and enhanced efficacy cannot be ruled out.
Cimetidine
By inhibiting cytochrome P450 ZA4, cimetidine increases the plasma concentration of nifedipine and may enhance its antihypertensive effect.
Cisapride
Concomitant use of cisapride and nifedipine may lead to increased plasma concentrations of nifedipine.
Antiepileptic drugs that induce the cytochrome P450 ZA4 system, such as phenytoin, carbamazepine, and phenobarbital
Phenytoin induces the cytochrome P450 ZA4 system. When used concomitantly with phenytoin, the bioavailability of nifedipine is reduced and its efficacy is diminished. When both drugs are used concomitantly, the clinical response to nifedipine therapy should be monitored, and an increase in the nifedipine dose should be considered if necessary. If the nifedipine dose is increased during concomitant use of both drugs, consider reducing the nifedipine dose when phenytoin is discontinued.
No clinical studies have been conducted to investigate the likelihood of potential interactions between nifedipine and carbamazepine or phenobarbital. It is known that both drugs reduce plasma concentrations of the structurally similar calcium channel blocker nimodipine through enzyme induction. Therefore, a reduction in plasma concentrations of nifedipine and a decrease in efficacy cannot be ruled out.
Antihypertensive Drugs
Nifedipine may potentiate the antihypertensive effect of concomitant antihypertensive drugs, such as: diuretics, β-blockers, ACE inhibitors, AT1 receptor antagonists, other calcium channel blockers, α-adrenergic blockers, PDE5 inhibitors, α-methyldopa, and magnesium sulfate.
Concomitant use of nifedipine with β-blockers requires careful monitoring of the patient, as there have been isolated reports of exacerbation of heart failure.
Digoxin and Theophylline
The combination of nifedipine with digoxin and theophylline is generally well tolerated by patients; very rarely, elevated plasma levels of digoxin and theophylline may occur (the plasma concentration of the latter should be monitored). Therefore, the patient should be monitored for symptoms of digoxin overdose, and if necessary, the glycoside dose should be reduced based on the digoxin concentration in the blood plasma.
Amiodarone and Quinidine
Amiodarone and quinidine may enhance the negative inotropic effect of nifedipine. When nifedipine and quinidine are used concomitantly, a decrease in quinidine levels has been observed in some cases, and upon discontinuation of nifedipine, a sharp increase in plasma quinidine concentration has been observed. Therefore, when nifedipine is used concomitantly or discontinued, it is recommended to monitor quinidine plasma concentrations and adjust the quinidine dose as necessary. Some authors have reported increased plasma concentrations of nifedipine when both drugs are used concomitantly, but other authors have not observed changes in the pharmacokinetics of nifedipine.
Therefore, when quinidine is added to a nifedipine regimen, blood pressure should be carefully monitored. If necessary, the nifedipine dose should be reduced.
Tacrolimus
Tacrolimus is known to be metabolized via the cytochrome P450 ZA4 system. Published data indicate that, in rare cases, the tacrolimus dose may need to be reduced when used concomitantly with nifedipine. When both drugs are used concomitantly, tacrolimus plasma concentrations should be monitored, and, if necessary, a reduction in the tacrolimus dose should be considered.
Other Types of Interactions
Grapefruit juice
Grapefruit juice inhibits the cytochrome P450 ZA4 system. Consuming grapefruit juice with nifedipine leads to increased plasma concentrations of the drug and a prolonged duration of action of nifedipine due to reduced first-pass metabolism or reduced clearance. As a result, the drug’s antihypertensive effect may be enhanced. After regular consumption of grapefruit juice, this effect may persist for at least 3 days after the last juice-containing beverage.
Therefore, grapefruit and grapefruit juice should be avoided during nifedipine therapy.
The use of nifedipine may lead to a false increase in the results of spectrophotometric determination of vanillylmandelic acid concentration in urine (however, this effect is not observed with high-performance liquid chromatography).
Special Considerations
Caution should be exercised when administering Pharmadipin® to patients with marked narrowing of the gastrointestinal tract due to the potential for the development of obstructive symptoms. Bezoars may occur very rarely and may require surgical intervention.
In rare cases, obstructive symptoms have been reported in patients with no history of gastrointestinal disorders.
Use of Pharmadipin® may lead to false-positive results on X-rays using barium contrast media (e.g., defects in a dental filling may be interpreted as a polyp).
Patients with hepatic insufficiency require close monitoring and, in severe cases, a dose reduction.
Nifedipine is metabolized via the cytochrome P450 ZA4 system; therefore, drugs that inhibit or induce this enzyme system may alter the “first-pass” metabolism or clearance of nifedipine.
Drugs that are mild or moderate inhibitors of the cytochrome P450 ZA4 system and may lead to increased plasma concentrations of nifedipine include: macrolide antibiotics (e.g., erythromycin), HIV protease inhibitors (e.g., ritonavir), azole antifungals (e.g., ketoconazole), the antidepressants nefazodone and fluoxetine, quinopristin/dalfopristin, valproic acid, and cimetidine.
If Pharmadipine is used concomitantly with these medications, blood pressure should be monitored and, if necessary, a reduction in the dose of nifedipine® should be considered.
The drug should not be used if there may be a link between previous use of nifedipine and ischemic pain. In patients with angina, episodes may occur more frequently, and their duration and intensity may increase, especially at the start of treatment.
Medications containing nifedipine as the active ingredient should not be used in patients experiencing an acute episode of stable angina.
Particular caution should be exercised when prescribing this medication to patients undergoing hemodialysis, or those with malignant hypertension or hypovolemia, as vasodilation may cause a significant decrease in blood pressure in these patients. The use of nifedipine in patients with diabetes mellitus may require adjustment of treatment.
This medication contains a small amount of ethanol (alcohol), less than 100 mg per dose.
Pregnancy and lactation.
Pregnancy.
Nifedipine is contraindicated during pregnancy.
Breastfeeding.
Nifedipine passes into breast milk; therefore, breastfeeding should be discontinued while taking this medication.
Fertility.
Some in vitro studies have revealed a correlation between the use of calcium channel blockers, particularly nifedipine, and reversible biochemical changes in sperm that impair their fertilization capacity. If in vitro fertilization attempts have been unsuccessful, and in the absence of other explanations, calcium channel blockers such as nifedipine may be considered a possible cause of this phenomenon.
Affects the ability to operate vehicles and machinery.
While using this medication, you should refrain from potentially hazardous activities that require increased attention (operating vehicles and machinery, etc.).
Dosage and Administration
Pharmadipine® is used to treat hypertensive crises as an emergency medication. It is not recommended to use this dosage form for long-term treatment.
If a course of antihypertensive therapy is necessary, the medication and dosage form are selected by a physician.
In the event of a sudden and significant increase in blood pressure, the initial single dose for adults is 3–5 drops (2–3.35 mg), for the elderly—no more than 3 drops (2 mg), taken sublingually or dripped onto a piece of a cracker or sugar cube, holding it in the mouth for as long as possible. If the effect is insufficient, the dose may be gradually increased until a clinically significant effect is achieved. Thereafter, in cases of elevated blood pressure, this dose should be used as a guide. If necessary (blood pressure rising to 190/100 mm Hg – 220/110 mmHg), the single dose may be gradually increased in some cases to 10–15 drops (6.7–10 mg), taking into account the patient’s individual blood pressure fluctuations.
The individual sensitivity of each patient to Pharmadipin® must be taken into account. In such cases, the dose should be titrated individually, starting with 3 drops, and gradually increased by 2–3 drops (1.34–2 mg) until a clinical effect is achieved.
Exceeding the initial dose may lead to a sharp drop in blood pressure!
Children.
This medication is not indicated for use in children (under 18 years of age).
Overdose
Symptoms of acute nifedipine intoxication: impaired consciousness up to coma, decreased blood pressure, tachycardia/bradycardia, hyperglycemia, metabolic acidosis, hypoxia, cardiogenic shock accompanied by pulmonary edema.
Treatment. Emergency measures should primarily be aimed at removing the drug from the body and restoring stable hemodynamics.
After oral ingestion, it is recommended to completely empty the stomach, if necessary in combination with small bowel lavage.
Elimination of the drug from the body should be as complete as possible, including from the small intestine, especially in cases of intoxication with sustained-release nifedipine preparations, to prevent absorption of the active ingredient.
Since nifedipine binds strongly to plasma proteins and has a relatively small volume of distribution, hemodialysis is ineffective, but plasmapheresis is recommended.
Bradycardia can be reversed with beta-sympathomimetics. If the heart rate slows to a life-threatening level, the use of an artificial pacemaker is recommended.
Hypotension resulting from cardiogenic shock and vasodilation can be treated with calcium preparations (10–20 mL of a 10% solution of calcium chloride or calcium gluconate is administered intravenously slowly, then repeated as necessary). As a result, serum calcium levels may reach the upper limit of normal or be slightly elevated. If calcium administration is not sufficiently effective, it is advisable to use sympathomimetics, such as dopamine or norepinephrine. Doses of these drugs are adjusted based on the therapeutic effect achieved.
Additional fluid administration should be approached with great caution, as it increases the risk of cardiac overload.
Side Effects
When the recommendations for use are followed, side effects are mild and reversible and generally do not require discontinuation of therapy.
With frequent and uncontrolled use, side effects characteristic of drugs in this pharmacological group may occur.
Blood and lymphatic system: leukopenia, agranulocytosis, anemia, thrombocytopenia.
Immune system disorders: allergic reactions, allergic edema/angioedema (including laryngeal edema*), anaphylactic/anaphylactoid reaction.
Psychiatric disorders: anxiety, agitation, sleep disturbances.
Nervous system disorders: headache, dizziness, migraine, vertigo, tremor, hypoesthesia, paresthesia, dysesthesia, drowsiness, loss of consciousness.
Metabolic disorders: hyperglycemia (should be taken into account in patients with diabetes mellitus).
Eye disorders: visual disturbances, eye pain.
Cardiac disorders: tachycardia, palpitations, chest pain (angina).
Vascular disorders: edema, vasodilation, hypotension.
Respiratory system: nosebleeds, nasal congestion, shortness of breath.
Gastrointestinal disorders: constipation, gastrointestinal and abdominal pain, nausea, dyspepsia, flatulence, dry mouth, gingival hyperplasia, bezoar, dysphagia, intestinal obstruction, intestinal ulcer, vomiting, gastroesophageal sphincter insufficiency.
Liver and biliary tract disorders: transient elevation of liver enzymes, jaundice.
Skin and subcutaneous tissue disorders: erythema, toxic epidermal necrolysis, photosensitivity, purpura, pruritus, urticaria, rash.
Musculoskeletal, connective tissue, and bone disorders: muscle spasms, joint swelling, arthralgia, myalgia.
Renal and urinary tract disorders: polyuria, dysuria.
Reproductive system and breast disorders: erectile dysfunction.
General disorders: malaise, nonspecific pain, fever.
*May lead to life-threatening consequences.
In patients with malignant hypertension and hypovolemia who are undergoing hemodialysis, a significant decrease in blood pressure may occur due to vasodilation.
Shelf life
3 years.
Do not use this medication after the expiration date printed on the package.
Storage conditions
Store in the original packaging at a temperature not exceeding 25 °C.
Keep out of reach of children.
Packaging
5 mL or 25 mL in a vial. 1 vial per package.
Manufacturer
PJSC “Farmak.”