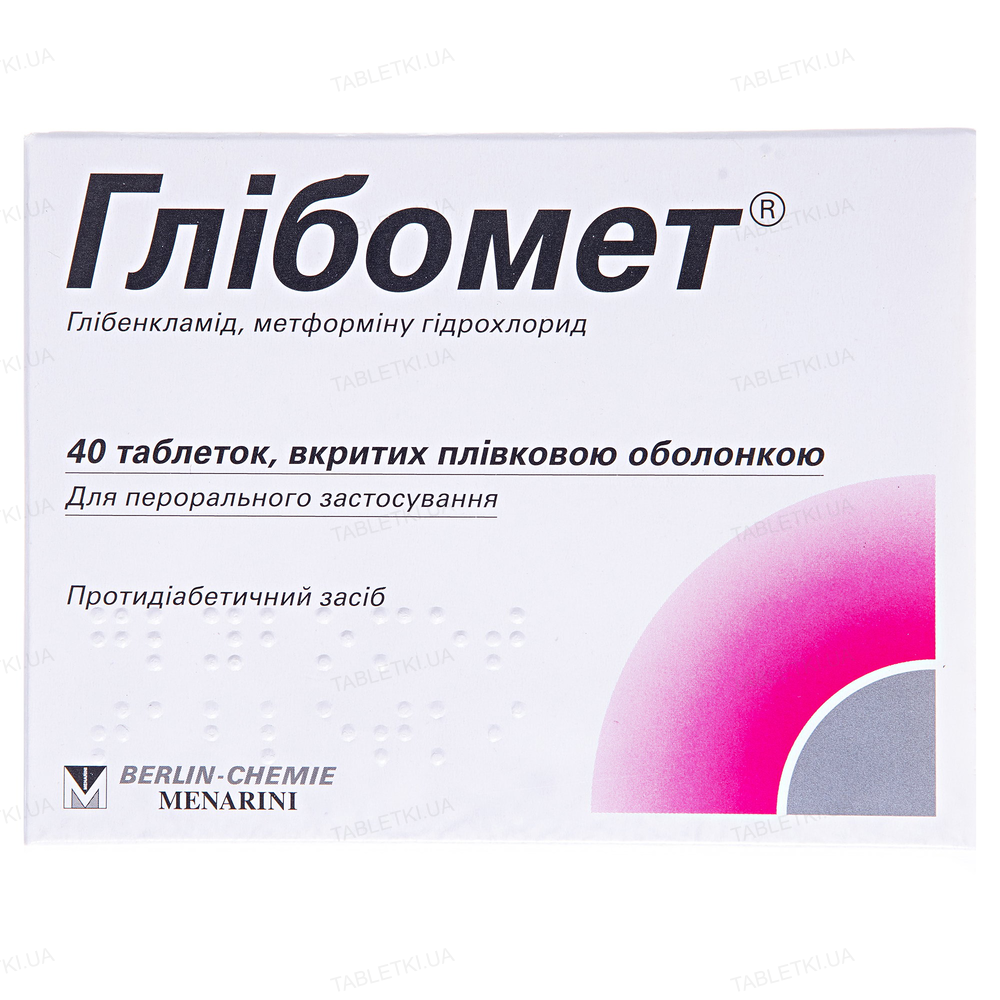


Glibomet tablets, film-coated, No. 40 (20 x 2)
Composition
Active ingredients: metformin hydrochloride and glibenclamide;
1 film-coated tablet contains 400 mg of metformin hydrochloride and 2.5 mg of glibenclamide;
Excipients: colloidal anhydrous silicon dioxide, polyethylene glycol 6000, povidone, croscarmellose sodium, microcrystalline cellulose, glycerin dibehenate, magnesium stearate; Opadry White coating (hypromellose, titanium dioxide (E 171), talc, polyethylene glycol 6000).
Dosage Form
Film-coated tablets.
Main physical and chemical properties: white to almost white, round, biconvex film-coated tablets, with a score line on one side and the imprint “2.5” on the flat side, and the imprints “B” and “1” on the semicircular halves of the other side.
Pharmacotherapeutic group
Antidiabetic agents. Combination of oral hypoglycemic agents.
ATC code A10B D02.
Pharmacological properties
Pharmacodynamics.
Glibomet® contains glibenclamide—a second-generation sulfonylurea that, at low doses, affects the kinetics of insulin production for a relatively short period of time and repeatedly after each dose—and metformin — a biguanide that stimulates peripheral tissue sensitivity to insulin (increased insulin binding to receptors, enhanced effect at the post-receptor level), regulates glucose absorption in the intestine, inhibits gluconeogenesis and restores lipid metabolism, reduces excess body weight in overweight patients with diabetes, and also reduces platelet adhesiveness and exerts a fibrinolytic effect; all of these effects are associated with improved tolerability, ease of use, and a reduced risk of lactic acidosis compared to other biguanides.
The synergistic action of the drug’s two active components: the stimulating effect of sulfonylurea on endogenous insulin production (pancreatic action) and the biguanide’s direct effect on muscle tissue, which leads to a significant increase in glucose uptake (extrapancreatic action), and liver tissue (decreased gluconeogenesis)—allows, at a specific dose ratio, for a reduction in the concentration of each component, which helps prevent excessive stimulation of pancreatic beta cells, and, consequently, a reduced risk of organ dysfunction, while also ensuring safety and a lower incidence of side effects.
Pharmacokinetics.
Glibenclamide is 84% absorbed in the gastrointestinal tract and is excreted via the gastrointestinal tract and in the urine after being metabolized in the liver into inactive metabolites; the half-life is 5 hours; the degree of plasma protein binding is 97%.
Metformin is absorbed in the gastrointestinal tract; it is rapidly excreted in feces and urine; it does not bind to plasma proteins and is not metabolized in the body; the plasma half-life is approximately two hours.
Preclinical Safety Data
Results of acute toxicity studies conducted in animals demonstrated the absence of synergistic toxicity among the active ingredients. Oral administration to animals for 26 weeks did not result in death, changes in health status, or a decrease in water or food intake.
Administration did not affect growth curves, blood cell counts, liver function, blood chemistry tests, urinalysis, body weight, or the macroscopic and microscopic appearance of organs and systems.
Teratogenicity studies revealed no toxic effects on pregnancy or the fetus.
Indications
Type 2 diabetes mellitus (non-insulin-dependent diabetes mellitus—NIDDM) when dietary therapy alone or dietary therapy combined with sulfonylurea or biguanide medications is insufficiently effective.
Contraindications
- Hypersensitivity to the active ingredients (glibenclamide, metformin), to other components of the drug, to other sulfonylurea drugs, or to sulfonamides;
- Complete lack of response to glibenclamide treatment in type 2 diabetes mellitus;
- gestational diabetes;
- Type 1 diabetes (insulin-dependent);
- any type of acute metabolic acidosis (e.g., lactic acidosis, diabetic ketoacidosis);
- diabetic coma and precoma;
- diabetes with a history of episodes of lactic acidosis;
- pancreatectomy;
- liver failure;
- severe renal insufficiency (glomerular filtration rate (GFR) < 30 mL/min);
- concomitant therapy with diuretics or antihypertensive drugs that may cause worsening of renal function; use within 48 hours before or after intravenous administration of iodine-containing radiocontrast agents;
- severe cardiovascular diseases (NYHA [New York Heart Association] Class I–IV heart failure, cardiogenic or toxic shock, recent myocardial infarction, unstable angina, peripheral arterial circulatory disorders);
- respiratory failure;
- adrenocortical insufficiency;
- acute alcohol intoxication, chronic alcoholism;
- a strict low-calorie diet, especially fasting, and/or malnutrition;
- acute conditions associated with a risk of renal dysfunction: dehydration, severe infectious diseases;
- severe dystrophic diseases;
- severe acute bleeding;
- shock;
- gangrene;
- pregnancy and breastfeeding;
- concomitant treatment with bosentan;
- use within 2 days before or after surgery;
- porphyria;
- concomitant therapy with miconazole (see the section “Interactions with Other Medications and Other Types of Interactions”).
Interactions with Other Medications and Other Types of Interactions
Combinations that are contraindicated.
Related to glibenclamide.
Miconazole (for systemic use, oral gel) potentiates the hypoglycemic effect, with possible onset of hypoglycemia symptoms or even coma (see the “Contraindications” section).
Combinations not recommended for use.
Related to sulfonylurea derivatives.
Alcohol—Antabuse-like effect (alcohol intolerance), especially when used with chlorpropamide, glibenclamide, glipizide, or tolbutamide.
Enhanced hypoglycemic effect (due to inhibition of compensatory reactions) may lead to hypoglycemic coma.
While taking this medication, avoid alcohol and medications containing alcohol.
Phenylbutazone (for systemic use) potentiates the hypoglycemic effect of sulfonylurea derivatives (by displacing their binding to plasma proteins and/or reducing their excretion). It is recommended to use another anti-inflammatory drug with fewer interactions or to advise the patient on the need for increased self-monitoring. If necessary, the dose of the drug should be adjusted during and after therapy with the anti-inflammatory drug.
Antibacterial agents. Concomitant use of sulfonylurea derivatives, including glibenclamide, with certain antibacterial agents, such as sulfonamides (e.g., co-trimoxazole), levofloxacin, or clarithromycin, may increase the risk of severe hypoglycemia.
Cyclophosphamide. Concomitant use of sulfonylureas, including glibenclamide, and cyclophosphamide may increase the risk of severe hypoglycemia.
Pheniramidol. Concomitant use of sulfonylureas, including glibenclamide, and pheniramidol increases the risk of severe hypoglycemia.
Applies to all antidiabetic agents.
Danazol. If this combination is unavoidable, the patient should be advised to monitor blood glucose levels more closely. If necessary, the dose of the antidiabetic medication should be adjusted during and after danazol therapy.
Associated with metformin.
Alcohol. Increased risk of lactic acidosis during acute alcohol intoxication, especially in cases of
- fasting or malnutrition;
- liver failure.
Alcohol consumption and the use of alcohol-containing medications should be avoided.
Iodine-containing radiocontrast agents. Metformin should be discontinued before or during an X-ray examination and should not be resumed until at least 48 hours after the examination is completed and only after re-evaluation of renal function and confirmation that there has been no further deterioration in renal function (see sections “Dosage and Administration” and “Special Considerations for Use”).
Combinations that should be used with caution.
Interactions with all antidiabetic agents.
Chlorpromazine. When taken in high doses (100 mg of chlorpromazine per day), blood glucose levels increase (due to reduced insulin production). Patients should be advised to monitor their blood glucose levels more closely. If necessary, the dose of the antidiabetic medication should be adjusted during and after treatment with antipsychotics.
Perexilin. The use of perexilin may lead to the development of hypoglycemia. When perexilin is used concomitantly with antidiabetic medications, the patient should be advised to monitor blood glucose levels more closely.
Corticosteroids (glucocorticoids) and tetracosactides (systemic and topical). Blood glucose levels increase, sometimes accompanied by ketosis (reduced carbohydrate tolerance with corticosteroid use, relative insulin deficiency). Patients should be advised of the need for closer monitoring of blood glucose levels. If necessary, the dose of the antidiabetic medication should be adjusted during and after corticosteroid therapy.
β2-agonists. Blood glucose levels increase. Patients should be advised to monitor their blood glucose levels more closely and, if necessary, switch to insulin therapy.
Angiotensin-converting enzyme (ACE) inhibitors (e.g., captopril, enalapril). Blood glucose levels decrease. If necessary, the dose of Glibomet® should be adjusted during and after discontinuation of ACE inhibitors.
Metformin-related.
Organic cation transporters OCT1 and OCT2.
Metformin is a substrate for both OCT1 and OCT2 transporters.
Concomitant use of metformin with:
- OCT1 inhibitors (such as verapamil) may reduce the effectiveness of metformin;
- OCT1 inducers (such as rifampin) may increase the gastrointestinal absorption and efficacy of metformin;
- OCT2 inhibitors (such as cimetidine, dolutegravir, ranolazine, trimethoprim, vandetanib, isavuconazole) may reduce the renal excretion of metformin, leading to an increase in metformin plasma concentrations;
- inhibitors of both OCT1 and OCT2 transporters (such as crizotinib, olaparib) may affect the efficacy and renal excretion of metformin.
In patients with type 2 diabetes, the concomitant use of metformin (1,000 mg twice daily) and ranolazine at doses of 500 mg and 1,000 mg twice daily resulted in a 1.4-fold and 1.8-fold increase in metformin plasma exposure, respectively.
In a study involving 7 healthy volunteers, cimetidine, at a dose of 400 mg twice daily, increased the systemic exposure (AUC) of metformin by 50% and Cmax by 81%.
Therefore, extreme caution is recommended when these drugs are used concomitantly with metformin, especially in patients with impaired renal function, as metformin plasma concentrations may increase. Consider adjusting the metformin dose, as OCT inhibitors/inducers may affect the efficacy of metformin.
Other Interactions.
Certain medications may adversely affect renal function, which may increase the risk of lactic acidosis. These include, in particular, NSAIDs, including selective cyclooxygenase (COX-2) inhibitors, ACE inhibitors, angiotensin II receptor antagonists, and diuretics, particularly loop diuretics. Careful monitoring of renal function is necessary at the start of and during treatment with the above-mentioned drugs in combination with metformin.
Related to glibenclamide.
β-blockers, clonidine, reserpine, guanethidine, and sympathomimetics.
All β-blockers, clonidine, reserpine, guanethidine, and sympathomimetics mask symptoms of hypoglycemia such as palpitations and tachycardia. Most non-selective β-blockers increase the frequency and severity of hypoglycemic episodes. Patients should be warned, and blood glucose monitoring should be intensified, especially at the start of therapy.
Fluconazole. Prolongation of the half-life of sulfonylurea derivatives, with possible manifestations of hypoglycemia symptoms. Patients should be warned, and blood glucose levels should be monitored more closely. If necessary, the dose of the drug should be adjusted during and after fluconazole therapy.
Bosentan. Concomitant use increases the risk of hepatotoxicity; therefore, these medications should not be used together. There is a risk of reduced hypoglycemic effect of glibenclamide, as bosentan decreases the concentration of glibenclamide in plasma.
Other interactions to consider.
Related to glibenclamide.
Desmopressin. Reduced antidiuretic effect.
The hypoglycemic effect of sulfonylurea derivatives may be increased when used concomitantly with monoamine oxidase inhibitors, chloramphenicol, probenecid, salicylates, and sulfinpyrazone; and, conversely, may be reduced by oral contraceptives, thiazide diuretics, and barbiturates.
It should be noted that biguanides may enhance the effects of anticoagulants.
Colesvelam. When used concomitantly, it reduces the plasma concentration of glibenclamide, which may lead to a decrease in the hypoglycemic effect. This effect was not observed when glibenclamide was taken before the other medications. It is recommended to take Glibomet® at least 4 hours before taking colesevelam.
Special Considerations for Use
Any treatment, and in particular the switch from one hypoglycemic agent to another, must be prescribed by a physician. The patient must strictly follow the physician’s recommendations regarding the dosage and method of administration of the medication, as well as dietary guidelines and exercise regimen. It is recommended to periodically perform routine diagnostic tests (fasting and postprandial blood glucose, HbA1c).
Since glibenclamide is a sulfonylurea derivative, Glibomet® should be used only in patients with type 2 diabetes mellitus when dietary therapy is insufficiently effective.
If symptoms of hypoglycemia occur (see the “Adverse Reactions” section), administer carbohydrates (sugar); in more severe cases, which may lead to loss of consciousness, a slow intravenous infusion of glucose solution should be administered.
In cases of trauma, surgical procedures, infectious diseases, and febrile conditions, it is necessary to switch to temporary insulin therapy to ensure precise metabolic control.
The possible development of a disulfiram-like reaction after ingestion of ethyl alcohol must be taken into account.
Treatment must be discontinued 48 hours prior to angiography or urography and, if necessary, resumed 48 hours after the procedure.
According to the results of some epidemiological studies, treatment with glibenclamide was associated with an increased risk of cardiovascular death compared with treatment with gliclazide. An increased risk of cardiovascular death was observed, in particular, in patients with acute ischemic heart disease.
Lactic acidosis is a rare but very serious metabolic disorder that most often occurs during acute renal impairment, cardiorespiratory diseases, or sepsis. Metformin accumulation occurs during acute renal impairment and increases the risk of lactic acidosis.
In case of dehydration (due to severe diarrhea or vomiting, fever, or insufficient fluid intake), metformin should be temporarily discontinued, and it is recommended to consult a doctor. Medications that may cause acute renal failure (such as antihypertensives, diuretics, and NSAIDs [nonsteroidal anti-inflammatory drugs]) should be used with caution in patients receiving metformin. Other risk factors for lactic acidosis include alcohol abuse, hepatic insufficiency, inadequately controlled diabetes, ketosis, prolonged fasting, and any conditions that cause hypoxia, as well as the use of medications that may cause lactic acidosis (see the sections “Contraindications” and “Drug Interactions and Other Interactions”).
Patients and/or their caregivers should be informed of the risk of developing lactic acidosis. Lactic acidosis is characterized by acidotic dyspnea, abdominal pain, muscle cramps, asthenia, and a decrease in body temperature; coma may subsequently develop. If lactic acidosis is suspected, the patient should stop taking metformin and seek medical attention immediately. Diagnostic laboratory findings include a low blood pH (< 7.35), elevated plasma lactate levels (> 5 mmol/L), an increased anion gap, and a rising lactate-to-pyruvate ratio.
Diagnosis.
Lactic acidosis is characterized by acidotic dyspnea, abdominal pain, and hypothermia; coma may develop subsequently. Lactic acidosis should be suspected in the presence of nonspecific symptoms, such as severe fatigue and malaise, vomiting, muscle cramps, and gastrointestinal disturbances, such as abdominal pain and complete loss of appetite. Diagnostic laboratory findings include low blood pH, elevated plasma lactate levels (greater than 5 mmol/L), an increased anion gap, and a rising lactate-to-pyruvate ratio. If metabolic acidosis is suspected, further use of the drug should be discontinued immediately, and the patient should be hospitalized urgently. The risk of lactic acidosis depends on the accumulation of metformin in the body, which is possible in cases of impaired renal function. Therefore, renal function must be monitored before starting treatment and regularly throughout the course of therapy. Patients should be provided with comprehensive information regarding the risk of lactic acidosis.
Renal Function
Glomerular filtration rate (GFR) should be determined before starting treatment and regularly throughout therapy; see the “Dosage and Administration” section. Metformin is contraindicated in patients with an eGFR < 30 mL/min; treatment should be temporarily discontinued if conditions that may impair renal function develop; see the “Contraindications” section.
Deterioration of renal function in elderly patients is common and is not accompanied by specific symptoms. Special caution is required if there is a possibility of renal impairment, for example, after starting antihypertensive or diuretic therapy, as well as after starting therapy with nonsteroidal anti-inflammatory drugs (NSAIDs).
Administration of Iodine-Containing Contrast Media
Intravascular administration of iodine-containing radiopaque contrast media may cause contrast-induced nephropathy, leading to the accumulation of metformin and an increased risk of lactic acidosis. Metformin should be discontinued prior to such an examination; treatment may be resumed no earlier than 48 hours after the procedure, provided that renal function has been assessed and stable renal function has been confirmed (see the sections “Dosage and Administration” and “Drug Interactions and Other Interactions”).
Surgical Procedures
Metformin should be discontinued prior to any surgical procedure performed under general, spinal, or epidural anesthesia. Treatment may be resumed no earlier than 48 hours after the completion of surgery or the resumption of independent feeding, provided that renal function has been assessed and stable renal function has been confirmed.
Hypoglycemia
Since this medication contains a sulfonylurea derivative, its use is associated with a risk of hypoglycemia. Appropriate dose adjustment after the start of therapy helps prevent hypoglycemia. Treatment is indicated only for patients who maintain a regular eating schedule (including breakfast). Regular sugar intake is important, as the risk of hypoglycemia increases with delayed meals or insufficient or unbalanced sugar intake. The likelihood of hypoglycemia increases when following a low-calorie diet, after intense or prolonged physical activity, when consuming alcoholic beverages, or when used in combination with other hypoglycemic agents.
Elderly Patients
Age 65 years and older is an identified risk factor for the development of hypoglycemia in patients receiving sulfonylurea medications. Hypoglycemia may be difficult to diagnose in elderly patients. At the start of treatment and when using maintenance doses of glibenclamide, the dose should be carefully adjusted to reduce the risk of hypoglycemia (see the “Dosage and Administration” section).
Diagnosis.
Symptoms of hypoglycemia include: headache, hunger, nausea, vomiting, severe fatigue, sleep disturbances, nervousness, aggression, impaired concentration and reaction time, depression, confusion, speech impairment, visual disturbances, tremors, paralysis and paresthesia, dizziness, delirium, seizures, drowsiness, loss of consciousness, shallow breathing, and bradycardia. Excessive sweating, anxiety, tachycardia, hypertension, palpitations, angina, and arrhythmia may occur as a result of antiregulatory mechanisms triggered by hypoglycemia. These symptoms may be absent if hypoglycemia develops slowly, in the presence of autonomic neuropathy, or in patients taking beta-blockers, clonidine, reserpine, guanethidine, and other sympathomimetics.
Treatment of hypoglycemia.
If mild symptoms of hypoglycemia are present, without impaired consciousness or neurological symptoms, sugar should be taken immediately. The dose and/or diet should also be adjusted. In cases of severe hypoglycemia with impaired consciousness, coma or neurological symptoms may also occur; therefore, even before emergency hospitalization, the patient should receive immediate care; intravenous glucose administration is required immediately upon confirmation of the diagnosis or if such a diagnosis is suspected. If hypoglycemia is suspected, an examination by a specialist in a hospital setting is always necessary.
Individualized dosing and proper patient education are important factors in reducing the risk of hypoglycemic episodes. If a patient experiences recurrent hypoglycemic episodes—whether severe or associated with unpredictable situations—the appropriateness of changing therapy or prescribing an antidiabetic medication other than Glibomet® should be considered.
Factors that contribute to the development of hypoglycemia:
- concurrent alcohol consumption, particularly in combination with fasting;
- refusal to cooperate or (particularly in the case of elderly patients) the patient’s inability to cooperate;
- malnutrition, irregular eating patterns, skipping meals, fasting, or changes in diet;
- an imbalance between physical activity and sugar intake;
- renal failure;
- severe liver failure;
- an overdose of Glibomet®;
- certain endocrine disorders: insufficiency of the thyroid gland, parathyroid glands, and adrenal medulla;
- concomitant use with certain other medications (see the section “Interactions with Other Medications and Other Types of Interactions”).
Hepatic or renal insufficiency.
Changes in pharmacokinetic and/or pharmacodynamic characteristics may occur when Glibomet® is administered to patients with hepatic insufficiency or severe renal insufficiency. If hypoglycemia occurs in such patients, it may be persistent; therefore, appropriate treatment is necessary.
Patient Information.
The patient and their close relatives should be informed about the risk of hypoglycemia, its symptoms, appropriate treatment, and factors that contribute to its development. The risk of lactic acidosis should be considered, and the patient should be provided with relevant information if nonspecific symptoms appear, such as muscle cramps associated with gastrointestinal disturbances, abdominal pain and severe asthenia, shortness of breath accompanied by acidosis, a drop in body temperature, and coma.
Patients should be informed of the importance of adhering to a dietary regimen and a regular exercise program, and their glucose levels should be monitored regularly.
Potential Metabolic Decompensation
In the event of trauma, surgery, an infectious disease or a condition accompanied by a high body temperature, or other potential causes of diabetic decompensation, the appropriateness of temporarily using insulin instead of the current therapy should be considered to maintain adequate metabolic control.
Symptoms of hyperglycemia include frequent urination, intense thirst, and dry skin.
Concomitant use of glibenclamide and other medications
Concomitant use of glibenclamide with alcoholic beverages, phenylbutazone, or danazol is not recommended (see the section “Interactions with Other Medications and Other Types of Interactions”).
Other Precautions
All patients should follow a diet that ensures a regular intake of sugar throughout the day. Patients who are overweight should continue to follow a low-calorie diet.
Regular physical activity is just as important as taking Glibomet®.
Regular laboratory tests are required (blood glucose, HbA1c).
Patients with G6PD (glucose-6-phosphate dehydrogenase) deficiency may develop hemolytic anemia when taking sulfonylurea derivatives.
Since glibenclamide belongs to the sulfonylurea class, caution is recommended when prescribing Glibomet® to patients with G6PD deficiency. Consider treating such patients with medications other than sulfonylureas.
Metformin may lower serum vitamin B12 levels. The risk of low vitamin B12 levels increases with higher doses of metformin, longer duration of treatment, and/or in patients with risk factors known to cause vitamin B12 deficiency. If vitamin B12 deficiency is suspected (e.g., anemia or neuropathy), serum vitamin B12 levels should be monitored. Patients with risk factors for vitamin B12 deficiency may require periodic monitoring of vitamin B12 levels. Metformin therapy should be continued as long as it is well tolerated and there are no contraindications, and appropriate corrective treatment for vitamin B12 deficiency should be provided in accordance with current clinical guidelines.
Use During Pregnancy or Breastfeeding
This medication is contraindicated during pregnancy and while breastfeeding.
Pregnancy.
There are no preclinical or clinical data on the use of Glibomet® during pregnancy.
Glibomet® should not be used to treat diabetes during pregnancy. In cases of gestational diabetes, it is recommended to switch the patient from oral antidiabetic agents to insulin as soon as she begins planning a pregnancy or as soon as it becomes known that she is pregnant, as well as as soon as the patient begins breastfeeding.
It is recommended to monitor the newborn’s blood glucose levels. Animal studies have not revealed any teratogenic effects with the use of the combination of active ingredients (see the “Preclinical Safety Data” section).
Risks Associated with Diabetes.
Uncontrolled diabetes during pregnancy (gestational or other types of diabetes) increases the risk of congenital anomalies and perinatal mortality. Diabetes must be controlled during conception to reduce the risk of congenital anomalies.
Risks associated with metformin (see the “Preclinical Safety Data” section).
Animal studies have not revealed any teratogenic effects; therefore, fetal malformations are not expected in humans either, since to date, all teratogenic effects of known substances have been observed in animal studies. Clinical studies have not revealed any evidence of fetal malformations associated with metformin use (see the “Contraindications” section).
Risks associated with glibenclamide (see the “Preclinical Safety Data” section).
Animal studies have not revealed any teratogenic effects. In clinical practice, there are no relevant data on which to base an assessment of teratogenic or fetotoxic effects associated with the use of glibenclamide during pregnancy.
Treatment.
Adequate control of blood glucose levels contributes to a normal course of pregnancy in this patient population. Glibomet® should not be used to treat diabetes during pregnancy.
If a therapeutic diet is insufficient to fully compensate for metabolic disturbances, insulin therapy must be initiated regardless of the type of diabetes (type 1 or type 2 diabetes, gestational diabetes).
For gestational diabetes, it is recommended to switch from oral antidiabetic medications to insulin from the moment pregnancy is planned or immediately upon the onset of pregnancy and the use of this medication. Monitoring of blood glucose levels in the newborn is recommended.
Breastfeeding.
Since there is insufficient data on the transfer of metformin and glibenclamide into human breast milk, and due to the risk of hypoglycemia in the newborn, this medication is contraindicated during breastfeeding.
Effect on reaction time when driving or operating machinery
Patients should be informed of the symptoms of hypoglycemia. Special caution is required when driving or operating machinery due to the risk of developing symptoms of hypoglycemia.
Dosage and Administration
Dosage.
The dose is determined by the physician on a strictly individual basis for each patient and in accordance with laboratory test results (blood glucose, HbA1c).
Typically, the initial dose is 2 tablets per day, to be taken with meals. If necessary, the dose may be gradually increased until blood glucose levels are controlled. The dose of Glibomet® may then be gradually reduced to the minimum dose sufficient to maintain blood glucose control.
The maximum recommended daily dose of Glibomet® is 6 tablets.
Adults with normal renal function (GFR ≥ 90 mL/min).
Typically, the starting dose is 2 film-coated tablets per day. The treatment regimen depends on the individual daily dose, for example: • 1 film-coated tablet daily with breakfast, if the recommended daily dose is 1 tablet;
- 1–2 film-coated tablets twice daily, in the morning and in the evening, if the recommended daily dose is 2–4 tablets;
- 1–2 film-coated tablets three times a day—in the morning, afternoon, and evening—if the recommended daily dose is 3–6 tablets.
Renal insufficiency.
Before starting treatment and at least once a year after starting treatment with metformin-containing medications, the glomerular filtration rate (GFR) must be determined. In patients at increased risk of further worsening of renal insufficiency, as well as in elderly patients, renal function should be monitored more frequently, specifically every 3–6 months.
It is recommended to divide the maximum daily dose into 2–3 doses per day. Before starting treatment with Glibomet®, factors that may increase the risk of lactic acidosis (see the “Special Considerations for Use” section) should be evaluated in patients with an eGFR <60 mL/min.
If Glibomet® is not available, individual single-component medications should be used instead of the fixed-dose combination of active ingredients.
| GFR (mL/min) | Metformin
|
Glibenclamide |
| 60–89 | Maximum daily dose: 3,000 mg
Consider reducing the dose if renal function deteriorates. |
In cases of impaired renal function, accumulation of the drug may occur, resulting in an increased frequency of hypoglycemic episodes. |
| 45–59 | Maximum daily dose: 2,000 mg
The initial dose should not exceed half the maximum dose. |
|
| 30–44 | Maximum daily dose: 1,000 mg
The initial dose should not exceed half the maximum dose. |
|
| < 30 | Metformin is contraindicated |
For patients with an eGFR ≥ 60 and ≤ 89 mL/min, the daily dose of Glibomet® should not exceed the maximum dose, i.e., 6 film-coated tablets.
For patients with an eGFR of ≥ 45 and ≤ 59 mL/min, the maximum daily dose of Glibomet® should not exceed 5 film-coated tablets.
For patients with an eGFR of ≥ 30 and < 44 mL/min, the daily dose of Glibomet® should not exceed 2 film-coated tablets.
Glibomet® is contraindicated in patients with an eGFR < 30 mL/min.
Elderly patients.
In this patient group, the dose of Glibomet® depends on renal function (1 Glibomet® tablet at the start of therapy); renal function should be monitored regularly (see the “Special Considerations for Use” section).
Patients aged 65 years and older: The initial and maintenance doses of Glibomet® must be carefully adjusted to reduce the risk of hypoglycemia. Treatment should be initiated with the lowest possible dose and gradually increased as needed (see the “Special Considerations for Use” section).
Directions for Use.
Tablets should be swallowed whole with food, without chewing, and with sufficient liquid. To prevent hypoglycemia after taking the medication, it is recommended to eat a meal containing sufficient carbohydrates.
Combination therapy with insulin.
There are no clinical data on the use of this medication with insulin.
Children
This medication is contraindicated in children.
Overdose
Since this medication contains metformin, lactic acidosis may develop in the event of an overdose (see the “Special Considerations for Use” section).
If lactic acidosis develops, the patient should be hospitalized immediately and receive appropriate treatment. Hemodialysis is the most effective method for removing lactate and metformin from the body.
Since the drug contains sulfonylurea, an overdose may lead to hypoglycemia (see the “Special Considerations for Use” section) and gastrointestinal symptoms.
Plasma clearance of glibenclamide may be prolonged in patients with liver disease.
Due to its high protein binding, glibenclamide is not removed during hemodialysis.
Side Effects
The most common adverse reactions at the start of treatment are gastrointestinal symptoms, such as nausea, vomiting, diarrhea, abdominal pain, and loss of appetite. In most cases, these symptoms subside with continued treatment. As the dose is gradually increased, gastrointestinal tolerance of the drug improves.
Transient visual disturbances may occur at the start of treatment due to hypoglycemia.
Life-threatening or even fatal lactic acidosis may develop during metformin therapy, especially in patients with risk factors, including renal insufficiency and cardiogenic shock. In such severe cases, metformin treatment should be discontinued immediately and appropriate measures taken.
Elevated blood lactate levels, an increased lactate-to-pyruvate ratio, decreased blood pH, and hyperazotemia have been reported, all of which had an exclusively adverse course.
Alcohol consumption during treatment contributes to the development of lactic acidosis (see the “Special Considerations for Use” section).
Adverse reactions may occur during treatment with Glibomet®. The following classification is used to assess the frequency of adverse reactions:
very common >1/10; common >1/100, <1/10; uncommon >1/1,000, <1/100; rare >1/10,000, <1/1,000; very rare <1/10,000.
Blood and lymphatic system disorders.
Rare: leukopenia, thrombocytopenia.
Very rare: agranulocytosis, hemolytic anemia, bone marrow aplasia, pancytopenia, acute hemolysis in patients with glucose-6-phosphate dehydrogenase deficiency.
These reactions are reversible and resolve after discontinuation of treatment. Metabolism and nutrition.
Common: decreased vitamin B12 levels or deficiency (see the “Special Considerations for Use” section).
Occasional: acute hepatic porphyria, cutaneous porphyria.
Rare: hypoglycemia.
Very rare: lactic acidosis, decreased vitamin B12 levels due to reduced absorption. This etiology should be considered in patients with megaloblastic anemia.
Disulfiram-like reaction following alcohol consumption.
Ocular disorders.
Common: visual disturbances (temporary).
Nervous system disorders.
Common: headache, taste disturbances.
Gastrointestinal system.
Very common: nausea, vomiting, diarrhea, abdominal pain, loss of appetite. These side effects most often occur at the start of treatment and usually resolve on their own. To prevent gastrointestinal side effects, it is recommended to gradually increase the dosage and take Glibomet® 2–3 times a day.
Hepatobiliary system.
Very rare: hepatitis (treatment should be discontinued immediately); abnormal liver function test results.
Skin and subcutaneous tissue.
Cross-hypersensitivity to sulfonamides and their derivatives may develop.
Rare: pruritus, urticaria, maculopapular rash.
Very rare: allergic granulomatous angiitis, erythema multiforme, exfoliative dermatitis, photosensitivity reactions, urticaria, up to and including shock.
Additional diagnostic tests.
Occasionally: moderate to severe elevations in serum urea and creatinine levels.
Very rare: hyponatremia.
Elderly patients.
Symptoms of hypoglycemia may occur, especially in frail elderly patients, in cases of unusual physical exertion, irregular meals, or alcohol consumption, as well as in cases of impaired renal and/or hepatic function (see the “Special Considerations for Use” section).
Reporting of Suspected Adverse Reactions.
Reporting suspected adverse reactions after a drug’s approval plays an important role. This allows for continued monitoring of the benefit-risk profile of the drug. Healthcare professionals should report any suspected adverse reactions.
Shelf life
3 years.
Do not use this medication after the expiration date.
Storage Conditions
No special storage conditions are required. Keep out of reach of children.
Packaging
20 film-coated tablets in a blister pack; 2 or 5 blister packs in a cardboard box.
Manufacturer
Menarini-Von Heiden GmbH.
Manufacturer’s location and address of its place of business.
Leipziger Strasse 7–13, 01097 Dresden, Germany.
Applicant
Laboratori GIDOTTI S.p.A.
Applicant’s location.
Via Livornese 897, 56122 La Vettola (Pisa), Italy.