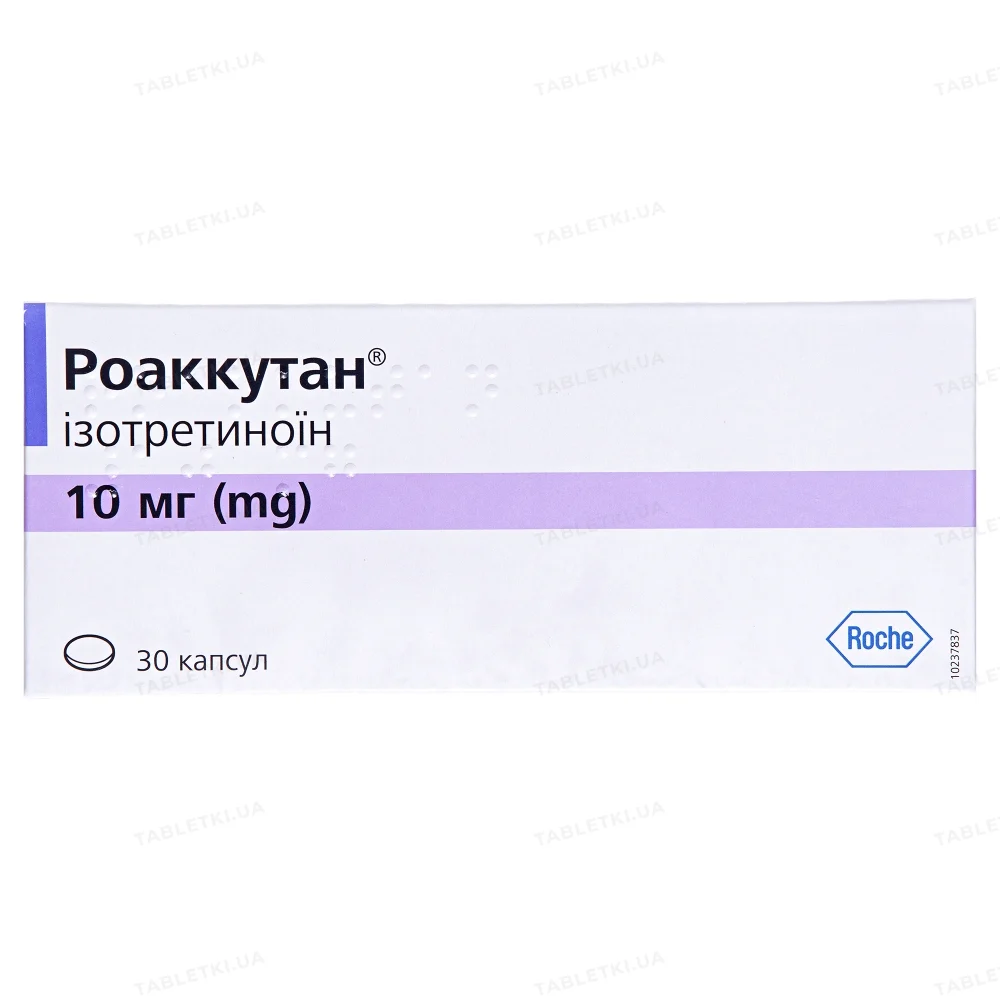

Roaccutane 10 mg capsules, No. 30 (10 x 3) 8594739239289
Composition
Active ingredient: isotretinoin;
1 capsule contains 10 mg or 20 mg of isotretinoin;
excipients: yellow beeswax, hydrogenated soybean oil, partially hydrogenated soybean oil, refined soybean oil;
capsule shell: gelatin, glycerin (85%), dry substance Carion 83 (sorbitol (E 420), mannitol (E 421), hydrolyzed hydrogenated starch), titanium dioxide (E 171), red iron oxide (E 172), printing ink.
Dosage Form
Capsules.
Main physical and chemical properties: 10 mg capsules: oval, opaque, brownish-red capsules, with a clear imprint of “ROA 10” on the surface; capsule length 8.3–10.7 mm, capsule diameter 5.3–7.7 mm; the capsule contents are a homogeneous, dark yellow suspension;
20 mg capsules: oval, opaque capsules; one half is brownish-red, the other half is white; the surface of the capsule bears a clear imprint of “ROA 20”; capsule length: 12.4–14.2 mm; capsule diameter: 7.3–9.1 mm; the capsule contents are a homogeneous, dark yellow suspension.
Pharmacotherapeutic group
Agents for the systemic treatment of acne.
ATC code D10B A01.
Pharmacological Properties
Pharmacodynamics.
Mechanism of action
Isotretinoin is a stereoisomer of all-trans-retinoic acid (tretinoin). The exact mechanism of action of isotretinoin has not yet been fully elucidated; however, it has been established that the improvement in the clinical presentation of severe forms of acne is associated with a reduction in sebaceous gland activity and a histologically confirmed decrease in their size. In addition, isotretinoin has been shown to have an anti-inflammatory effect on the skin.
Efficacy
Hyperkeratosis of the epithelial cells of the hair follicle and sebaceous gland leads to the desquamation of corneocytes within the gland duct and to its obstruction by keratin and excess sebum. This results in the formation of a comedone, and in some cases, an inflammatory process develops. Roaccutane® inhibits the proliferation of sebocytes and treats acne by restoring the normal process of cell differentiation. Sebum is the primary substrate for the growth of Propionibacterium acnes; reducing sebum production inhibits bacterial colonization of the duct.
Pharmacokinetics.
Absorption
The absorption of isotretinoin in the gastrointestinal tract is variable and linearly dependent on the dose within the therapeutic dosage range. The absolute bioavailability of isotretinoin has not been determined, as there is no formulation of the drug for intravenous administration; however, extrapolation of study results in dogs suggests very low and variable systemic bioavailability. Taking isotretinoin with food doubles its bioavailability compared to taking it on an empty stomach.
Distribution
Isotretinoin is almost completely bound to plasma proteins (99.9%), primarily to albumin. The volume of distribution of isotretinoin in the human body is unknown, as there is no formulation for intravenous administration. Isotretinoin concentrations in the epidermis are only half those in blood serum. Plasma concentrations of isotretinoin are approximately 1.7 times higher than those in whole blood due to poor penetration of isotretinoin into red blood cells.
Metabolism
Following oral administration, three major metabolites are observed in plasma: 4-oxo-isotretinoin, tretinoin (all-trans retinoic acid), and 4-oxo-retinoin. These metabolites have demonstrated biological activity in several in vitro assays. 4-oxo-isotretinoin, as shown in several clinical studies, accounts for a significant portion of isotretinoin’s therapeutic activity (inhibition of sebum secretion, regardless of plasma levels of isotretinoin and tretinoin). The major metabolite is 4-oxo-isotretinoin, whose steady-state plasma concentrations are 2.5 times higher than those of the parent drug. Other metabolites, including glucuronide conjugates, are minor.
Since isotretinoin and tretinoin (all-trans retinoic acid) are reversibly interconverted, the metabolism of tretinoin is linked to that of isotretinoin. It has been established that 20–30% of the isotretinoin dose is metabolized via isomerization.
Enterohepatic circulation may play a significant role in the pharmacokinetics of isotretinoin in humans.
In vitro metabolism studies have shown that several CYP enzymes are involved in the conversion of isotretinoin to 4-oxo-isotretinoin and tretinoin. Apparently, none of the isoforms plays a dominant role. Roaccutane® and its metabolites have no significant effect on the activity of CYP enzymes.
Excretion
After oral administration of radioactively labeled isotretinoin, approximately equal amounts are detected in urine and feces. The terminal-phase half-life of the unchanged drug following oral administration in patients with acne averages 19 hours. The terminal half-life of 4-oxo-isotretinoin is longer, averaging 29 hours.
Isotretinoin belongs to the group of natural (physiological) retinoids. Endogenous retinoid concentrations return to normal approximately 2 weeks after discontinuation of Roaccutane®.
Pharmacokinetics in Special Clinical Cases
Since isotretinoin is contraindicated in patients with impaired liver function, data on the pharmacokinetics of the drug in this patient population are limited.
Renal insufficiency does not significantly reduce the plasma clearance of isotretinoin and 4-oxo-isotretinoin.
Indications
Severe forms of acne (particularly nodular and conglobate acne, and acne prone to permanent scarring) that do not respond to standard treatments (systemic antibacterial therapy, topical treatment).
Before initiating treatment with isotretinoin in patients under 18 years of age, two independent prescribing physicians must agree that no other appropriate and effective treatment is available (see the “Children” section).
Contraindications
Pregnancy and breastfeeding; failure to comply with all conditions of the “Pregnancy Prevention Program” by women of childbearing age; hypersensitivity to isotretinoin or to any component of the drug; hepatic insufficiency; severe hyperlipidemia; hypervitaminosis A; concomitant therapy with tetracyclines. Because Roaccutane® contains refined soybean oil, partially hydrogenated soybean oil, and hydrogenated soybean oil, the drug is contraindicated in patients with an allergy to peanuts or soy.
Drug Interactions and Other Interactions
Due to the potential for exacerbation of hypervitaminosis A symptoms, concomitant administration of Roaccutane® and vitamin A should be avoided.
Cases of benign increased intracranial pressure (pseudotumor cerebri) have been reported with the concurrent use of isotretinoin and tetracyclines. Therefore, concomitant use with tetracyclines is contraindicated (see sections “Contraindications” and “Special Precautions for Use”).
Combined use with topical keratolytic or exfoliative agents for the treatment of acne should be avoided due to the potential for increased local irritation (see the “Special Precautions for Use” section).
Special Precautions for Use
Teratogenic Effects
Roaccutane® is a potent human teratogen and induces a high incidence of severe and life-threatening congenital malformations.
Roaccutane® is strictly contraindicated:
- pregnant women,
- women of childbearing age who do not comply with all the conditions of the “Pregnancy Prevention Program.”
“Pregnancy Prevention Program”
This medication is TERATOGENIC.
Roaccutane® is contraindicated in women of childbearing age, except in cases where all of the following conditions are met:
- the woman has been diagnosed with severe acne (nodular and conglobate acne, acne prone to permanent scarring) that does not respond to standard treatments (systemic antibiotic therapy, topical treatment) (see the “Indications” section);
- the potential for pregnancy should be assessed in all women;
- the woman understands the teratogenic risk of the drug;
- The woman understands the need for mandatory monthly follow-up visits with a physician;
- the woman understands and agrees to the need for effective contraception continuously for 1 month prior to the start of treatment, throughout the entire treatment period, and for one month after the end of treatment. At least one highly effective method of contraception (i.e., one that is not user-dependent) or two complementary user-dependent methods of contraception should be used simultaneously;
- When selecting a method of contraception in each specific case, individual circumstances should be evaluated. The patient should be involved in the discussion of the choice of contraceptive method to ensure her commitment and agreement to follow the rules for using the selected methods;
- even in the event of amenorrhea, a woman must use reliable methods of contraception;
- The woman has been informed of the risk of pregnancy during treatment with Roaccutane® and understands the need for immediate consultation if pregnancy is suspected or confirmed;
- The woman understands the necessity of and agrees to undergo regular pregnancy testing prior to treatment, ideally monthly during treatment, and 1 month after treatment is completed;
- the woman confirms that she is aware of the risks associated with isotretinoin and the need to take precautionary measures;
These conditions also apply to sexually inactive women, unless the physician is certain there is no risk of pregnancy.
The physician must be certain that:
- the patient is capable of understanding and complying with all of the above conditions for preventing pregnancy and has an adequate level of understanding;
- the patient confirms that she is familiar with the above conditions;
- the patient understands the need for consistent and correct use of either a single highly effective method of contraception (i.e., a user-independent method) or two complementary user-dependent methods of contraception simultaneously, for at least 1 month prior to the start of treatment, as well as the continued use of effective contraception throughout the entire treatment period and for at least 1 month after discontinuation of treatment;
- a negative result from a reliable pregnancy test prior to starting the medication, during treatment, and 1 month after the end of therapy. The dates and results of the pregnancy tests must be documented.
If a woman taking isotretinoin becomes pregnant, treatment with the drug should be discontinued, and the patient should be referred to a physician who specializes in or has experience in teratology for evaluation and guidance.
If pregnancy occurs after treatment has ended, there remains a risk of severe and serious congenital malformations in the fetus. This risk persists until the drug is completely eliminated from the body, which takes one month after the end of treatment.
Prevention of Pregnancy.
Patients must be informed about methods of contraception. If they are not using contraception, the physician must provide the necessary recommendations. If the treating physician is unable to provide this information, the patient should be referred to a physician with the appropriate specialty.
As a minimum requirement, women of reproductive age must use at least one highly effective method of contraception (i.e., one that is not user-dependent) or two complementary user-dependent methods of contraception simultaneously. Contraceptive methods should be used for at least 1 month prior to the start of treatment, throughout the entire treatment period, and for at least 1 month after discontinuation of Roaccutane®, even in patients with amenorrhea.
When selecting a method of contraception in each specific case, individual circumstances should be evaluated, and the patient should be invited to discuss the choice of contraceptive method to ensure her commitment and agreement to follow the guidelines for using the selected methods.
Pregnancy test.
In accordance with current practice, it is recommended to perform a pregnancy test under medical supervision, with a minimum sensitivity of 25 mMO/mL, as described below.
Before starting treatment
At least one month after the patient has started using contraception, and shortly (preferably a few days) before the first dose is administered, the patient should undergo a pregnancy test under medical supervision to ensure that she is not pregnant at the time of starting isotretinoin treatment.
During treatment
The patient should visit her doctor on a regular basis, ideally monthly. The need for monthly pregnancy testing under medical supervision is determined in accordance with local practice, taking into account the patient’s sexual activity, history of recent menstrual cycles (abnormal menstruation, irregular periods, or amenorrhea) and her method of contraception. If indicated, a pregnancy test is performed on the day of the scheduled visit or 3 days prior to the visit.
Completion of Treatment
A final pregnancy test is performed one month after the end of treatment.
For women of reproductive age, the duration of Roaccutane® treatment should ideally be limited to 30 days to ensure regular follow-up, including pregnancy tests and monitoring. It is recommended that the pregnancy test, prescription, and dispensing of Roaccutane® all take place on the same day. Roaccutane® should be dispensed at the pharmacy no later than 7 days after the prescription is written.
This monthly follow-up will ensure regular pregnancy testing and monitoring, as well as confirm that the patient is not pregnant before receiving the next course of treatment.
For patients who, in the opinion of the prescribing physician, have compelling reasons to indicate that there is no risk of pregnancy, after consistent use of isotretinoin without pregnancy (after the first 1–3 months), subsequent prescriptions may be issued for a treatment period exceeding 30 days (up to 12 weeks).
Male patients.
Available data indicate that in women, exposure to the drug from the semen and seminal fluid of men who have used Roaccutane® is insufficient to cause teratogenic effects.
Male patients should be reminded not to give the drug to others, especially women.
Additional Precautions
Microdoses of progesterone preparations may be an inadequate method of contraception during treatment with Roaccutane®.
Patients should never give this medication to others and should return any unused capsules to their doctor at the end of treatment.
Patients should not donate blood during treatment or for 1 month after treatment ends, as there is a risk of transfusion-related transmission to the fetus of a pregnant woman.
Mental Disorders
In patients receiving Roaccutane®, depression, worsening depression, anxiety, aggressive tendencies, mood swings, psychotic symptoms, suicidal thoughts, suicide attempts, and suicide have been reported (see the “Adverse Reactions” section).
Patients and, if appropriate, parents or caregivers should be advised of the risk of psychiatric disorders before prescribing isotretinoin and, preferably, beforereferral to an appropriate healthcare provider—which may include consideration of isotretinoin treatment—must be advised of the risk of developing psychiatric disorders.
Before starting treatment with isotretinoin, all patients should undergo a mental health assessment and be monitored regularly during treatment for the development or worsening of psychiatric disorders. In particular, caution is warranted in patients with a history of depression. If necessary, patients should be prescribed appropriate treatment for mental disorders. Discontinuation of Roaccutane® may not resolve the symptoms of mental disorders; in such cases, the patient requires further monitoring by specialists.
Awareness on the part of family or friends may be helpful in identifying mental health issues.
Sexual Dysfunction
The use of isotretinoin may be associated with sexual dysfunction (see the “Adverse Reactions” section). There have been reports of persistent sexual dysfunction, where symptoms did not resolve despite discontinuation of isotretinoin.
Patients and, if appropriate, their parents or guardians, should be advised of the risk of sexual dysfunction before a decision is made to prescribe the drug, and ideally before any referral to a healthcare provider that may involve consideration of isotretinoin treatment, must be counseled regarding the risk of sexual dysfunction associated with isotretinoin use. The patient’s age and sexual maturity should be taken into account when selecting the most appropriate approach to such counseling, including the possibility of discussing the matter without the presence of parents or guardians, if appropriate.
Before starting treatment with isotretinoin, all patients should be asked about symptoms of sexual dysfunction and monitored for the development of new sexual disorders during treatment.
Educational Materials
To help physicians, pharmacists, and patients avoid the risk of isotretinoin affecting the fetus, the marketing authorization holder provides educational materials designed to reinforce the warning regarding the teratogenic effects of isotretinoin, as well as recommendations on the use of contraception prior to starting therapy and the necessity of pregnancy testing.
Complete information on the teratogenic risk and strict measures for preventing pregnancy, as contained in the “Pregnancy Prevention Program,” must be provided by physicians to all patients, including both men and women of reproductive age (every woman who could become pregnant).
In addition, the educational material reinforces warnings regarding the risks associated with the use of isotretinoin, including potential risks to mental health and sexual function.
Skin and Subcutaneous Tissue Disorders
In rare cases, an exacerbation of acne may occur at the start of therapy; this usually resolves within 7–10 days without the need to adjust the dose.
Excessive exposure to sunlight or UV rays should be avoided. If sun protection is necessary, use sunscreen with an SPF of at least 15.
Deep chemical dermabrasion and laser treatment must not be performed during treatment with Roaccutane® or for 5–6 months after treatment, as there is a high risk of hypertrophic scarring in atypical areas and, less commonly, hyper- and hypopigmentation in the treated areas. During treatment with Roaccutane® and for 6 months after treatment, waxing should not be performed due to the risk of epidermal detachment.
Concomitant use of Roaccutane® with topical keratolytic or exfoliating agents for the treatment of acne should be avoided due to the potential for increased local irritation (see the section “Interactions with Other Medications and Other Types of Interactions”).
Patients receiving Roaccutane® are advised to use moisturizing ointments or body creams and lip balm to reduce dryness of the skin and lips at the start of treatment.
During the postmarketing period, cases of severe skin reactions (exudative erythema multiforme, Stevens–Johnson syndrome, toxic epidermal necrolysis) have been reported. Since these cases are difficult to distinguish from other possible skin reactions (see the “Adverse Reactions” section), patients should be warned about the symptoms of these conditions and closely monitored for severe skin reactions. If severe skin reactions are suspected, treatment with isotretinoin should be discontinued.
Allergic Reactions
Anaphylactic reactions have been rarely reported, in some cases following topical application of retinoids. Allergic skin reactions have been reported infrequently. Serious cases of allergic vasculitis of the extremities, often with purpura (bruises and red spots), as well as non-cutaneous manifestations, have been reported. Serious allergic reactions require discontinuation of therapy and careful monitoring of the patient’s condition.
Ocular Disorders
Dry eyes, corneal opacity, impaired night vision, and keratitis usually resolve after discontinuation of the drug. Cases of dry eyes that did not resolve after discontinuation of therapy have been reported. For dryness of the ocular mucosa, moisturizing eye ointment or artificial tears may be applied. If contact lenses are not tolerated, glasses should be worn during treatment.
Some patients may experience a decrease in twilight vision, which sometimes occurs suddenly (see the section “Ability to Affect Reaction Time When Driving or Operating Machinery”). If such patients report vision problems, they should be referred to an ophthalmologist, and discontinuation of the drug should be considered.
Musculoskeletal and Connective Tissue Disorders
In patients receiving isotretinoin, muscle and joint pain and elevated serum creatine phosphokinase levels have been reported, particularly during intense physical exertion (see the section “Adverse Reactions”). In some cases, this may progress to rhabdomyolysis, which is a potentially life-threatening condition.
Several years after treatment with Roaccutane® for the treatment of dyskeratoses at very high doses, skeletal changes developed, including premature closure of the epiphyseal growth plates, hyperostosis, and calcification of ligaments and tendons. The doses, duration of treatment, and total cumulative dose in these patients generally exceeded those recommended for the treatment of acne.
Cases of sacroiliitis have been reported in patients receiving isotretinoin. To differentiate sacroiliitis from other causes of back pain, patients with clinical manifestations of sacroiliitis may require additional evaluation, including imaging modalities such as MRI. In cases reported during the postmarketing period, sacroiliitis resolved after discontinuation of Roaccutane® and appropriate treatment.
Benign Intracranial Hypertension
Cases of benign intracranial hypertension have been reported; some of these were caused by concomitant use with tetracyclines (see the sections “Contraindications” and “Drug Interactions and Other Interactions”). Symptoms of benign intracranial hypertension include headache, nausea and vomiting, visual disturbances, and papilledema. Patients who develop benign intracranial hypertension should discontinue the drug immediately.
Hepatobiliary Disorders
It is recommended to monitor liver enzymes prior to treatment, 1 month after treatment initiation, and then every 3 months, unless there are clinical indications for more frequent monitoring. Temporary and reversible elevations in liver transaminase levels have been reported; in most cases, these elevations remained within the normal range and returned to baseline levels during treatment. If transaminase levels exceed normal limits, the dose should be reduced or the drug discontinued.
Renal Insufficiency
Impaired renal function or renal insufficiency does not affect the pharmacokinetics of isotretinoin. Therefore, isotretinoin may be administered to patients with renal insufficiency. However, it is recommended to start with a low dose and titrate it to the maximum tolerated dose (see the “Dosage and Administration” section).
Lipid Metabolism
Fasting serum lipid levels should be measured (prior to treatment, 1 month after initiation, and then every 3 months, unless there are clinical indications for more frequent monitoring). Elevated serum lipid levels usually normalize after reducing the dose or discontinuing the drug, as well as with dietary management. The use of isotretinoin is associated with increased triglyceride levels. Isotretinoin should be discontinued in cases of uncontrolled hyperlipidemia or if symptoms of pancreatitis occur. An increase in triglyceride levels above 800 mg/dL, or 9 mmol/L, may be accompanied by the development of acute pancreatitis, which may be fatal.
Gastrointestinal Disorders
Inflammatory bowel disease (including regional ileitis) may develop during treatment with isotretinoin. Patients with severe (hemorrhagic) diarrhea must discontinue the drug immediately.
High-Risk Groups
Patients with diabetes mellitus, obesity, alcoholism, or lipid metabolism disorders may require more frequent monitoring of serum glucose and/or lipid levels during treatment with isotretinoin. Elevated fasting blood glucose levels and new cases of diabetes mellitus have been reported during treatment with isotretinoin.
Excipients
This medication contains 2–3.05 mg of sorbitol (E 420) in each 10-mg capsule.
This medication contains 3.2–4.86 mg of sorbitol (E 420) in each 20-mg capsule.
The additive effect of concomitantly administered medications containing sorbitol (or fructose), as well as the intake of sorbitol (or lactose) with food, must be taken into account.
The sorbitol content in oral medications may affect the bioavailability of other oral medications when used concomitantly.
Use during pregnancy or breastfeeding.
Pregnancy
Pregnancy is an absolute contraindication for the use of Roaccutane® (see the “Contraindications” section). Women of childbearing age should use effective contraception during treatment and for one month after treatment. If, despite these precautions, pregnancy occurs while a woman is taking Roaccutane® or within one month after the end of therapy, there is a very high risk of severe and serious fetal malformations.
Fetal malformations associated with isotretinoin include central nervous system disorders (hydrocephalus, cerebellar malformations/anomalies, microcephaly), facial malformations, cleft lip, external ear anomalies (absence of the external ear, small or absent external auditory canal), eye malformations (microphthalmia), cardiac and vascular anomalies (conotruncal heart defects, such as tetralogy of Fallot, transposition of the great arteries, septal defects), and anomalies of the thymus and parathyroid glands. In addition, there is an increased risk of spontaneous miscarriage.
If a woman becomes pregnant while undergoing treatment with isotretinoin, therapy should be discontinued, and she should consult a physician who specializes in and has experience with teratology for an evaluation and consultation.
Breastfeeding.
Due to isotretinoin’s high lipophilicity, there is a high probability that it is excreted into breast milk. Due to the potential for adverse effects in the infant resulting from the drug’s transfer through breast milk, the use of Roaccutane® is contraindicated in women who are breastfeeding (see the “Contraindications” section).
Fertility
At therapeutic doses, isotretinoin does not affect sperm count, motility, or morphology and does not compromise embryonic formation or development in men taking isotretinoin.
Effect on reaction time when operating motor vehicles or other machinery.
Roaccutane® may potentially affect the ability to operate vehicles and other machinery.
During treatment and, rarely, afterward, some patients have experienced a decrease in twilight vision (see the “Adverse Reactions” and “Special Precautions for Use” sections). Since these symptoms occurred suddenly in some individuals, patients should be informed of the possibility of this problem and warned to exercise caution when driving or operating machinery.
Cases of drowsiness, dizziness, and visual disturbances have been reported very rarely. Patients should be warned that if these symptoms occur, they should not drive, operate machinery, or engage in activities that could endanger themselves or others.
Dosage and Administration
Standard Dosage Regimen.
Treatment with isotretinoin should be prescribed and administered only by a physician who has experience using systemic retinoids to treat severe acne and is fully aware of the risks of retinoid therapy and the requirements for monitoring patients’ condition.
Capsules should be taken with meals 1–2 times a day.
Adults (including adolescents and the elderly). Treatment should be initiated at a dose of 0.5 mg/kg per day. The therapeutic response to isotretinoin and certain adverse reactions are dose-dependent and vary among patients. Therefore, individual dose adjustments are necessary during treatment. In most patients, the dose ranges from 0.5 to 1 mg/kg of body weight per day.
Long-term remission and the frequency of relapse are more closely related to the total prescribed dose than to the duration of treatment or the daily dose. It has been shown that no additional benefit should be expected from a total dose exceeding 120–150 mg/kg. The duration of therapy depends on the daily dose. A treatment course of 16–24 weeks is usually sufficient to achieve remission.
In most patients, acne clears up completely after a single course of treatment. In cases of severe recurrence, a repeat course of Roaccutane® should be administered at the same daily and total doses as the first course. Since improvement may continue for up to 8 weeks after the end of treatment, a repeat course should not be prescribed until this period has elapsed.
Dosage in Special Cases.
Patients with renal impairment. In patients with severe renal impairment, treatment should be initiated at a lower dose (e.g., 10 mg/day), and then increased to 1 mg/kg/day or to the maximum tolerated dose (see the “Special Considerations for Use” section).
Patients with intolerance. For patients who experience severe intolerance to the recommended dose, treatment may be continued at a lower dose. In such cases, the duration of therapy will be longer, and the risk of relapse will be higher. To achieve the maximum possible efficacy, the highest tolerated dose should be used.
Children.
Roaccutane® should not be used to treat acne during the prepubertal period; the drug is not recommended for children under 12 years of age due to a lack of data on efficacy and safety.
Before initiating treatment with isotretinoin in patients under 18 years of age, two independent prescribing physicians must agree that no other appropriate and effective treatment is available (see the “Indications” section).
Overdose
Isotretinoin is a vitamin A derivative. Although the acute toxicity of isotretinoin is low, signs of hypervitaminosis A may occur in the event of an accidental overdose. Symptoms of acute vitamin A toxicity include severe headache, nausea or vomiting, drowsiness, irritability, and itching. Symptoms of accidental or intentional isotretinoin overdose are likely to be similar. These symptoms are reversible and resolve without the need for treatment.
Side Effects
Some side effects of isotretinoin are dose-dependent. Side effects are usually reversible after dose adjustment or discontinuation of the drug, but some may persist after treatment is stopped. The most commonly reported symptoms associated with isotretinoin use are dryness of the skin and mucous membranes, including the lips (cheilitis), the nasal cavity (nosebleeds), and the eyes (conjunctivitis).
The following categories are used to describe the frequency of adverse reactions: very common (≥ 1/10), common (≥ 1/100, < 1/10), uncommon (≥ 1/10,000, < 1/1,000), very rare (< 1/10,000), and frequency unknown (cannot be estimated from the available data). Within each frequency group and organ system class, adverse reactions are listed in order of decreasing severity.
Infections: very rare—Gram-positive bacterial infections of the skin and mucous membranes.
Blood and lymphatic system disorders: very common—anemia, elevated erythrocyte sedimentation rate (ESR), thrombocytopenia, thrombocytosis; common—neutropenia; very rare – lymphadenopathy.
Immune system disorders: rare—allergic skin reactions, anaphylactic reactions, hypersensitivity reactions.
Metabolic disorders: very rare—diabetes mellitus, hyperuricemia.
Psychiatric disorders: rare – tendency toward aggression, anxiety, mood changes; very rare – behavioral disorders, psychotic disorders; frequency unknown – depression, worsening of depression, suicide, suicide attempts, suicidal thoughts.
Nervous system disorders: common—headache; very rare—benign intracranial hypertension, seizures, drowsiness, dizziness.
Eye disorders: very common—blepharitis, conjunctivitis, dry eyes, eye irritation; very rare – blurred vision, cataracts, color vision abnormalities, contact lens intolerance, corneal opacity, decreased twilight vision, keratitis, optic disc edema (as a manifestation of benign intracranial hypertension), photophobia, visual disturbances.
Ear and labyrinth disorders: very rare—hearing impairment.
Vascular disorders: very rare—vasculitis (e.g., Wegener’s granulomatosis, allergic vasculitis).
Respiratory, thoracic, and mediastinal disorders: common—nosebleeds, nasal dryness, nasopharyngitis; very rare – bronchospasm (especially in patients with asthma), dysphonia.
Gastrointestinal disorders: very rare—colitis, ileitis, dry throat, gastrointestinal bleeding, hemorrhagic diarrhea, inflammatory bowel disease, nausea, pancreatitis. Cases of severe diarrhea have also been reported (see the “Special Precautions for Use” section).
Hepatobiliary disorders: very common—elevated transaminases (see the “Special Precautions for Use” section); very rare—hepatitis.
Skin and subcutaneous tissue disorders: very common—cheilitis, dermatitis, dry skin, localized scaling, pruritus, erythematous rash, skin trauma (risk of injury from friction); rare—alopecia; very rare—fulminant forms of acne, exacerbation of acne (acne-related erythema), erythema (face), exanthema, hair disorders, hirsutism, onychodystrophy, paronychia, photosensitivity, pyogenic granuloma, skin hyperpigmentation, increased sweating; frequency unknown—erythema multiforme, Stevens-Johnson syndrome, toxic epidermal necrolysis.
Musculoskeletal and connective tissue disorders: very common – arthralgia, myalgia, back pain (especially in children and adolescents); very rare – arthritis, calcinosis (calcification of ligaments and tendons), premature closure of epiphyseal growth plates, exostosis, hyperostosis, decreased bone density, tendinitis; frequency unknown – rhabdomyolysis, sacroiliitis.
Renal and urinary disorders: very rare—glomerulonephritis; frequency unknown—urethritis.
Reproductive system and breast disorders: frequency unknown – sexual dysfunction, including erectile dysfunction and decreased libido, gynecomastia, vulvovaginal dryness, orgasmic disorders, hypesthesia of the genital organs.
General disorders: very rare – tissue granulation (excessive formation), fatigue.
Laboratory parameters: very common—hypertriglyceridemia, decreased high-density lipoprotein levels; common—hypercholesterolemia, hyperglycemia, hematuria, proteinuria; very rare – elevated blood CPK levels.
Reporting adverse reactions after the drug’s approval is of great importance. This allows for monitoring the benefit-risk ratio when using this drug. Healthcare and pharmaceutical professionals, as well as patients or their legal representatives, should report all cases of suspected adverse reactions and lack of efficacy of the drug through the automated pharmacovigilance information system at the following link: https://aisf.dec.gov.ua.
Shelf life
3 years.
Storage conditions
Keep out of reach of children.
Store at a temperature not exceeding 25 °C in the original packaging to protect from moisture and light.
Packaging
10 capsules of 10 mg or 20 mg in blisters made of PVC/PE/PVDC/aluminum foil or PVC/PVDC/aluminum foil. 3 blisters per cardboard box.
Manufacturer
F. Hoffmann-La Roche Ltd.
Address
Wurmisweg, 4303 Kaiseraugst, Switzerland
Grenzacherstrasse 124, 4058 Basel, Switzerland