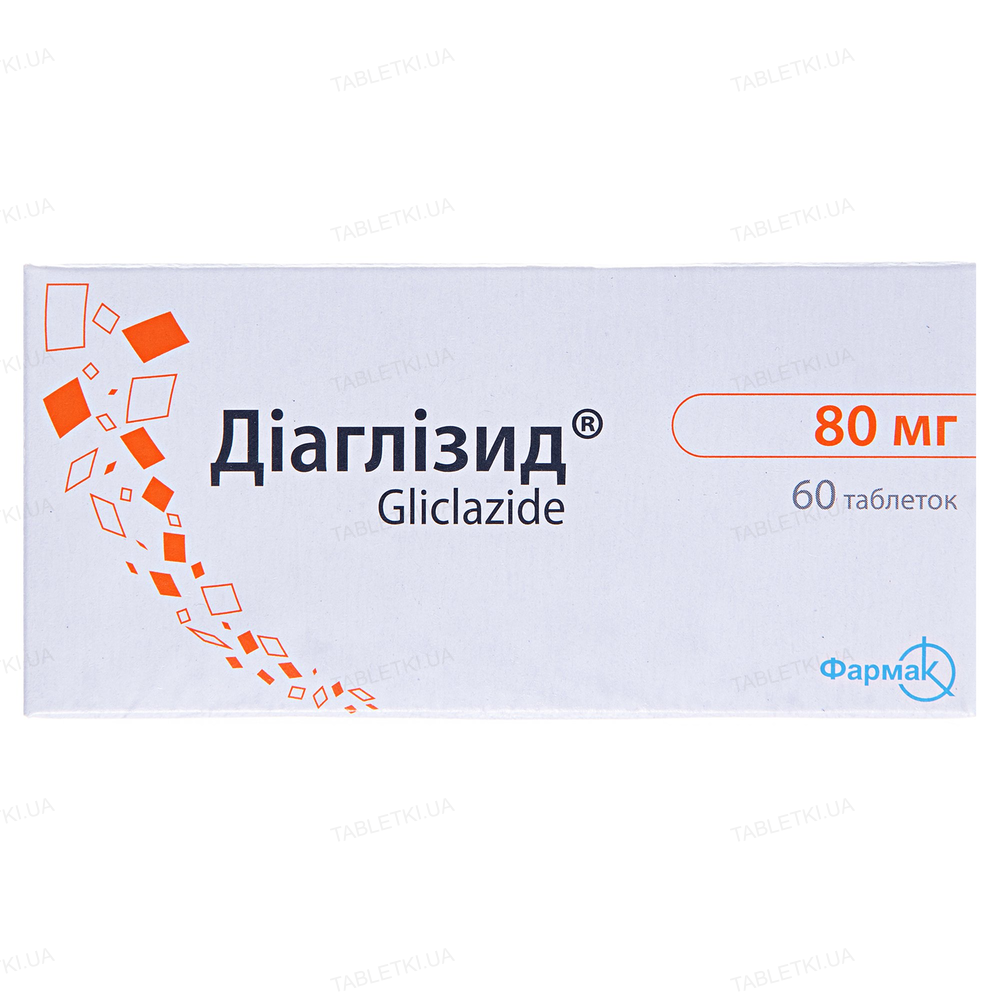

Diaglizid 80 mg tablets, No. 60 (10 x 6)
1 tablet contains 80 mg of gliclazide, calculated as 100% active ingredient;
Inactive ingredients: lactose monohydrate, microcrystalline cellulose, povidone, calcium stearate, talc.
Dosage Form
Tablets.
Main physical and chemical properties: white or white tablets with a cream tint, featuring a flat surface, a score line, and a bevel.
Pharmacotherapeutic group
Antidiabetic agents, excluding insulins. Sulfonylureas, urea derivatives. Gliclazide. ATC code A10B B09.
Pharmacological properties
Pharmacodynamics.
Gliclazide is a sulfonylurea derivative and belongs to the second generation of synthetic oral hypoglycemic agents. The drug restores the early peak of insulin secretion and affects calcium transport in pancreatic β-cells. A distinctive feature of the chemical structure of second-generation drugs accounts for their greater affinity for the sulfonylurea receptor on the β-cell membrane. This action occurs via the following mechanism: a decrease in the permeability of the β-cell membrane to potassium ions ®, depolarization of the membrane, the influx of calcium ions through channels whose opening depends on changes in the membrane’s electrical potential, an increase in intracellular calcium concentration, and the release of insulin from cytoplasmic granules. Gliclazide selectively, with high affinity, and reversibly binds to the regulatory subunit of the calcium-dependent translocation protein (CATP) in the pancreatic β-cells. Gliclazide enhances the effectiveness of insulin and reduces insulin resistance by increasing glucose utilization and storage in muscles and decreasing its synthesis in the liver. The drug enhances insulin-stimulated glucose metabolism by accelerating its transport to tissues and by activating muscle glycogen synthase. The hypoglycemic effect of gliclazide stimulates the secretion of endogenous insulin. The hypoglycemic effect is mild.
Gliclazide prevents the development of diabetic vascular complications, including microangiopathy and atheromatous macroangiopathy. This effect is achieved by reducing platelet adhesion and aggregation, normalizing prostaglandin metabolism (the balance of which is disrupted in diabetes), and increasing the fibrinolytic activity of blood vessels. In addition, the drug is a potent inhibitor of free radicals (the production of which is significantly increased in diabetes), normalizes vascular permeability, and prevents the development of microthrombosis and atherogenesis. Gliclazide reduces the severity of oxidative stress. Gliclazide reduces lipid deposition leading to the formation of atherosclerotic plaques. The drug promotes weight loss and normalizes lipid metabolism (reduces the concentration of cholesterol, triglycerides, and free fatty acids in blood plasma).
Pharmacokinetics.
Gliclazide is rapidly absorbed in the gastrointestinal tract. Food intake and meal composition do not affect the rate or extent of its absorption. After oral administration of 80 mg of gliclazide to patients with non-insulin-dependent diabetes mellitus who had been receiving this drug at the same dose for one week, a maximum plasma concentration of 6–8 μg/mL was reached within 2–3 hours. In a healthy person, the maximum plasma concentration—2–4 μg/mL—is reached 4 hours after a single 80-mg dose. 87–95% of gliclazide is bound to plasma proteins. The drug is almost completely metabolized, primarily in the liver. The half-life of gliclazide in the body ranges from 10 to 12 hours. Three to six hours after administration, its metabolites are detected in the intestines. Plasma clearance is approximately 13 mL/min; 60–70% of the drug is excreted in the urine, and 10–20% in the feces.
Indications
Type 2 diabetes mellitus (non-insulin-dependent) in adults when blood glucose levels cannot be controlled by diet, exercise, or weight loss alone.
Contraindications
- Hypersensitivity to gliclazide, other sulfonylurea derivatives, or to any of the drug’s inactive ingredients;
- Type 1 diabetes (insulin-dependent);
- severe ketoacidosis, precoma, and diabetic coma;
- severe renal insufficiency;
- severe hepatic insufficiency;
- treatment with miconazole;
- treatment with quinolones;
- breastfeeding.
Drug Interactions and Other Interactions
When using medications that may cause hypo- or hyperglycemia, the patient should be advised to carefully monitor blood glucose levels during treatment. Dosage adjustment of the hypoglycemic medication may be required during and after treatment with these medications.
Medications that may increase the risk of hypoglycemia:
Concomitant use is contraindicated.
Miconazole (for systemic use, oral gel) potentiates the hypoglycemic effect, potentially leading to the development of hypoglycemia symptoms and even coma.
Quinolones enhance the hypoglycemic effect, potentially leading to severe, profound, and persistent hypoglycemia—whose symptoms are difficult to control—or even coma, especially in elderly patients with renal insufficiency.
Concomitant use is not recommended.
Phenylbutazone (for systemic use) enhances the hypoglycemic effect of sulfonylureas (by displacing their binding to plasma proteins and/or reducing their excretion). It is recommended to use other nonsteroidal anti-inflammatory drugs (NSAIDs) or to advise the patient and emphasize the importance of self-monitoring blood glucose levels. If necessary, the dose of the hypoglycemic agent may be adjusted during and after treatment with phenylbutazone.
Alcohol increases the risk of hypoglycemic reactions (due to suppression of compensatory responses), which may lead to hypoglycemic coma. Alcohol and alcohol-containing medications should be avoided.
Combinations Requiring Caution.
Concomitant use with any of the following medications may cause hypoglycemia in some cases due to an enhanced hypoglycemic effect: other hypoglycemic agents (insulin, acarbose, biguanides, metformin, thiazolidinediones, dipeptidyl peptidase-4 inhibitors, glucagon-like peptide-1 (GLP-1) receptor agonists)), β-blockers, fluconazole, ACE inhibitors (captopril, enalapril), H₂ receptor antagonists, MAO inhibitors, sulfonylureas, nonsteroidal anti-inflammatory drugs, clarithromycin.
Medications that may increase the risk of hyperglycemia:
Concomitant use is not recommended.
Danazol has a diabetogenic effect. If use of this drug cannot be avoided, the patient must be warned and the importance of self-monitoring blood and urine glucose levels must be emphasized. If necessary, the dose of the hypoglycemic medication may be adjusted during and after treatment with danazol.
Combinations Requiring Caution.
Chlorpromazine (a neuroleptic) in high doses (over 100 mg per day) increases blood glucose levels (by reducing insulin release). Patients should be warned and the importance of self-monitoring blood glucose levels should be emphasized. If necessary, the dose of the hypoglycemic agent may be adjusted during and after treatment with the neuroleptic.
Glucocorticoids (for systemic and topical use: intra-articular, topical, and rectal formulations) and tetracosactide—raise blood glucose levels and may lead to the development of ketoacidosis (they reduce carbohydrate tolerance). Patients should be warned and the importance of self-monitoring blood glucose levels should be emphasized, especially at the start of treatment. If necessary, the dose of the hypoglycemic medication may be adjusted during and after treatment with glucocorticoids.
Ritodrine, salbutamol, and terbutaline (intravenous) may increase blood glucose levels due to the effects of β2-agonists.
St. John’s wort (Hypericum perforatum) preparations reduce the concentration of gliclazide. The importance of monitoring blood glucose levels should be emphasized.
Combinations to Consider.
Anticoagulants (e.g., warfarin): When used concomitantly with anticoagulants, sulfonylurea derivatives may potentiate the anticoagulant effect of the latter. If necessary, the dose of anticoagulants may be adjusted.
Special Considerations
Hypoglycemia. This medication should only be prescribed if the patient can maintain a regular diet (including breakfast). Regular carbohydrate intake is very important. Delays in eating, insufficient food intake, or low carbohydrate intake increase the risk of hypoglycemia.
Hypoglycemia is more likely to occur with a low-calorie or irregular diet, prolonged or intense physical activity, alcohol consumption, or concomitant use of other hypoglycemic medications.
Hypoglycemia may occur when taking sulfonylureas. In some cases, hypoglycemia can be severe and prolonged. In such cases, hospitalization and administration of glucose for several days may be required.
To reduce the risk of hypoglycemic episodes, it is necessary to take into account the individual characteristics of patients, provide them with clear instructions, and carefully adjust the dose.
Risk factors that increase the likelihood of hypoglycemia include:
- the patient refuses or is unable to follow the doctor’s recommendations (this is especially true for older patients);
- poor or irregular nutrition, periods of fasting, and changes in diet;
- an imbalance between physical activity and carbohydrate intake;
- alcohol consumption;
- renal failure;
- severe liver failure;
- drug overdose;
- certain endocrine disorders: thyroid dysfunction, hypopituitarism, and adrenal insufficiency;
- concomitant use of certain medications (see the “Drug Interactions” section).
Renal and hepatic insufficiency: The pharmacokinetics and/or pharmacodynamics of gliclazide may differ in patients with hepatic or severe renal insufficiency. Episodes of hypoglycemia in such patients may be prolonged and therefore require appropriate treatment.
Patient Information. The patient and their family members should be informed about the risk factors and conditions that may contribute to hypoglycemia, the symptoms of hypoglycemia, and how to manage them. The patient should be informed of the importance of following the doctor’s dietary recommendations, engaging in regular physical activity, and monitoring blood glucose levels regularly.
Worsening glycemic control in patients receiving hypoglycemic medications may be caused by: St. John’s wort (Hypericum perforatum) preparations or any concomitant treatment that may affect the metabolism of gliclazide, infection, fever, trauma, or surgery. In some cases, insulin may be required. The hypoglycemic efficacy of any oral hypoglycemic agent, including gliclazide, may change over time. This may be due to the progression of the disease or a reduced response to treatment. This phenomenon is known as secondary failure, which differs from primary failure, where medications are ineffective from the very start of treatment. Before concluding that a patient has developed secondary failure, it is necessary to verify that the prescribed dose is correct and that the patient is adhering to their diet.
Abnormalities in blood glucose levels, including hypo- and hyperglycemia, have been observed in patients with diabetes, particularly the elderly, receiving concomitant treatment with fluoroquinolones. Careful monitoring of blood glucose levels is recommended for all patients receiving concomitant treatment with Diaglizid® and fluoroquinolones.
Laboratory parameters: To assess blood glucose control, measurement of glycated hemoglobin (or fasting blood glucose) is recommended.
In patients with glucose-6-phosphate dehydrogenase deficiency, the use of sulfonylureas may cause hemolytic anemia. Gliclazide should be prescribed with caution in these patients, and alternative treatments should be considered.
This medication contains lactose; therefore, it is not recommended for patients with congenital galactose intolerance, glucose-galactose malabsorption syndrome, or Lapp lactase deficiency.
Pregnancy and lactation.
Pregnancy. Oral hypoglycemic agents (including Diaglizid) should not be used during pregnancy. Experience with gliclazide during pregnancy is limited (fewer than 300 cases in pregnant women), and data on the use of other sulfonylurea drugs are limited. Animal studies have shown that gliclazide® has no teratogenic effects.
It is advisable to avoid taking gliclazide during pregnancy.
Glucose control should be achieved before planning a pregnancy to reduce the risk of complications associated with uncontrolled diabetes. When planning a pregnancy or immediately after confirmation of pregnancy, the woman should be switched from oral hypoglycemic agents to insulin.
Breastfeeding. There are no data on the excretion of gliclazide or its metabolites into breast milk. Diaglizid® is contraindicated during breastfeeding due to the potential for neonatal hypoglycemia. A risk to newborns and infants cannot be ruled out.
Fertility. Preclinical studies did not reveal any effects on fertility or reproductive performance in female and male rats
Effects on the ability to operate vehicles and machinery.
Diaglizid® may have a minor effect on the ability to drive a car or operate other automated systems.
Patients should be aware of the symptoms of hypoglycemia, be able to recognize them, and refrain from driving or operating machinery if they occur.
Dosage and Administration
Administer orally to adults.
Like all hypoglycemic agents, Diaglizid® requires individual dose adjustment based on the patient’s individual response to treatment. For patients whose glucose levels are usually well controlled by diet, Diaglizid® may be prescribed for a short period in the event of a temporary loss of glucose control.
Initial dose: For patients under 65 years of age, 1 tablet (80 mg of gliclazide) per day.
Patients over 65 years of age should start with 40 mg of the drug once daily (use gliclazide preparations that allow for this dosage).
It is recommended to increase the dose at intervals of at least 14 days, with careful monitoring of blood glucose levels.
The average daily dose is 1–3 tablets of Diaglizid® (80 mg tablets) taken in two divided doses.
The standard dose is 2 tablets per day, taken in two divided doses.
The maximum daily dose is 4 tablets of the drug in two doses.
Other high-risk patients.
For patients with inadequate or irregular nutrition, or with a significantly impaired general condition, as well as patients with renal or hepatic insufficiency, treatment should be initiated at the minimum dose, and recommendations for dose escalation should be strictly followed to avoid the possibility of hypoglycemic reactions.
Patients receiving other oral hypoglycemic agents:
As with other medications for the treatment of diabetes, this medication may be prescribed in place of another hypoglycemic agent without any transition period. When switching from another sulfonylurea with a longer half-life (e.g., chlorpropamide) to this drug, the patient should be closely monitored (for several weeks) to avoid an additive effect of the two drugs and the development of hypoglycemia.
Children. The safety and efficacy of Diaglizid® in children have not been studied; therefore, the drug should not be used in this patient population.
Overdose
An overdose of sulfonylureas may cause hypoglycemia.
Symptoms of mild hypoglycemia (without loss of consciousness or neurological symptoms) should be corrected by consuming carbohydrates (sugar), adjusting the dose of the hypoglycemic medication, and/or modifying the diet. Close monitoring of the patient should continue until the physician is confident of the patient’s safety.
Severe hypoglycemia with coma, seizures, or other neurological disorders requires emergency medical care with immediate hospitalization.
If hypoglycemic coma is diagnosed or suspected, the patient should be given 50 mL of concentrated glucose (20–30%) intravenously as soon as possible, followed by a continuous infusion of a less concentrated glucose solution (10%) at a rate that will maintain blood glucose levels above 1 g/L. Depending on the patient’s condition, the physician decides on the further course of action.
Gliclazide has a high plasma protein binding rate, so dialysis is not very effective.
Side Effects
Based on experience with gliclazide and other sulfonylurea derivatives, the following adverse effects may occur.
Hypoglycemia. As with other sulfonylurea drugs, gliclazide can cause hypoglycemia if meals are taken irregularly, and especially if a meal is skipped. The onset of hypoglycemia may be accompanied by characteristic symptoms, namely: headache, intense hunger, nausea, vomiting, fatigue, sleep disturbances, agitation, aggression, impaired concentration and reaction time, depression, confusion, visual and speech disturbances, aphasia, tremor, paresis, sensory disturbances, dizziness, a feeling of weakness, loss of self-control, delirium, seizures, shallow breathing, bradycardia, drowsiness, and loss of consciousness, which can lead to coma and death.
In addition, signs of adrenergic counterregulation may occur, such as increased sweating, clammy skin, anxiety, tachycardia, hypertension, palpitations, angina attacks, and arrhythmia.
Symptoms of hypoglycemia usually resolve after the intake of carbohydrates (sugar). However, sweeteners are not very effective. Experience with other sulfonylurea drugs indicates that hypoglycemia may recur even if the initial treatment measures were effective.
If an episode of hypoglycemia is severe or prolonged, the patient requires emergency medical care or hospitalization, even if blood sugar levels are temporarily under control.
Other adverse effects.
Gastrointestinal disorders: abdominal pain, nausea, vomiting, dyspepsia, diarrhea, and constipation. Following the recommendation to take the medication with breakfast will help prevent or minimize the occurrence of these symptoms.
The following side effects are observed less frequently.
Skin and subcutaneous tissue disorders: rash, itching, hives, erythema, macropapular rash, bullous rash, Stevens-Johnson syndrome, toxic epidermal necrolysis, angioedema; in rare cases, drug rash with eosinophilia and systemic symptoms (DRESS).
Blood and lymphatic system disorders (rare): anemia, thrombocytopenia, leukopenia, granulocytopenia. These effects usually resolve after discontinuation of treatment.
Hepatobiliary system: elevated liver enzyme levels (ALT, AST, alkaline phosphatase), hepatitis (isolated cases). If jaundice occurs, treatment with the drug should be discontinued.
These adverse effects usually resolve after discontinuation of the drug.
Ocular: Temporary visual disturbances may occur, especially at the start of treatment, due to changes in blood glucose levels.
Metabolic disorders: hyponatremia.
Abnormalities that may occur with any sulfonylurea include erythrocytopenia, agranulocytosis, hemolytic anemia, pancytopenia, and allergic vasculitis. Cases of elevated liver enzyme levels and even liver dysfunction (e.g., cholestasis and jaundice) and hepatitis have also been reported with sulfonylureas. Life-threatening failure.
Shelf life
3 years.
Do not use the medication after the expiration date printed on the package.
Storage conditions
Store at a temperature not exceeding 25 °C. Keep out of the reach of children.
Packaging
10 tablets per blister pack. 3 or 6 blister packs per package.
Manufacturer
Farmak JSC.
Address
74 Kirillovskaya St., Kyiv, 04080, Ukraine.