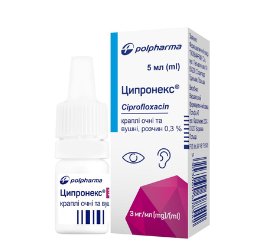






Cipronex Eye/Ear Drops, 0.3% solution, 5 mL per dropper bottle
Ingredients
Active ingredient: ciprofloxacin;
1 mL of solution contains 3 mg of ciprofloxacin as 3.5 mg of ciprofloxacin hydrochloride monohydrate;
Excipients: mannitol (E 421); sodium acetate trihydrate; glacial acetic acid; disodium edetate; benzalkonium chloride solution; purified water.
Dosage Form
Eye and ear drops, solution.
Main physical and chemical properties: an almost colorless, light yellow or light green, clear liquid.
Pharmacotherapeutic group
Agents for use in ophthalmology and otology. Antimicrobial agents. ATC code S0ZA A07.
Pharmacological properties
Pharmacodynamics.
Mechanism of action
Cipronex® contains ciprofloxacin hydrochloride, which belongs to the quinolone class. The bactericidal action of quinolones, which primarily affects bacterial DNA synthesis, is mediated by the inhibition of DNA gyrase.
Ciprofloxacin exhibits high in vitro activity against most Gram-negative microorganisms, including Pseudomonas aeruginosa. It is also effective against aerobic Gram-positive microorganisms, such as staphylococci and streptococci.
Susceptibility of microorganisms
Ophthalmic use
Both in vitro studies and clinical use in ocular infections have demonstrated that ciprofloxacin is active against most strains of the following organisms.
Aerobic Gram-positive microorganisms:
Staphylococcus aureus (including both methicillin-susceptible and methicillin-resistant strains);
Staphylococcus epidermidis;
Staphylococcus spp., other coagulase-negative species of Staphylococcus spp., including S. haemolyticus and S. hominis;
Corynebacterium spp.;
Streptococcus pneumoniae;
Viridans group Streptococcus.
Aerobic Gram-negative microorganisms:
Acinetobacter spp.;
Haemophilus influenzae;
Pseudomonas aeruginosa;
Moraxella spp. (including M. catarrhalis)
Use in otology
Ciprofloxacin exhibits high in vitro activity against most aerobic Gram-negative microorganisms, including Pseudomonas aeruginosa. It is also effective against aerobic Gram-positive microorganisms, such as staphylococci and streptococci. As shown in Table 1, ciprofloxacin exhibits a broad spectrum of activity in vivo (MIC90S ≤ 2 μg/mL) against pathogenic microorganisms isolated from patients with acute otitis externa.
Table 1
|
Bacterial species
|
Isolates
N=
|
Min. MIC
(μg/mL)
|
MIC50
(μg/mL)
|
MIC90
(μg/mL)
|
MICmax
(μg/mL)
|
|
Pseudomonas aeruginosa
|
1089
|
0.03
|
0.13
|
0.25
|
16
|
|
Staphylococcus aureus
|
221
|
0.13
|
0.50
|
1.0
|
128
|
|
Staphylococcus epidermidis
|
257
|
0.06
|
0.25
|
0.50
|
128
|
|
Staphylococcus caprae
|
75
|
0.13
|
0.50
|
0.50
|
2.0
|
|
Enterococcus faecalis
|
53
|
0.50
|
1.0
|
2.0
|
4.0
|
|
Enterobacter cloacae
|
45
|
0.004
|
0.016
|
0.032
|
0.25
|
Ciprofloxacin is also active against pathogenic microorganisms isolated from patients with acute otitis media who have tympanostomy tubes.
Table 2
|
Bacterial species
|
Isolates
N=
|
Min. MIC
(μg/mL)
|
MIC50
(μg/mL)
|
MIC90
(μg/mL)
|
MICmax
(μg/mL)
|
|
Streptococcus pneumoniae
|
197
|
0.25
|
1.0
|
2.0
|
8.0
|
|
Staphylococcus aureus
|
134
|
0.06
|
0.25
|
1.0
|
>128
|
|
Pseudomonas aeruginosa
|
132
|
0.03
|
0.25
|
0.50
|
128
|
|
Haemophilus influenzae
|
122
|
0.004
|
0.008
|
0.016
|
0.25
|
|
Staphylococcus epidermidis
|
103
|
0.06
|
1.0
|
64
|
64
|
|
Moraxella catarrhalis
|
37
|
0.008
|
0.03
|
0.06
|
0.06
|
|
Escherichia coli
|
15
|
0.008
|
0.03
|
128
|
>128
|
Threshold values for the diameters of zones of microbial growth inhibition
Ophthalmic use
Ciprofloxacin has been shown to be active in vitro against most strains of the microorganisms listed below; however, the clinical significance of these data in ophthalmic infections is unknown. The safety and efficacy of ciprofloxacin in the treatment of corneal ulcers or conjunctivitis caused by these microorganisms have not been established in adequate and well-controlled clinical studies.
The bacteria listed below are considered susceptible when evaluated using standard cut-off values for the diameters of zones of microbial growth inhibition. However, a correlation between systemic in vitro minimum inhibitory diameter values and ophthalmic efficacy has not been established. Ciprofloxacin demonstrates minimum inhibitory concentrations (MIC) of 1 μg/mL or less in vitro (systemic breakpoints for zones of inhibition) against the majority (90%) of strains of the following ocular pathogenic microorganisms.
Aerobic Gram-positive microorganisms:
Bacillus species.
Aerobic Gram-negative microorganisms:
Acinetobacter calcoaceticus;
Enterobacter aerogenes;
Escherichia coli;
Haemophilus parainfluenzae;
Klebsiella pneumoniae;
Neisseria gonorrhoeae;
Proteus mirabilis;
Proteus vulgaris;
Serratia marcescens.
Other
Peptococcus spp., Peptostreptococcus spp., Propionibacterium acnes, and Clostridium perfringens are susceptible microorganisms.
Resistant
Some strains of Burkholderia cepacia and Stenotrophomonas maltophilia are resistant to ciprofloxacin, as are some anaerobic bacteria, particularly Bacteroides fragilis.
Additional Information
The minimum bactericidal concentration (MBC) does not usually exceed the MIC by more than a factor of 2.
Use in Otology
Ciprofloxacin has been shown to be active in vitro against most strains of the microorganisms listed below; however, the clinical significance of these data in ear infections is unknown. The safety and efficacy of ciprofloxacin in the treatment of acute otitis externa caused by these microorganisms have not been established in adequate and well-controlled clinical studies.
The bacteria listed below are considered susceptible when evaluated using systemic cut-off values for the diameters of zones of microbial growth inhibition. However, a correlation between in vitro minimum inhibitory diameter values and efficacy when administered to the ear has not been established. Ciprofloxacin demonstrates an in vitro MIC of 1 μg/mL or less (systemic breakpoint values for zones of microbial growth inhibition) against the majority (90%) of strains of the following pathogenic microorganisms.
Aerobic Gram-positive microorganisms:
Bacillus species;
Corynebacterium species;
Enterococcus faecalis;
Staphylococcus aureus;
Staphylococcus epidermidis;
Staphylococcus caprae;
Staphylococcus capitis;
Staphylococcus haemolyticus;
Streptococcus pneumoniae;
Viridans group Streptococcus.
Aerobic Gram-negative microorganisms:
Achromobacter xylosoxidans subsp. xylosoxidans;
Acinetobacter baumannii;
Acinetobacter junii;
Acinetobacter Iwoffi;
Acinetobacter radioresistans;
Acinetobacter genotype 3;
Citrobacter freundii;
Citrobacter koseri;
Enterobacter aerogenes;
Enterobacter cloacae;
Escherichia coli;
Haemophilus influenzae;
Klebsiella oxytoca;
Klebsiella pneumoniae;
Moraxella catarrhalis;
Proteus mirabilis;
Pseudomonas stutzeri;
Serratia marcescens.
Ciprofloxacin has also been shown to be active in vitro against most strains of the following microorganisms that cause otitis media.
Aerobic Gram-positive microorganisms:
Staphylococcus aureus;
Staphylococcus epidermidis;
Streptococcus pneumoniae.
Aerobic Gram-negative microorganisms:
Escherichia coli;
Haemophilus influenzae;
Moraxella catarrhalis;
Pseudomonas aeruginosa.
Resistance to ciprofloxacin usually develops slowly. However, cross-resistance is observed within this group of gyrase inhibitors.
Bacterial susceptibility testing has shown that most microorganisms resistant to ciprofloxacin are also resistant to other fluoroquinolones. The frequency of isolation of strains with acquired resistance to ciprofloxacin was low.
Due to its unique mechanism of action, there is no cross-resistance between ciprofloxacin and other antibacterial agents with different chemical structures, such as beta-lactam antibiotics, aminoglycosides, tetracyclines, macrolides, and peptides, as well as sulfonamides, trimethoprim derivatives, and nitrofuran derivatives. Thus, microorganisms resistant to these drugs may be susceptible to ciprofloxacin.
Pharmacokinetics.
After topical application to the human eye, ciprofloxacin is well absorbed. The concentration of ciprofloxacin detected in the tear film, cornea, and anterior chamber of the eye is 10 to several hundred times higher than the MIC90 for susceptible ocular pathogens.
Systemic absorption of ciprofloxacin following topical application to the eye is low. Plasma ciprofloxacin levels after 7 days of topical application ranged from undetectable levels (<1.25 ng/mL) to 4.7 ng/mL. The mean maximum plasma concentration of ciprofloxacin obtained after topical application to the eye was approximately 450 times lower than that observed following oral administration of a single 250-mg dose of ciprofloxacin.
In children with otorrhea using a tympanostomy tube or with a perforated eardrum, topical application of ciprofloxacin to the ear resulted in plasma ciprofloxacin concentrations which were not quantifiable, with a limit of detection of 5 ng/mL. In animals, ciprofloxacin was distributed in plasma and middle ear fluid following intramuscular injection and was absorbed into the inner ear following topical application to the middle ear.
The systemic pharmacokinetic properties of ciprofloxacin are well established.
Ciprofloxacin is well distributed throughout body tissues, with tissue concentrations typically higher than plasma concentrations. The volume of distribution at steady state is 1.7–2.71 L/kg. Serum protein binding is 16–43%. The half-life of ciprofloxacin in serum is 3–5 hours. After oral administration of a single dose of 250 to 750 mg in adult patients with normal renal function, 15–50% of the dose is excreted in the urine as unchanged drug and 10–15% as metabolites within 24 hours. Both ciprofloxacin and its four primary metabolites are excreted in the urine and feces. The renal clearance of ciprofloxacin is typically 300–479 mL/min. Approximately 20–40% of the dose is excreted in the feces as the unchanged drug and as metabolites over a period of 5 days.
Indications
Corneal ulcers and superficial infections of the eye(s) and its adnexa caused by bacterial strains susceptible to ciprofloxacin.
Acute otitis externa, as well as acute otitis media with drainage via a tympanostomy tube, caused by bacterial strains susceptible to ciprofloxacin.
Contraindications
Hypersensitivity to ciprofloxacin, other quinolones, or any of the drug’s components.
Drug Interactions and Other Interactions
Since ciprofloxacin has low systemic concentrations when used topically in ophthalmic or otologic applications, interactions with other medications are unlikely. If multiple topical eye medications are used simultaneously, wait at least 5 minutes between applications. Eye ointments should be applied last.
Special Instructions for Use
For ophthalmic use only.
General
- Serious and sometimes fatal (anaphylactic) hypersensitivity reactions have been observed in patients undergoing quinolone therapy, some as early as after the first dose. Some reactions were accompanied by cardiovascular failure, loss of consciousness, tinnitus, swelling of the throat or face, dyspnea, hives, and itching. Hypersensitivity reactions were observed in only a few patients.
- Severe cases of acute hypersensitivity to ciprofloxacin may require emergency treatment. If clinically indicated, oxygen therapy and airway management should be provided.
- Ciprofloxacin should be discontinued at the first signs of a skin rash or any other signs of a hypersensitivity reaction.
- As with all antibacterial agents, prolonged use may lead to the overgrowth of antibiotic-resistant bacterial strains or fungi. If superinfection develops, appropriate therapy should be initiated.
- Tendon inflammation and rupture are possible with systemic therapy with fluoroquinolones, including ciprofloxacin, especially in elderly patients and in patients receiving concomitant corticosteroids. Therefore, treatment with Cipronex® eye/ear drops should be discontinued at the first signs of tendon inflammation.
Eye Drops
- Clinical experience with the use of this medication in children under 1 year of age, especially newborns, is quite limited.
- The use of Cipronex® eye drops is not recommended for newborns with neonatal blenorrhea of gonococcal or chlamydial origin, as it has not been evaluated in this patient population. Newborns with neonatal blenorrhea should receive treatment appropriate for their condition.
- When using Cipronex® eye drops, the risk of the drug entering the nasopharynx should be taken into account, as this may lead to the emergence and spread of bacterial resistance.
- In patients with corneal ulcers who frequently used eye drops containing ciprofloxacin, white ocular precipitates (drug residues) were observed; these disappeared after discontinuation of the eye drops. The occurrence of precipitates does not preclude continued use of the eye drops and does not adversely affect the course of the disease. Precipitates were observed between 24 hours and 7 days after the start of therapy. The deposits disappear completely either immediately or within 13 days after the start of therapy.
- Cipronex® eye drops contain benzalkonium chloride, which may cause irritation and discolor soft contact lenses.
- Wearing contact lenses during treatment of an eye infection is not recommended.
Therefore, patients should be advised not to wear contact lenses while being treated with Cipronex® eye drops. If patients are permitted to wear contact lenses, they should remove them before using the eye drops and wait at least 15 minutes before putting them back in.
Ear Drops
- The efficacy and safety of the drug in children under 1 year of age have not been evaluated.
- Although there are very limited data on patients under 1 year of age treated for acute otitis externa, there are no differences in the course of the disease in this patient population that would preclude the use of this medication. Based on the very limited data, a physician prescribing this medication to children under 1 year of age should weigh the clinical benefits against the known and potential unknown risks. The safety and efficacy of Cipronex® have not been studied in patients with a perforated eardrum; therefore it should be used with caution in patients with known or suspected perforation, or when there is a risk of tympanic membrane perforation
- If signs and symptoms of the disease do not resolve within a week of treatment, it is recommended to reevaluate the treatment regimen.
- Photosensitivity reactions of varying severity have been reported in patients treated with systemic quinolones. Since this medication is applied topically, photosensitivity reactions are unlikely.
- When instilling the medication into the ear, frequent medical monitoring should be performed to allow for the timely implementation of other therapeutic measures.
Use During Pregnancy or Breastfeeding.
Reproductive function
No studies have been conducted to evaluate the effect of topical application of Cipronex® on reproductive function.
Pregnancy
There are no adequate data on the use of Cipronex® in pregnant women. Animal studies do not indicate a direct harmful effect due to reproductive toxicity.
It is advisable to avoid using this medication during pregnancy.
Breastfeeding
When administered orally, ciprofloxacin has been detected in breast milk. It is unknown whether ciprofloxacin is excreted into breast milk following topical application to the eye or ear. Cipronex® should be used with caution in women who are breastfeeding.
Effect on the ability to drive or operate machinery.
This medication has no or negligible effect on the ability to drive or operate machinery. Temporary blurred vision or other visual disturbances may affect the ability to drive or operate machinery. If blurred vision occurs after instillation, the patient should wait until vision clears before driving or operating machinery.
There are no data regarding the effect of Cipronex® ear drops on the ability to drive or operate machinery.
Dosage and Administration
Ophthalmic Use
Adults, including the elderly, and children
Corneal ulcers
Cipronex® should be administered at the following intervals, including at night:
On Day 1, instill 2 drops into the conjunctival sac(s) of the affected eye(s) every 15 minutes for the first 6 hours, then 2 drops every 30 minutes for the first 24 hours;
On Day 2, instill 2 drops into the conjunctival sac(s) of the affected eye(s) every hour;
From the 3rd to the 14th day, instill 2 drops into the conjunctival sac(s) of the affected eye(s) every 4 hours.
In cases of corneal ulcer, treatment may last longer than 14 days; the dosing regimen and duration of treatment are determined by the doctor.
Bacterial superficial infections of the eye and its adnexa
The standard dose is 1–2 drops into the conjunctival sac(s) of the affected eye(s) 4 times a day.
For severe infections, the dose may be 1–2 drops every 2 hours during the day for the first two days.
Treatment usually lasts 7–14 days.
After instillation, it is recommended to tightly close the eyelids or use nasolacrimal occlusion. This reduces systemic absorption of the medication administered to the eye, thereby lowering the likelihood of systemic side effects.
When used in combination with other topical ophthalmic medications, a 10–15-minute interval should be observed between applications.
Children
The dosage for children aged 1 year and older is the same as for adults.
A clinical study of the drug’s use in newborns and infants under one month of age found that Cipronex® is clinically and microbiologically effective for the treatment of bacterial conjunctivitis in this patient population when administered 3 times daily for 4 days.
Patients with Impaired Liver or Kidney Function
The use of Cipronex® in this patient population has not been studied.
Precautions for Use
To prevent contamination of the dropper tip and the solution, take care not to touch the eyelids, surrounding areas, or other surfaces with the tip of the dropper bottle.
Use in Otology
Dosage
Adults, including elderly patients
For adults, the dose is 4 drops of Cipronex® into the ear canal twice daily.
For patients who require the use of ear swabs, the dose may be doubled only for the first application (i.e., 6 drops for children and 8 drops for adults).
In general, the duration of treatment should not exceed 5–10 days. In some cases, treatment may be extended, but in such cases, it is recommended to test the sensitivity of the local flora.
If other topical medications are used concurrently, a 10–15-minute interval should be observed between applications.
Children
The dose is 3 drops of Cipronex® into the ear canal twice daily. The safety and efficacy of Cipronex® have been studied in children aged 1 to 12 years. The safety and efficacy of the drug in children under 1 year of age have not been established.
Patients with Impaired Liver or Kidney Function
The use of Cipronex® in this patient population has not been studied.
Precautions for Use
The external auditory canal should be thoroughly cleaned. To prevent vestibular stimulation, it is recommended to administer the solution at room temperature or body temperature.
The patient should lie on the side opposite the affected ear. It is recommended to remain in this position for 5–10 minutes. Additionally, after local cleansing, a moistened gauze or absorbent cotton swab may be inserted into the ear canal for 1–2 days; however, it must be re-moistened with the solution twice daily to ensure saturation.
To prevent contamination of the dropper tip and the solution, take care not to touch the auricle, the external auditory canal, adjacent areas, or other surfaces with the tip of the dropper bottle.
Children.
Eye drops
Use in children from birth (see the “Special Considerations for Use” section).
Ear drops
Use in children 1 year of age and older.
Safety and efficacy in children under 1 year of age have not been established.
Overdose
Given the characteristics of this product, which is intended for external use, no toxic effects are expected when used in ophthalmology/otology at the recommended doses, nor in the event of accidental ingestion of the contents of a single vial.
Side Effects
The adverse reactions listed below are classified as follows: very common (≥1/10), common (≥1/100, <1/10), uncommon (≥1/1,000, <1/100), very rare (≥1/10,000, <1/1,000), rare (<1/10,000), or unknown (frequency cannot be estimated from available data). Within each group, adverse reactions are listed in order of decreasing severity. Data on adverse reactions were obtained during clinical trials and during the postmarketing period.
Adverse effects observed following the use of Cipronex® in the eye
|
Organ System Classes
|
Adverse reactions according to the MedDRA classification
|
|
Infections and infestations
|
Rare: stye, rhinitis
|
|
Immune system disorders
|
Rare: hypersensitivity
|
|
Nervous system
system
|
Common: dysgeusia
Uncommon: headache
Rare: dizziness
|
|
Eye disorders
|
Common: corneal deposits, eye discomfort, eye redness
Uncommon: keratopathy, corneal infiltrates, corneal discoloration, photophobia, decreased visual acuity, eyelid edema, blurred vision, eye pain, dry eyes, eye swelling, itchy eyes, foreign body sensation in the eye, increased tearing, eye discharge, scaling along the eyelid margins, eyelid desquamation, conjunctival edema
of the conjunctiva, erythema of the eyelids
Rare: ocular toxicity, punctate keratitis, keratitis, conjunctivitis, corneal dysfunction, corneal epithelial defect, diplopia, ocular hypoesthesia, asthenopia, eye irritation, eye inflammation, conjunctival hyperemia
|
|
Ear disorders
|
Rare: ear pain
|
|
Respiratory system, thoracic, and mediastinal disorders
|
Rare: hypersecretion of the paranasal sinuses
|
|
Gastrointestinal system
|
Uncommon: nausea
Rare: diarrhea, abdominal pain
|
|
Skin and subcutaneous tissue disorders
|
Rare: dermatitis
|
|
General disorders and administration site conditions
|
Rare: intolerance to the drug
|
|
Laboratory
tests
|
Rare: abnormal laboratory
tests
|
Adverse reactions reported with the use of Cipronex® in the ear
Table 2
|
Organ system classes
|
Adverse reactions according to the MedDRA classification
|
|
Nervous system
|
Uncommon: tearfulness, headache
|
|
Ear and labyrinth disorders
|
Uncommon: ear pain, ear fullness, otorrhea,
ear itching
Frequency unknown: ringing in the ears
|
|
Skin and subcutaneous tissue disorders
|
Uncommon: dermatitis
|
|
General disorders and administration site conditions
|
Uncommon: hyperthermia
|
Description of the listed adverse reactions
With topical application of fluoroquinolones, reactions such as (generalized) rash, toxic epidermal necrolysis, exfoliative dermatitis, Stevens-Johnson syndrome, and urticaria have occurred very rarely.
In isolated cases, when ciprofloxacin was applied to the eye, blurred vision, decreased visual acuity, and signs of drug residue have been observed.
Rarely, the drug’s components may cause a hypersensitivity reaction when applied to the ear. However, as with the application of any substance to the skin, there is always a possibility of an allergic reaction to any of the drug’s components (applicable only to Cipronex® ear drops).
Serious, and in some cases fatal (anaphylactic), hypersensitivity reactions—sometimes following the first dose—have been reported in patients receiving systemic quinolone therapy. Some reactions were accompanied by cardiovascular collapse, loss of consciousness, tingling, swelling of the throat or face, dyspnea, hives, and itching.
In patients receiving systemic fluoroquinolones, ruptures of the shoulder, wrist, Achilles, or other tendons have been reported, requiring surgical repair or resulting in prolonged disability. Clinical trials and postmarketing experience with systemic fluoroquinolones indicate that the risk of such ruptures may be increased in patients receiving corticosteroids, especially in elderly patients, and when the tendons, including the Achilles tendon, are subjected to high stress. To date, clinical and postmarketing data have not demonstrated a clear association between the use of Cipronex® and adverse reactions involving the musculoskeletal and connective tissues.
In patients with corneal ulcers, frequent use of Cipronex® resulted in the observation of a white precipitate in the eye (drug residue), which disappeared with continued use. The presence of a precipitate does not require discontinuation of Cipronex® and does not adversely affect the clinical course of recovery.
Shelf life
3 years. Do not use after the expiration date indicated on the package.
Shelf life after first opening: 4 weeks.
Storage Conditions
Store in the original packaging at a temperature not exceeding 25 °C.
Keep out of reach of children.
Packaging
5 mL of the product in a 5-mL polyethylene dropper bottle with a cap featuring a tamper-evident ring. One bottle per cardboard box.
Dispensing Category
By prescription only.
Applicant
Pharmaceutical Plant “POLPHARMA” S.A./
Pharmaceutical Works “POLPHARMA” S.A.