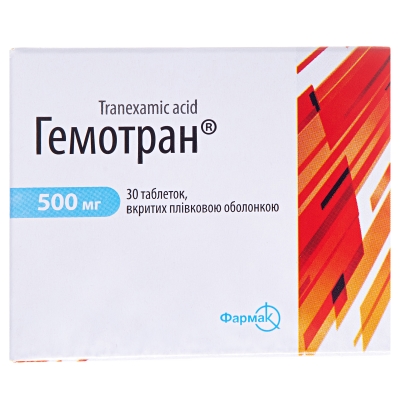

Hemotrans tablets, film-coated, 500 mg, No. 30 (10 x 3)
1 tablet contains 500 mg of tranexamic acid, calculated as 100% dry weight;
Excipients: povidone, low-substituted hydroxypropyl cellulose, hydroxypropyl cellulose, anhydrous colloidal silicon dioxide, talc, polyethylene glycol 8000, calcium stearate;
film coating: Opadry White 03 F 180011 (hypromellose, titanium dioxide (E 171), macrogol).
Dosage Form
Film-coated tablets.
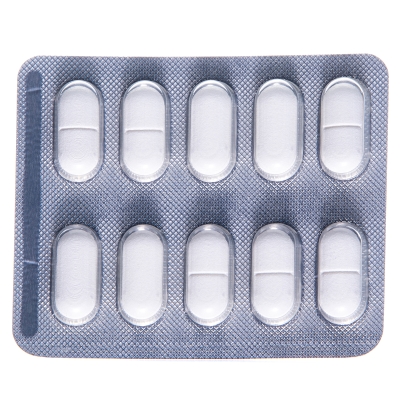
Main physical and chemical properties: oblong tablets with biconvex surfaces, a white or nearly white score line, and a film coating.
Pharmacotherapeutic group
Antihemorrhagic agents. Fibrinolysis inhibitors.
ATC code B02A A02.
Pharmacological Properties
Pharmacodynamics.
Antifibrinolytic, antiallergic, anti-inflammatory. Competitively inhibits plasminogen activator and binds plasmin at higher concentrations. It has been noted that the inhibitory effect of tranexamic acid on plasminogen activation by urokinase is 6–100 times greater, and by streptokinase—6–40 times greater, than the inhibitory effect of aminocaproic acid. The antifibrinolytic effect of tranexamic acid is approximately 10 times greater than that of aminocaproic acid. It prolongs prothrombin time. It inhibits the formation of kinins and other peptides involved in inflammatory and allergic reactions.
Pharmacokinetics.
When taken orally, 30–50% of the dose is absorbed. Cmax is reached 3 hours after dosing and is 8 mg/L and 15 mg/L, respectively, at doses of 1 g and 2 g. The concentration-time curve is triphasic, with a half-life (T1/2) of 3 hours in the terminal phase. Approximately 3% is bound to protein (plasminogen) in the blood. The initial volume of distribution is 9–12 liters.
It readily crosses histohematological barriers, including the blood-brain barrier and the placental barrier. The concentration in cerebrospinal fluid is 1/10 that in plasma. It is present in seminal fluid, where it inhibits fibrinolytic activity but does not affect sperm motility. A small portion undergoes biotransformation. The primary route of elimination is glomerular filtration. More than 95% (mostly in its unchanged form) is excreted in the urine. Total renal clearance is equal to plasma clearance. Antifibrinolytic concentrations are maintained in various tissues for up to 17 hours and in blood plasma for up to 7–8 hours.
Tranexamic acid rapidly penetrates into the synovial fluid and synovial membrane. The concentration in synovial fluid is the same as in blood serum. The half-life of tranexamic acid is approximately 3 hours. The concentration of tranexamic acid in the blood is lower than in other tissues. In breast milk, the concentration is approximately 1/100 of the peak concentration in blood serum. The concentration of tranexamic acid in cerebrospinal fluid is approximately 1/10 of the concentration in plasma. The drug penetrates into the intraocular fluid, where the concentration is approximately 1/10 that in plasma.
In patients with renal insufficiency, the concentration of tranexamic acid in blood plasma increases.
Indications
Short-term treatment of bleeding or risk of bleeding associated with increased fibrinolysis or fibrinogenolysis.
Local fibrinolysis is observed in the following conditions:
- prostatectomy or bladder surgery;
- menorrhagia;
- nosebleeds;
- cervical conization;
- post-traumatic hyphaema.
Hereditary angioedema.
Tooth extraction in patients with hemophilia.
Contraindications
- Hypersensitivity to tranexamic acid or to other components of the drug.
- Severe renal insufficiency (due to the risk of accumulation).
- Acute thromboembolic diseases.
- History of arterial or venous thrombosis.
- Fibrinolytic conditions caused by depletion coagulopathy.
- History of seizures.
Drug Interactions and Other Interactions
Tranexamic acid counteracts thrombolytic therapy with fibrinolytic agents.
Special considerations
In cases of renal insufficiency (depending on the degree of elevation in serum creatinine), the dose and frequency of administration should be reduced. In cases of hematuria of renal origin (especially in patients with hemophilia), there is a risk of developing mechanical anuria as a result of thrombus formation in the ureters.
Patients with a personal or family history of thromboembolic complications (patients with thrombophilia) should receive tranexamic acid only when there are direct medical indications and under strict medical supervision.
During long-term therapy, patients with hereditary angioedema should have their vision (e.g., visual acuity, visual fields, intraocular pressure, fundus examination) and liver function (liver function tests) checked regularly.
Tranexamic acid should be used with caution in patients taking oral contraceptives due to an increased risk of thrombosis.
The use of tranexamic acid is not recommended in cases of increased fibrinolysis due to disseminated intravascular coagulation.
Patients with irregular menstrual bleeding should not use tranexamic acid until the cause of such bleeding has been determined. If tranexamic acid does not reduce menstrual bleeding, alternative treatment should be considered.
If visual disturbances occur, treatment should be discontinued.
There is no clinical experience with the use of tranexamic acid for the treatment of menorrhagia in children under 15 years of age.
Pregnancy and lactation.
Pregnancy
Tranexamic acid crosses the placenta. Although no teratogenic effects of tranexamic acid on fetal development were observed in preclinical studies, it is recommended to follow general guidelines for the use of medications during pregnancy; specifically, the drug should be prescribed only when the expected benefit to the pregnant woman outweighs the potential risk to the fetus.
Breastfeeding
Tranexamic acid passes into breast milk at a concentration of approximately 1/100 of its concentration in the mother’s blood. An antifibrinolytic effect in the infant is unlikely.
Effects on the ability to drive and operate machinery.
No data available.
Dosage and Administration
For adults, the drug is administered orally. Take regardless of meals.
| Local fibrinolysis: 15–25 mg/kg body weight (2–3 tablets of 500 mg) 2–3 times daily.
For the indications listed below, the following dosages may be used: |
|
|
|
|
|
| Hereditary angioedema: For some patients who are familiar with the course of exacerbations, 1–1.5 g (2–3 tablets of 500 mg each) 2–3 times a day for several days is usually sufficient. Other patients should take the medication at the same dose for an extended period, depending on the course of the disease. |
| Tooth extraction in patients with hemophilia: 25 mg/kg (2–3 500-mg tablets) every 8 hours. |
Patients with renal insufficiency
Dose adjustment is necessary for patients with mild to moderate renal insufficiency based on plasma creatinine levels.
| Serum creatinine | Oral dose |
| 120–249 μmol/L | 15 mg/kg twice daily |
| 250–500 μmol/L | 15 mg/kg every 24 hours |
Elderly patients
No dose adjustment is required in the absence of renal excretory dysfunction.
Children
There is no clinical experience with the use of tranexamic acid in children under 15 years of age with menorrhagia; therefore, the drug should not be used in this patient population.
The recommended dose for children is 25 mg/kg. Data on the efficacy, dosage, and safety of tranexamic acid in children are limited.
Overdose
Symptoms: nausea, vomiting, abdominal pain, orthostatic hypotension.
Treatment: Induce vomiting, perform gastric lavage, and administer activated charcoal. Fluid intake is necessary to stimulate renal excretion. Symptomatic treatment is provided, and anticoagulant therapy is administered if necessary.
Side Effects
Adverse reactions are classified according to their frequency and effect on organs or organ systems. The following adverse reactions have been reported, categorized by frequency as follows: very common (≥1/10); common (≥1/100 − < 1/10); uncommon (≥1/1,000 − < 1/100); rare (≥1/10,000 − < 1/1,000); very rare (< 1/10,000); frequency unknown (cannot be estimated from the available data).
Gastrointestinal disorders
Very rare: nausea, vomiting, diarrhea, which resolve upon dose reduction.
Skin and subcutaneous tissue disorders
Rare: allergic skin reactions.
Eye disorders
Rare: color vision disturbances, visual disturbances, retinal vein/artery occlusion.
Immune system disorders
Very rare: hypersensitivity reactions, including anaphylaxis.
Vascular disorders
Rare: thromboembolism.
Very rare: arterial or venous thrombosis of any location.
Reporting of Suspected Adverse Reactions
Reporting suspected adverse reactions that occur after the drug’s approval is very important. This allows for ongoing monitoring of the benefit-risk profile of the drug. Healthcare professionals should report any suspected adverse reactions through the national pharmacovigilance system.
Shelf Life
2 years.
Do not use the drug after the expiration date printed on the package.
Storage conditions
Store in the original packaging at a temperature not exceeding 25 °C.
Keep out of reach of children.
Packaging
10 tablets per blister pack. 3 blister packs per package.
Manufacturer
Farmak JSC.
Address
74 Kirillovskaya St., Kyiv, 04080, Ukraine.